Related Experiment Video
Updated: Mar 12, 2026


Observational Study Protocol for Repeated Clinical Examination and Critical Care Ultrasonography Within the Simple Intensive Care Studies
Published on: January 16, 2019
Applicability of stroke volume variation in patients of a general intensive care unit: a longitudinal observational
Sebastian Mair1, Julia Tschirdewahn1, Simon Götz1
1II. Medizinische Klinik und Poliklinik, Klinikum rechts der Isar, Technische Universität München, Ismaninger Strasse 22, 81675, Munich, Germany.

Abstract:
Sinus rhythm (SR) and controlled mechanical ventilation (CV) are mandatory for the applicability of respiratory changes of the arterial curve such as stroke volume variation (SVV) to predict fluid-responsiveness. Furthermore, several secondary limitations including tidal volumes <8 mL/kg and SVV-values within the "gray zone" of 9-13% impair prediction of fluid-responsiveness by SVV. Therefore, we investigated the prevalence of these four conditions in general ICU-patients. This longitudinal observational study analyzed a prospectively maintained haemodynamic database including 4801 transpulmonary thermodilution and pulse contour analysis measurements of 278 patients (APACHE-II 21.0 ± 7.4). The main underlying diseases were cirrhosis (32%), sepsis (28%), and ARDS (17%). The prevalence of SR and CV was only 19.4% (54/278) in the first measurements (primary endpoint), 18.8% (902/4801) in all measurements and 26.5% (9/34) in measurements with MAP < 65 mmHg and CI < 2.5 L/min/m2 and vasopressor therapy. In 69.1% (192/278) of the first measurements and in 65.9% (3165/4801) of all measurements the patients had SR but did not have CV. In 1.8% (5/278) of the first measurements and in 2.5% (119/4801) of all measurements the patients had CV but lacked SR. In 9.7% (27/278) of the first measurements and in 12.8% (615/4801) of all measurements the patients did neither have SR nor CV. Only 20 of 278 (7.2%) of the first measurements and 8.2% of all measurements fulfilled both major criteria (CV, SR) and both minor criteria for the applicability of SVV. The applicability of SVV in ICU-patients is limited due to the absence of mandatory criteria during the majority of measurements.
Related Concept Videos
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:27
Regulation of Stroke Volume
Preload refers to the degree of stretch on the heart before it contracts. It's analogous to the stretching of a rubber band; the more it's stretched, the more forcefully it snaps back. This concept is encapsulated in the Frank-Starling law of the...
 01:11
Cardiac Output and Stroke Volume
In an average resting adult male, the typical cardiac...
 01:19
Cardiac Output I:Effect of Heart Rate on Cardiac Output
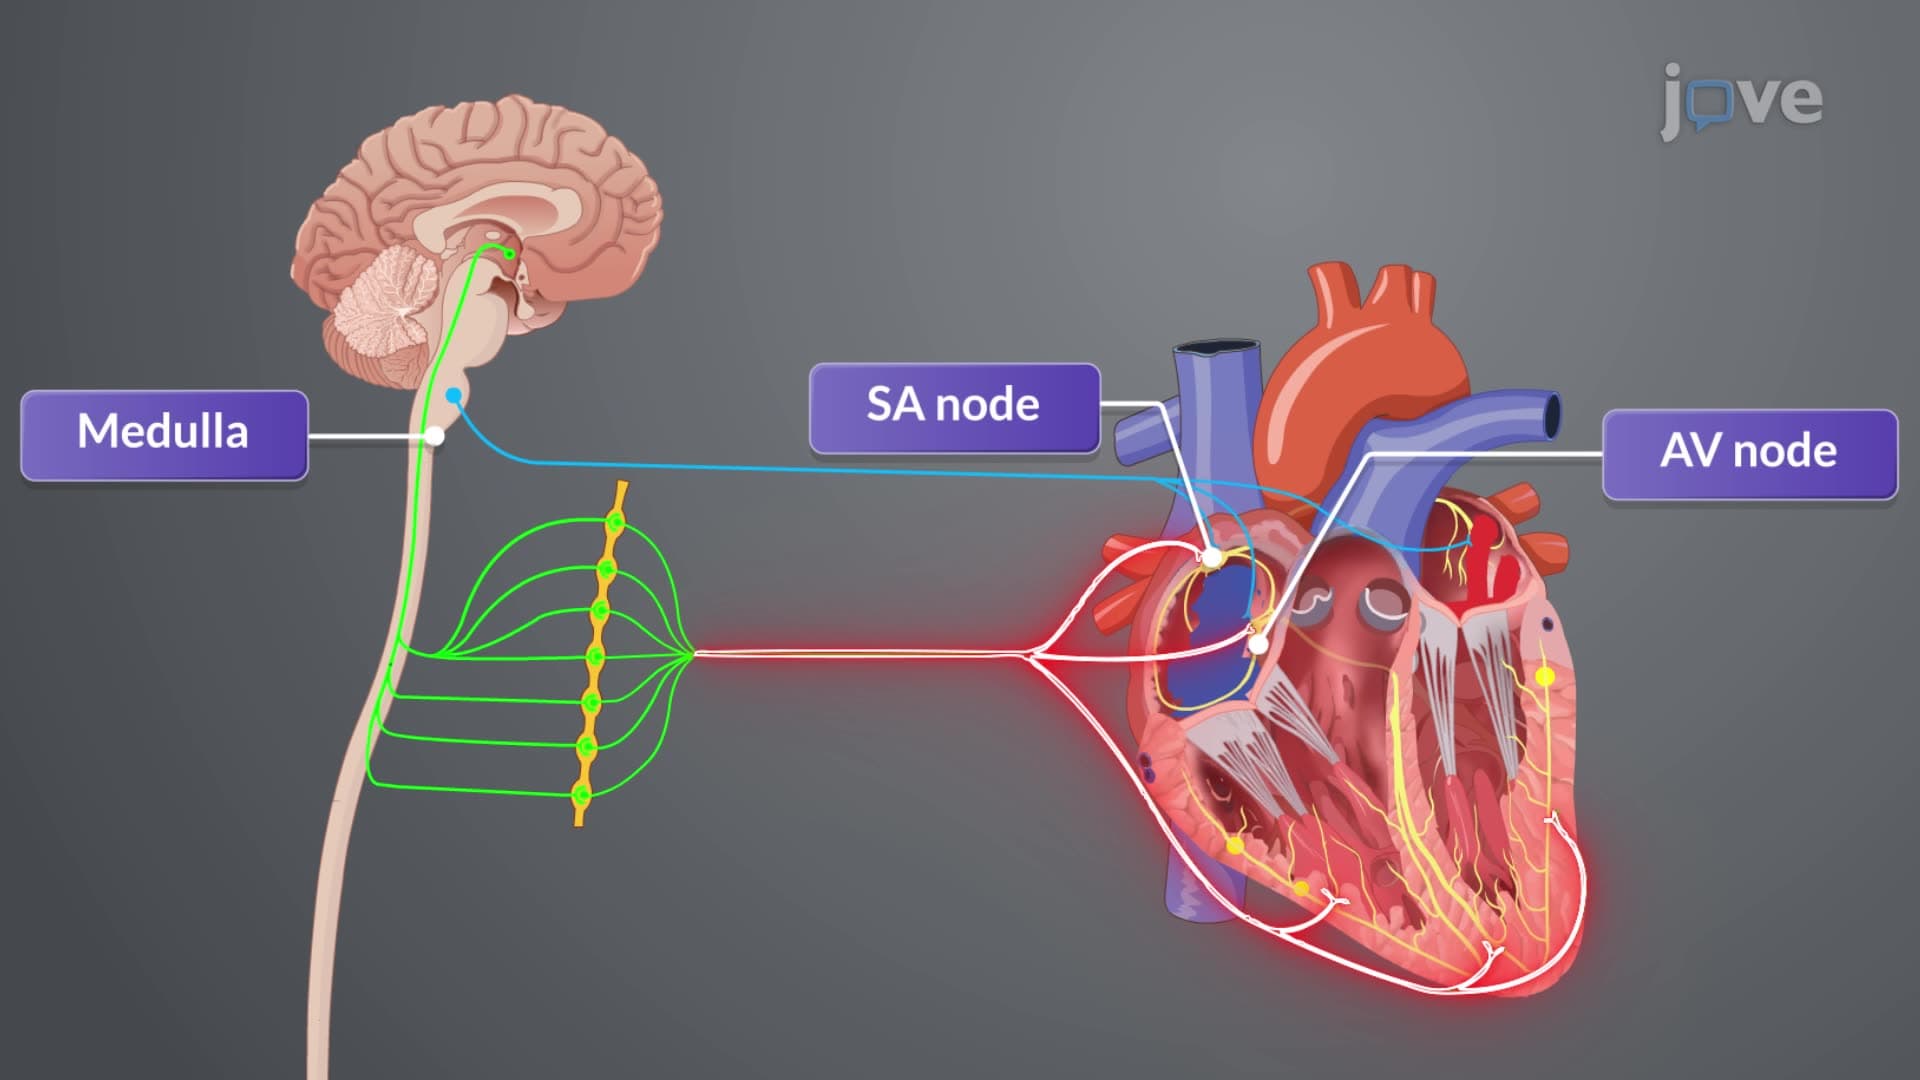
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...
 01:05
Pulse
Pulse Rate and its Significance
Pulse rate, often measured in beats per minute (bpm), reflects the heart rate (HR), which is influenced by numerous factors such as stress, physical activity, and hormonal changes. A normal resting adult pulse rate falls...
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send...