Related Experiment Video
Updated: Mar 12, 2026
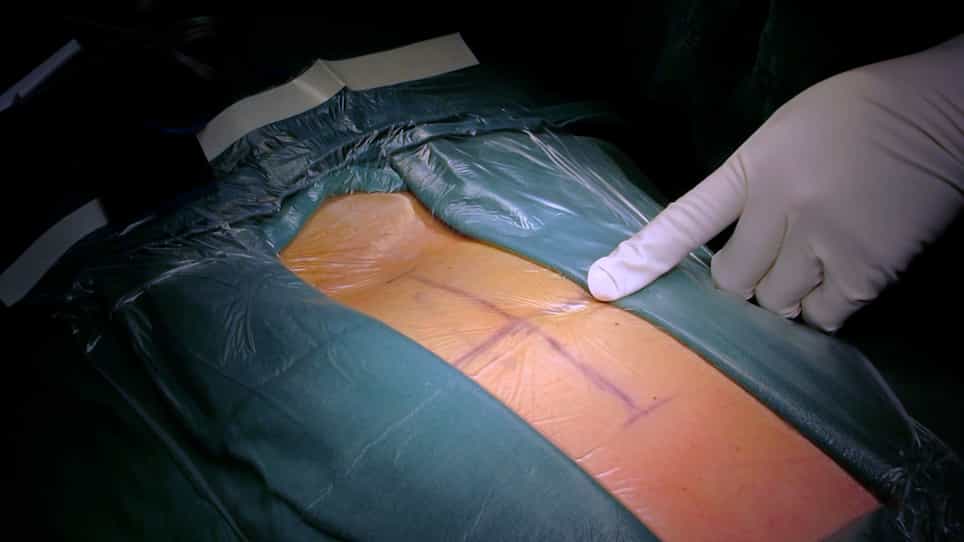

Modified Posterior Vertebral Column Resection for Patients with Thoracolumbar Kyphotic Deformity
Published on: September 16, 2022
Craniovertebral junction anomalies: When is resurgery required?
Pavaman Sindgikar1, Kuntal Kanti Das1, Jayesh Sardhara1
1Department of Neurosurgery, Sanjay Gandhi Postgraduate Institute of Medical Sciences, Lucknow, Uttar Pradesh, India.

Background:
Craniovertebral junction (CVJ) abnormalities, such as atlantoaxial dislocation (AAD) with or without basilar invagination (BI), with or without associated Chiari malformation (CM), may cause a high cervical myelopathy. Occasionally, mechanical factors such as inadequate canal decompression, torticollis, and/or scoliosis may lead to lack of improvement following the primary surgery. Furthermore, implant-related factors, requiring implant revision/removal, or the presence of surgical site infections may cause the patient to undergo resurgery.
Aims:
This study was aimed at highlighting the underlying etiopathogenesis of resurgery following the primary surgery undertaken in CVJ abnormalities.
Setting And Design:
This was a retrospective study from a tertiary care referral institute focusing on 414 operated cases of CVJ anomalies.
Materials And Methods:
The data of 55 patients who underwent resurgery included their clinicoradiological assessment and operative records. The inclusion criteria included failed primary procedure, repeat procedure for construct failure, infection at the surgical site, or wound dehiscence. Pure CM patients without bony anomalies were excluded from the study.
Results:
A total of 137 procedures were performed in 55/414 (13%) patients. Causes of resurgery could be divided into ventral [redo or denovo transoral decompression (TOD) or wound-related complications, n = 33, 40.2%] and dorsal causes (implant-related factors/wound infections, n = 49, 59.8%). De novo TOD was done in persisting myelopathy following posterior fusion (PF) with C1-2 distraction (n = 15,18.3%,). Redo TOD was done for residual anterior bony compression [n = 8, 9.6%, OR 0.61; [CI = 0.20-1.86]. Causes for oral wound reexplorations (n = 10, 12.2%) included velopharyngeal insufficiency, wound resuturing, oral bleeding, and cerebrospinal fluid (CSF) leak. Dorsal causes included: (A) Implant factors (n = 27, 32.7%) and (B) neck wound reexplorations (n = 22, 26.8%). Presence of subaxial spine scoliosis, torticollis, and asymmetric joints increased the incidence of reexploration. Occipitocervical fusion rather than C1-2 fusion was more prone towards construct loosening.
Conclusions:
Patients undergoing distraction with PF may require transoral surgery due to persisting myelopathy, especially in the presence of torticollis, scoliosis, and symmetrical joints. Single stage TOD+PF increases the chances of implant infection due to tissue contamination, bacteremia, or transfacetal migration of microbes. Chronic/recurrent sinus is usually a harbinger of deeper infection and can be cured with implant removal.
More Related Videos


Related Concept Videos
 01:22
Sutures of the Skull
Sutures are immobile joints between adjacent bones of the skull. The narrow gap between the bones is filled with dense, fibrous connective tissue that unites the bones. The long sutures located between the skull bones are not straight but instead follow irregular, tightly twisting paths. These twisting lines tightly...
 01:14
Cranial Bones: Superior and Posterior View
The frontal bone is the single bone that forms the forehead. At its anterior midline, between the eyebrows, there is a slight depression called the glabella. The frontal bone also forms the supraorbital margin of the orbit. Near the middle of this margin is the supraorbital foramen, the opening that provides passage for a sensory nerve to the forehead. The frontal bone is thickened just above each supraorbital margin,...