Related Experiment Video
Updated: Mar 12, 2026
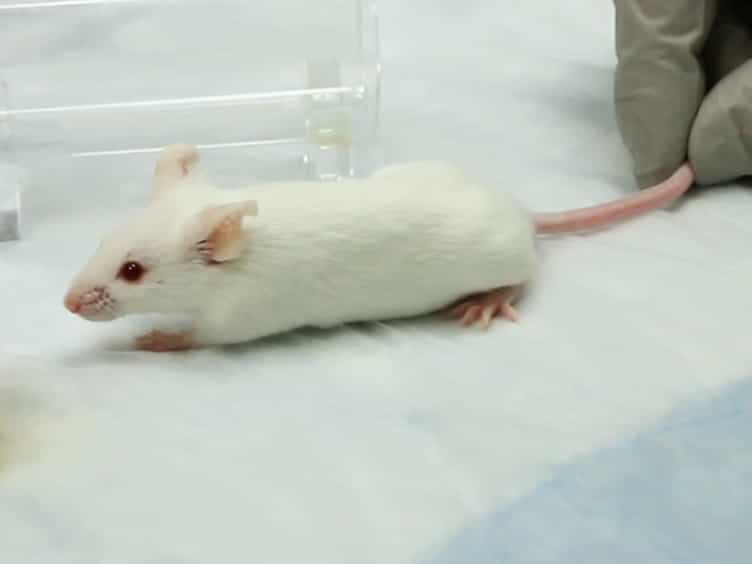

Assessment of Respiratory Function in Conscious Mice by Double-chamber Plethysmography
Published on: July 10, 2018
Diagnostic accuracy of methacholine challenge tests assessing airway hyperreactivity in asthmatic patients - a
Richard Kraemer1, Hans-Jürgen Smith2, Thomas Sigrist3
1Department of Clinical Research, University of Berne, Kirchenfeldstrasse 74, CH-3005, Berne, Switzerland. richard.kraemer@swissonline.ch.

Background:
There are few studies comparing diagnostic accuracy of different lung function parameters evaluating dose-response characteristics of methacholine (MCH) challenge tests (MCT) as quantitative outcome of airway hyperreactivity (AHR) in asthmatic patients. The aim of this retrospectively analysis of our database (Clinic Barmelweid, Switzerland) was, to assess diagnostic accuracy of several lung function parameters quantitating AHR by dose-response characteristics.
Methods:
Changes in effective specific airway conductance (sGeff) as estimate of the degree of bronchial obstruction were compared with concomitantly measured forced expiratory volume in 1 s (FEV1) and forced expiratory flows at 50% forced vital capacity (FEF50). According to the GINA Guidelines the patients (n = 484) were classified into asthmatic patients (n = 337) and non-asthmatic subjects (n = 147). Whole-body plethysmography (CareFusion, Würzburg, Germany) was performed using ATS-ERS criteria, and for the MCTs a standardised computer controlled protocol with 3 consecutive cumulative provocation doses (PD1: 0.2 mg; PD2: 1.0 mg; PD3: 2.2 mg) was used. Break off criterion for the MCTs were when a decrease in FEV1 of 20% was reached or respiratory symptoms occurred.
Results:
In the assessment of AHR, whole-body plethysmography offers in addition to spirometry indices of airways conductance and thoracic lung volumes, which are incorporated in the parameter sGeff, derived from spontaneous tidal breathing. The cumulative percent dose-responses at each provocation step were at the 1st level step (0.2 mg MCH) 3.7 times, at the 2nd level step (1 mg MCH) 2.4 times, and at the 3rd level step (2.2 mg MCH) 2.0 times more pronounced for sGeff, compared to FEV1. A much better diagnostic odds ratio of sGeff (7.855) over FEV1 (6.893) and FEF50 (4.001) could be found. Moreover, the so-called dysanapsis, and changes of end-expiratory lung volume were found to be important determinants of AHR.
Conclusions:
Applying plethysmographic tidal breathing analysis in addition to spirometry in MCTs provides relevant advantages. The absence of deep and maximal inhalations and forced expiratory manoeuvres improve the subject's cooperation and coordination, and provide sensitive and differentiated test results, improving diagnostic accuracy. Moreover, by the combined assessment, pulmonary hyperinflation and dysanapsis can be respected in the differentiation between "asthmatics" and "non-asthmatics".


Related Concept Videos
 01:30
Asthma-IV: Diagnostic and Management
Clinical Assessment for Asthma:
This is the first step in diagnosing and managing asthma. It includes:
 01:15
Myasthenia Gravis: Diagnostic Tests
The edrophonium test is a diagnostic tool for myasthenia gravis. It involves...
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:20
Asthma: Pathogenesis and Management
Asthma is classified as allergic and non-allergic. Allergens such as dust mites, pollen, and pet dander trigger allergic asthma, while factors like cold air, intense emotions, or exercise can induce non-allergic asthma.
 01:24
Antiasthma Drugs: Methylxanthines
Theophylline is thought to inhibit phosphodiesterase enzymes, increasing intracellular levels of cyclic adenosine monophosphate (cAMP) and cyclic guanosine monophosphate (cGMP). This rise in cAMP and cGMP concentrations stimulates cardiac function,...
 01:26
Asthma-II: Pathophysiology and Classification
Additionally, environmental and genetic factors play crucial roles in determining an individual's susceptibility to asthma and the severity of their condition.
Critical processes in asthma pathophysiology include: