Related Experiment Video
Updated: Mar 11, 2026
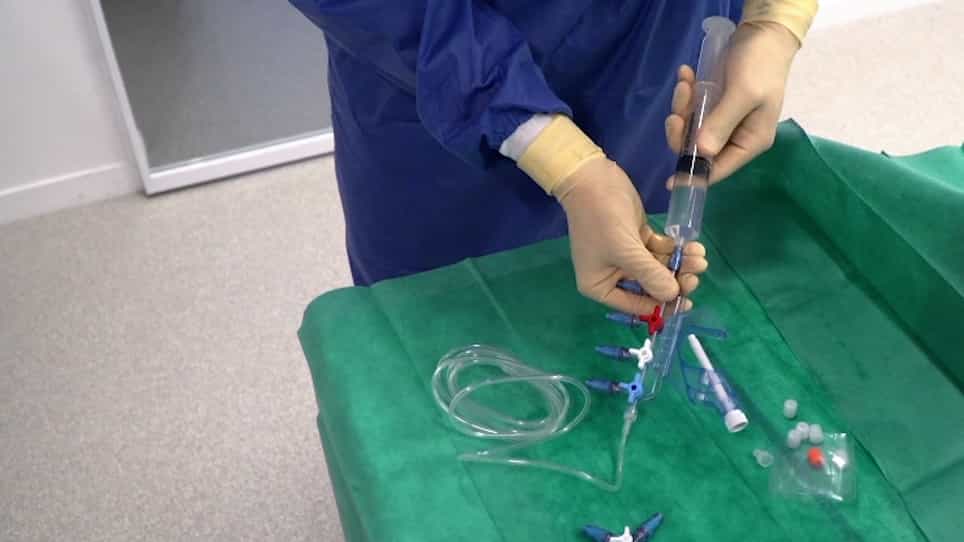

A Protocol to Set Up Needle-Free Connector with Positive Displacement on Central Venous Catheter in Intensive Care Unit
Published on: July 13, 2019
[Multidimensional Strategy Regarding the Reduction of Central-Line Associated Infection in Pediatric Intensive Care]
Jorge Rodrigues1, Andrea Dias2, Guiomar Oliveira3
1Faculdade de Medicina. Universidade de Coimbra. Coimbra.

Insights
Implementing central venous catheter care bundles in a Pediatric Intensive Care Unit eliminated central-line associated bloodstream infections. Continued vigilance is crucial to maintain this infection-free status and reduce patient risk.
Area of Science:
- Pediatric Intensive Care
- Infection Control
- Clinical Practice Improvement
Background:
- Central-line associated bloodstream infections (CLABSIs) pose a significant risk in pediatric intensive care settings.
- Evaluating the impact of care bundles on CLABSI rates is essential for patient safety.
Purpose of the Study:
- To assess the CLABSI rate following the implementation of central venous catheter care bundles.
- To compare the post-implementation CLABSI rate with historical control data.
Main Methods:
- A prospective, observational study conducted in a Pediatric Intensive Care Unit over five months.
- Inclusion of all pediatric patients requiring central venous catheter insertion.
- Comparative analysis with historical control data (Group 1 vs. Group 2).
Main Results:
- No central-line associated bloodstream infections were reported during the study period (Group 2).
- Seventy-five children and 105 central venous catheters were analyzed.
- Demographics and catheter characteristics were comparable to historical controls, with a longer median length of stay in Group 2.
Conclusions:
- A multidimensional strategy effectively eliminated CLABSIs in the Pediatric Intensive Care Unit.
- Sustained implementation of prevention strategies is necessary to maintain the absence of CLABSIs.
Introduction:
To determine the central-line associated bloodstream infection rate after implementation of central venous catheter-care practice bundles and guidelines and to compare it with the previous central-line associated bloodstream infection rate.
Material And Methods:
A prospective, longitudinal, observational descriptive study with an exploratory component was performed in a Pediatric Intensive Care Unit during five months. The universe was composed of every child admitted to Pediatric Intensive Care Unit who inserted a central venous catheter. A comparative study with historical controls was performed to evaluate the result of the intervention (group 1 versus group 2).
Results:
Seventy five children were included, with a median age of 23 months: 22 (29.3%) newborns; 28 (37.3%) with recent surgery and 32 (43.8%) with underlying illness. A total of 105 central venous catheter were inserted, the majority a single central venous catheter (69.3%), with a mean duration of 6.8 ± 6.7 days. The most common type of central venous catheter was the short-term, non-tunneled central venous catheter (45.7%), while the subclavian and brachial flexure veins were the most frequent insertion sites (both 25.7%). There were no cases of central-line associated bloodstream infection reported during this study. Comparing with historical controls (group 1), both groups were similar regarding age, gender, department of origin and place of central venous catheter insertion. In the current study (group 2), the median length of stay was higher, while the mean duration of central venous catheter (excluding peripherally inserted central line) was similar in both groups. There were no statistical differences regarding central venous catheter caliber and number of lumens. Fewer children admitted to Pediatric Intensive Care Unit had central venous catheter inserted in group 2, with no significant difference between single or multiple central venous catheter.
Discussion:
After multidimensional strategy implementation there was no reported central-line associated bloodstream infection Conclusions: Efforts must be made to preserve the same degree of multidimensional prevention, in order to confirm the effective reduction of the central-line associated bloodstream infection rate and to allow its maintenance.

Related Concept Videos
 01:22
Healthcare Associated Infections II: Preventive Measures
The best practices for preventing healthcare-associated infections include hand hygiene, patient risk...
 01:27
Parentral Nutrition: Centeral and Peripheral Parental Nutrition
PN can be administered through two primary routes:
1. Central Parenteral Nutrition (CPN):
CPN involves delivering a high concentration of nutrients through a large vein. This is typically achieved using a Peripherally Inserted Central Catheter (PICC) or,...
 01:29
Endocarditis IV: Nursing Management
 01:26
Standard Precaution
Hand hygiene is the most crucial means to prevent the transmission of disease. Employers are legally required to provide their workers with personal protective equipment (PPE) to minimize exposure or contact with...
 01:26
Healthcare Associated Infections I: Iatrogenic, Exogenic and Endogenic
HAIs significantly increase the cost of health care. Extended stays in healthcare institutions, increased disability, increased costs of medications, including specialized antibiotics, and prolonged recovery times add to the patient's expenses and the healthcare institution and funding bodies.
 01:29
Venous Thrombosis III: Interprofessional Care