Related Experiment Video
Updated: Mar 11, 2026


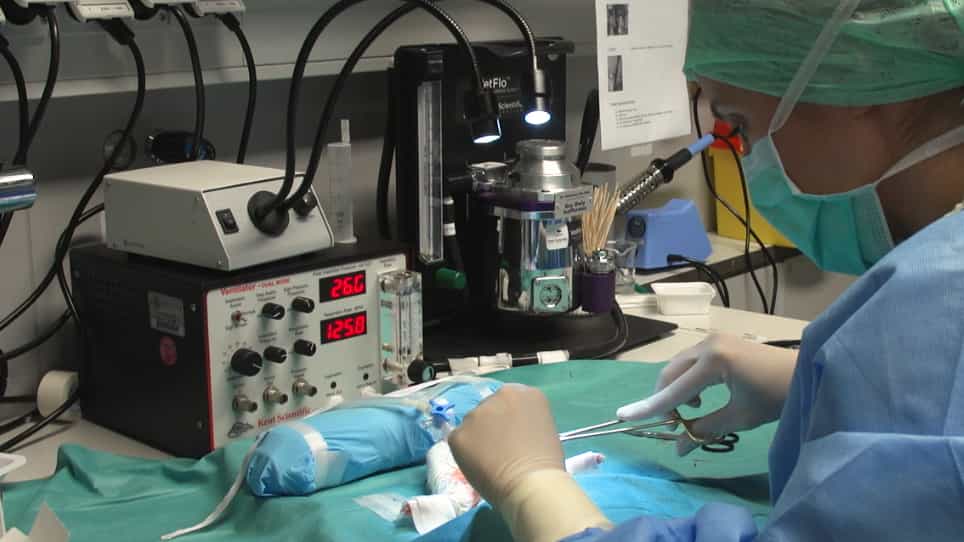
Standardized Model of Ventricular Fibrillation and Advanced Cardiac Life Support in Swine
Published on: January 30, 2020
Ventricular Fibrillation-Induced Cardiac Arrest Results in Regional Cardiac Injury Preferentially in Left Anterior
Giridhar Kaliki Venkata1, John R Forder2, Dan Clark2
1Division of Pediatric Critical Care Medicine, Department of Pediatrics, University of Florida College of Medicine, Gainesville, FL, USA; Division of Pediatric Cardiology, Congenital Heart Center, Department of Pediatrics, University of Florida College of Medicine, Gainesville, FL, USA.

Insights
Post-cardiac arrest myocardial dysfunction causes wall motion abnormalities in the left anterior descending artery territory. However, no perfusion defects were observed in these affected segments.
Area of Science:
- Cardiology
- Cardiovascular Research
- Myocardial Infarction
Background:
- Cardiac arrest (CA) leads to myocardial dysfunction due to global ischemia.
- The specific coronary arterial territory affected by post-CA myocardial dysfunction is not well understood.
- Understanding regional myocardial involvement is crucial for targeted therapeutic strategies.
Purpose of the Study:
- To investigate whether specific coronary arterial territories are preferentially involved in myocardial dysfunction after resuscitation from cardiac arrest.
- To test the hypothesis that there is no preferential involvement of any coronary artery during electrically induced ventricular fibrillation (VF) in a piglet model.
Main Methods:
- A prospective, randomized controlled study involving 12 piglets divided into baseline and VF groups.
- Ventricular fibrillation (VF) was induced for 5 minutes, followed by resuscitation according to AHA PALS guidelines.
- Cardiac MRI was performed 4 hours after return of spontaneous circulation (ROSC) to assess segmental wall motion and perfusion.
Main Results:
- Significant segmental wall motion abnormalities were observed in the left anterior descending (LAD) artery territory (segments 7, 13, and 14) post-resuscitation.
- Specifically, wall motion decreased from baseline values in these LAD segments (e.g., segment 7: 4.68 ± 0.54 mm vs. 3.31 ± 0.64 mm, p=0.0026).
- No perfusion defects were identified in the myocardial segments exhibiting wall motion abnormalities.
Conclusions:
- Post-cardiac arrest myocardial dysfunction is associated with segmental wall motion defects, particularly within the LAD coronary artery territory.
- Despite functional deficits, the involved myocardial segments did not show perfusion defects, suggesting potential for recovery.
- These findings highlight regional vulnerability in the myocardium following cardiac arrest and resuscitation.
Abstract:
Objective. Decreased cardiac function after resuscitation from cardiac arrest (CA) results from global ischemia of the myocardium. In the evolution of postarrest myocardial dysfunction, preferential involvement of any coronary arterial territory is not known. We hypothesized that there is no preferential involvement of any coronary artery during electrical induced ventricular fibrillation (VF) in piglet model. Design. Prospective, randomized controlled study. Methods. 12 piglets were randomized to baseline and electrical induced VF. After 5 min, the animals were resuscitated according to AHA PALS guidelines. After return of spontaneous circulation (ROSC), animals were observed for an additional 4 hours prior to cardiac MRI. Data (mean ± SD) was analyzed using unpaired t-test; p value ≤ 0.05 was considered statistically significant. Results. Segmental wall motion (mm; baseline versus postarrest group) in segment 7 (left anterior descending (LAD)) was 4.68 ± 0.54 versus 3.31 ± 0.64, p = 0.0026. In segment 13, it was 3.82 ± 0.96 versus 2.58 ± 0.82, p = 0.02. In segment 14, it was 2.42 ± 0.44 versus 1.29 ± 0.99, p = 0.028. Conclusion. Postarrest myocardial dysfunction resulted in segmental wall motion defects in the LAD territory. There were no perfusion defects in the involved segments.