Related Experiment Video
Updated: Mar 11, 2026

Multiplex Therapeutic Drug Monitoring by Isotope-dilution HPLC-MS/MS of Antibiotics in Critical Illnesses
Published on: August 30, 2018
Clinical Outcomes of Extended Versus Intermittent Infusion of Piperacillin/Tazobactam in Critically Ill Patients: A
Sheung-Yin Fan1, Hoi-Ping Shum2, Wing-Yee Cheng1
1Department of Pharmacy, Pamela Youde Nethersole Eastern Hospital, Chai Wan, Hong Kong, China.

Study Objective:
To determine whether critically ill patients receiving extended-infusion (EI) piperacillin/tazobactam would have improved clinical outcomes compared with patients receiving intermittent infusions.
Design:
Single-center, open-label, prospective study.
Setting:
Twenty-two-bed intensive care unit (ICU) in a regional hospital in Hong Kong.
Patients:
A total of 367 adults who had a diagnosis of either bacterial infection or neutropenic fever and had received treatment with piperacillin/tazobactam for at least 48 hours between December 1, 2013, and August 31, 2015.
Intervention:
Patients were assigned to receive piperacillin/tazobactam as either a 4-hour EI (182 patients [EI group]) or a 30-minute intermittent infusion (185 patients [non-extended infusion (NEI) group]).
Measurements And Main Results:
All patients were followed for at least 14 days after treatment assignment. The primary outcome was the 14-day mortality rate after initiation of piperacillin/tazobactam. Secondary outcomes included in-hospital mortality rate, time to defervescence, duration of mechanical ventilatory support, length of ICU stay, and duration of hospital stay. Both groups demonstrated similar 14-day mortality (11.5% in the EI group vs 15.7% in the NEI group, p=0.29). The mean time to defervescence was significantly reduced in the EI group (4 days in the EI group vs 6 days in the NEI group, p=0.01); no significant differences between groups were noted in the other secondary outcomes. An Acute Physiology and Chronic Health Evaluation II score of 29.5 or higher was found to strongly predict 14-day mortality (p=0.03) by Classification and Regression Tree analysis. In the post hoc analyses, a 14-day mortality benefit was demonstrated in patients in the EI group in whom infectious organisms were identified (mortality rate 9.3% in the EI group vs 22.4% in the NEI group, p=0.01) and in whom respiratory tract infection was diagnosed (mortality rate 8.9% in the EI group vs 18.7% in the NEI group, p=0.02).
Conclusion:
Both the EI and NEI groups demonstrated similar 14-day mortality. Post hoc subgroup analysis revealed a mortality benefit in patients in the EI group who had infectious organisms identified or were diagnosed with respiratory tract infections.
More Related Videos
 05:39
Author Spotlight: A Non-Intubated Video-Assisted Thoracoscopic Surgery with Multimodal Analgesia and Sevoflurane Inhalation Anesthesia
Published on: May 26, 2023
 09:17
Use of a Central Venous Line for Fluids, Drugs and Nutrient Administration in a Mouse Model of Critical Illness
Published on: May 2, 2017
Related Concept Videos
 01:28
Acute Pyelonephritis II: Diagnostic Studies and Management
 01:24
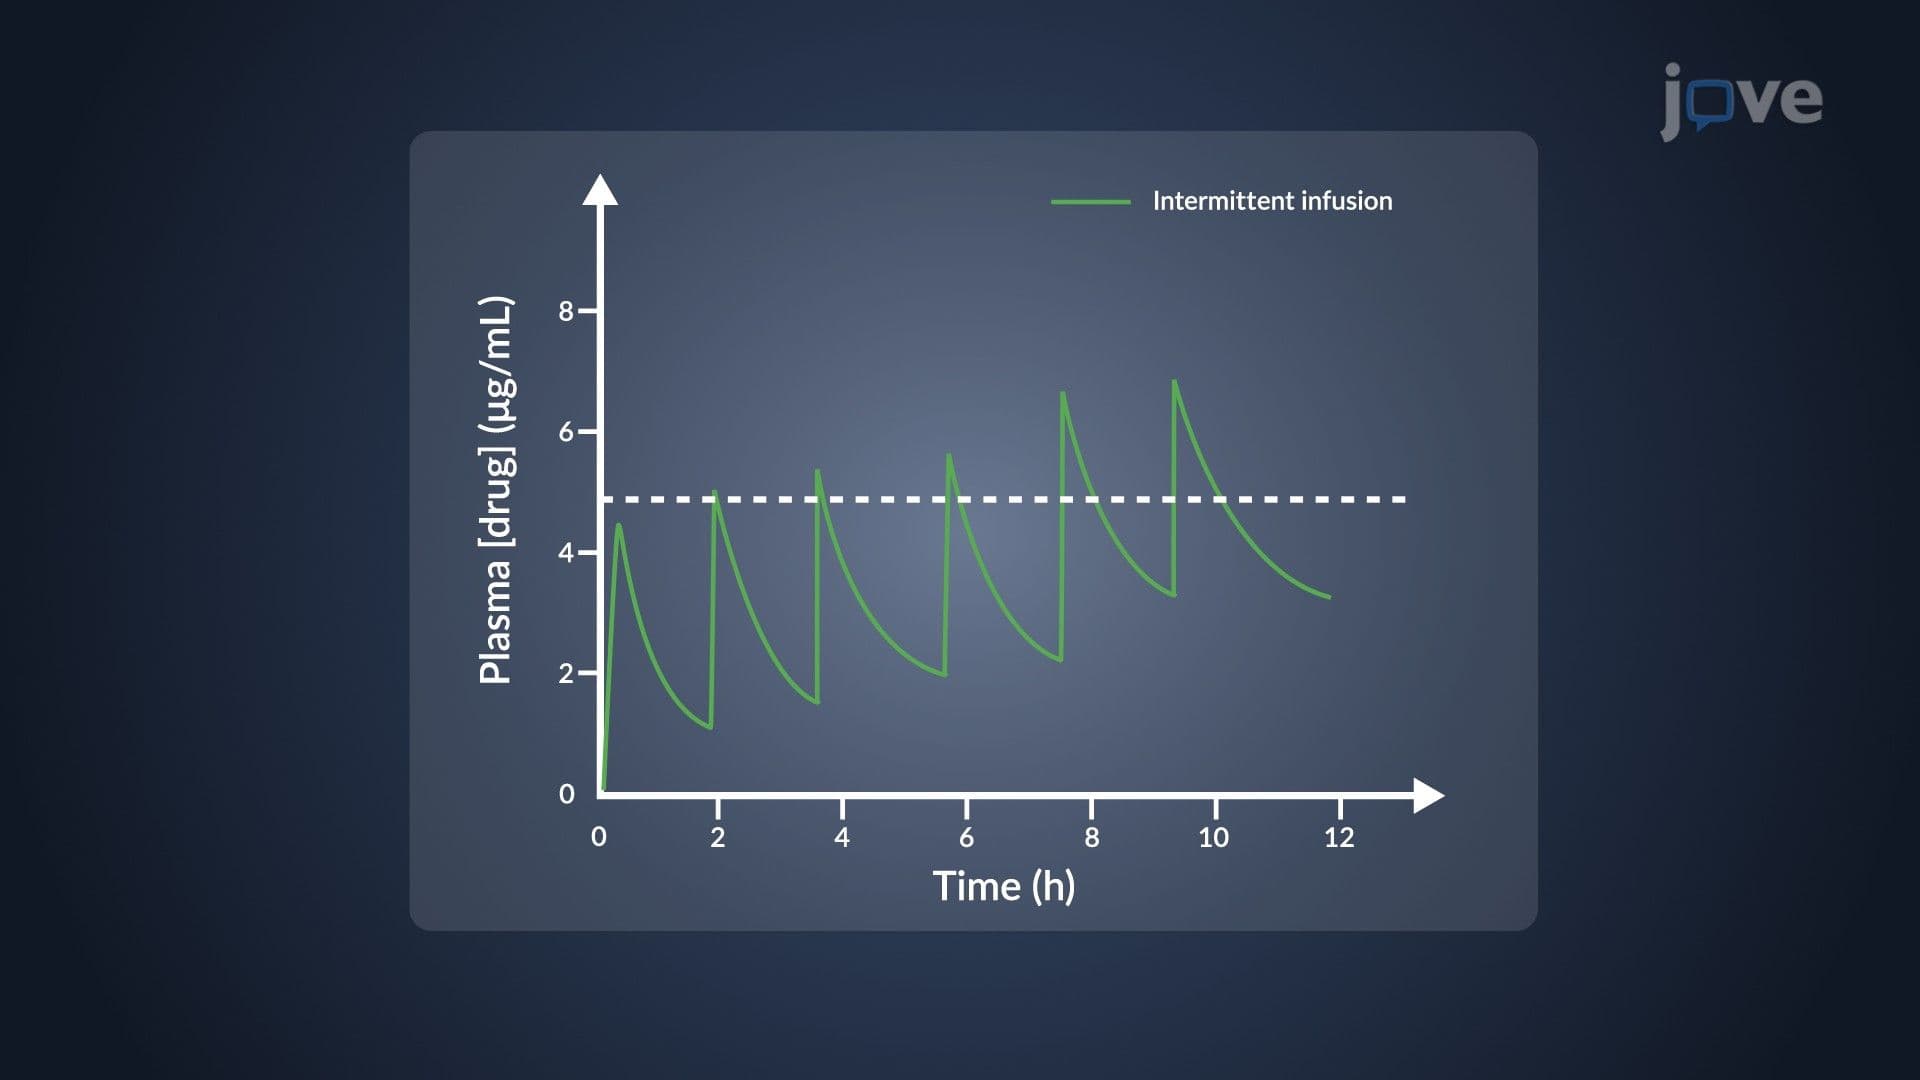
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:28
Pneumonia IV: Management
Bacterial Pneumonia Treatment
For bacterial pneumonia, antibiotics serve as the cornerstone of therapy. Initial treatment often begins with empirical antibiotics, tailored to the anticipated causative organism and adjusted based on culture results. Key antibiotic choices include:
 01:22
Pharmaceutical Alternatives: Stability-Related Therapeutic Nonequivalence
 01:15
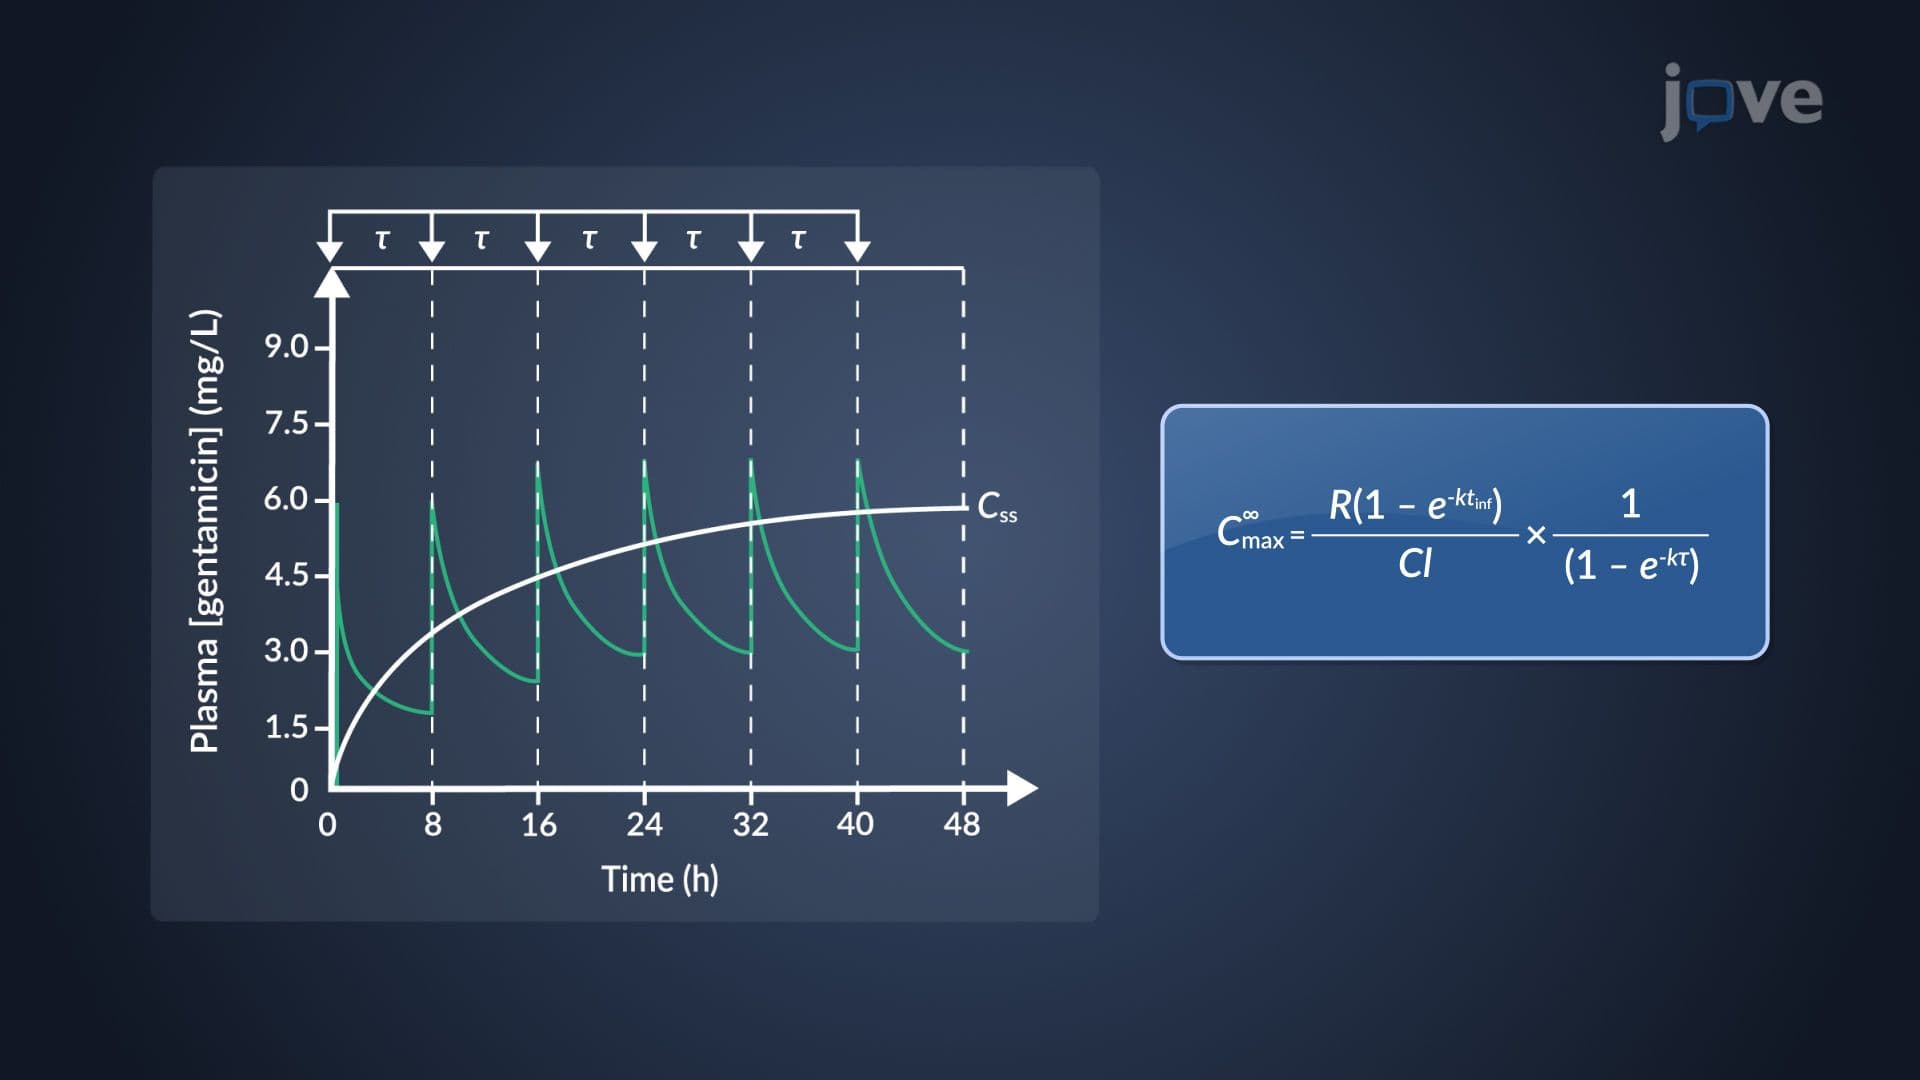
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:28
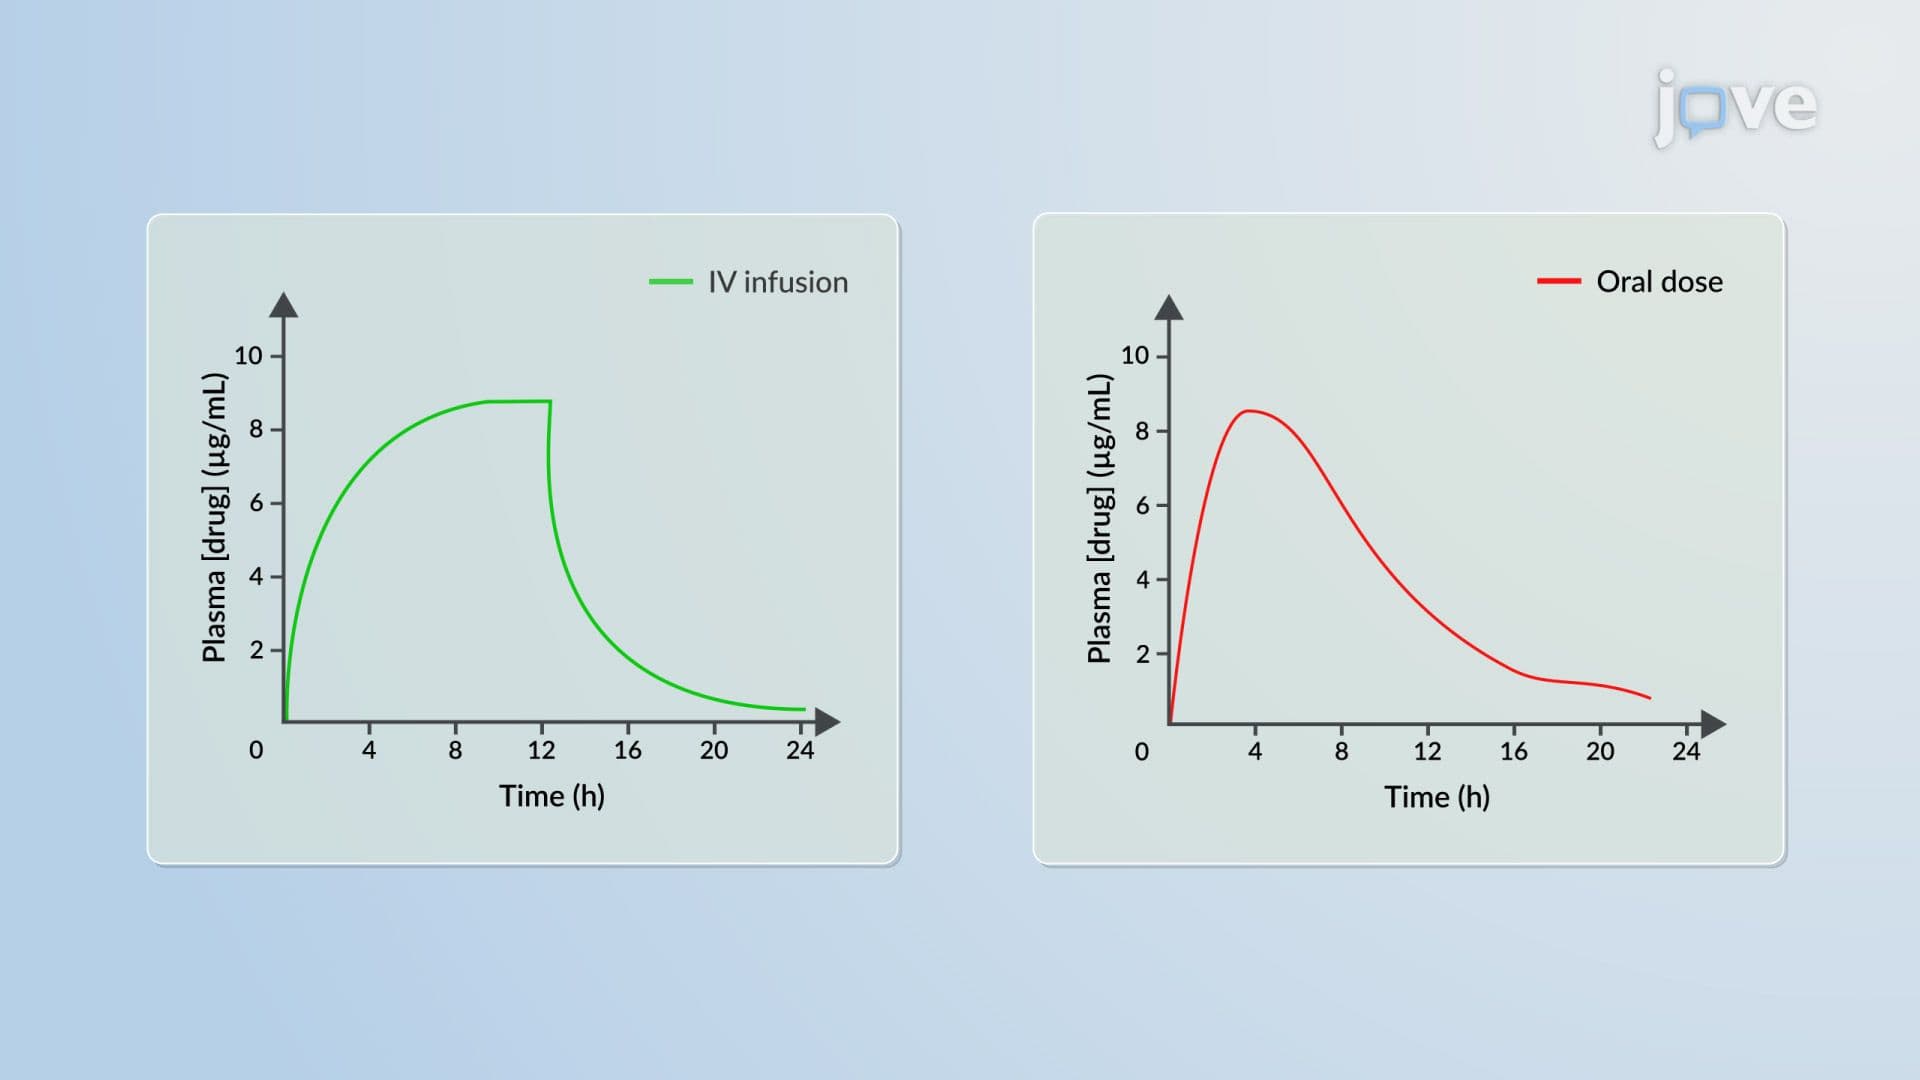
IV Infusion to Oral Dosing: Conversion Methods