Related Experiment Video
Updated: Mar 11, 2026


Author Spotlight: Developing a Rat Model for Pouchitis Research and Treatment
Published on: May 31, 2024
Variables associated with loss of ileoanal pouches constructed in childhood
Khaled Abdelaal1, Bruce Jaffray1
1Department of paediatric surgery, The Great North Children's Hospital, Queen Victoria Road, Newcastle upon Tyne NE1 4LP.

Insights
In children undergoing restorative procto- colectomy, 13% ultimately require a permanent ileostomy. Pre-operative fecal incontinence is a key risk factor for pouch loss, increasing the likelihood of needing a permanent ileostomy.
Area of Science:
- Pediatric Surgery
- Gastroenterology
- Colorectal Surgery
Background:
- Restorative procto- colectomy with ileoanal pouch creation is a complex procedure for pediatric patients with various colorectal conditions.
- Understanding factors influencing pouch survival is crucial for optimizing surgical outcomes and patient quality of life.
Purpose of the Study:
- To determine the incidence of ileoanal pouch loss in children following restorative procto- colectomy.
- To identify preoperative and operative variables associated with pouch excision or permanent diversion.
Main Methods:
- A retrospective analysis of 103 children who underwent ileoanal pouch surgery.
- Logistic regression (univariate and multivariate) was employed to assess potential risk factors for pouch loss.
- Kaplan-Meier graphs were used to illustrate pouch survival rates.
Main Results:
- 13% of children (13 out of 103) required pouch excision or permanent diversion.
- Pre-operative fecal incontinence (Odds Ratio 21) and anastomotic leak were significantly associated with pouch loss.
- On multivariate analysis, only pre-operative fecal incontinence remained a significant predictor of pouch excision/diversion.
Conclusions:
- Fecal incontinence prior to restorative procto- colectomy in children is a significant risk factor and may be a relative contraindication.
- Anastomotic leak following surgery increases the probability of subsequent pouch excision.
- Approximately 13% of pediatric patients may ultimately require a permanent ileostomy after this procedure.
Aims:
To quantify the incidence of loss of an ileoanal pouch in children and to identify variables associated this event.
Methods:
Logistic regression of possible explanatory variables: age, sex, indication for procto-colectomy, pre-operative continence status, use of immunosuppressive drugs, open or laparoscopic surgery, number of stages, anastomotic leak, operative complication excluding anastomotic leak, performance of revisional surgery, albumin concentration and platelet count at time of surgery, rank order in series. Univariate logistic regression was used to identify significant variables which were then assessed in a multivariate model and construction of Kaplan-Meier graphs.
Results:
103 children, 56 girls, underwent ileoanal pouch at median age 14years (SD 3.7). Indications and mean age were: ulcerative colitis (n=71, 14years), polyposis syndromes (n=13, 15years), chronic idiopathic constipation (n=9, 11years), Hirschsprung's disease (n=4, 1year), Crohn's disease (n=2, 16years), and fibrosing colonopathy (n=2, 11years). 13 patients had their pouch excised or permanently diverted. Three patients had successful revisional pouch surgery. Only pre-operative fecal incontinence and anastomotic leak were significantly associated with pouch excision/diversion, however on multivariate analysis, only fecal incontinence remained significant, odds ratio 21 (95%CI 1.8-235, p=0.01). Pouch survival was significantly worse where there was fecal incontinence pre-operatively, p<0.0001 or an anastomotic leak, p<0.001.
Conclusions:
13% of children subjected to restorative procto-colectomy ultimately receive a permanent ileostomy. Fecal incontinence prior to surgery is a relative contra-indication. Anastomotic leak increases the probability of later pouch excision.
Level Of Evidence:
IV.


Related Concept Videos
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:27
Histology of the Small Intestine
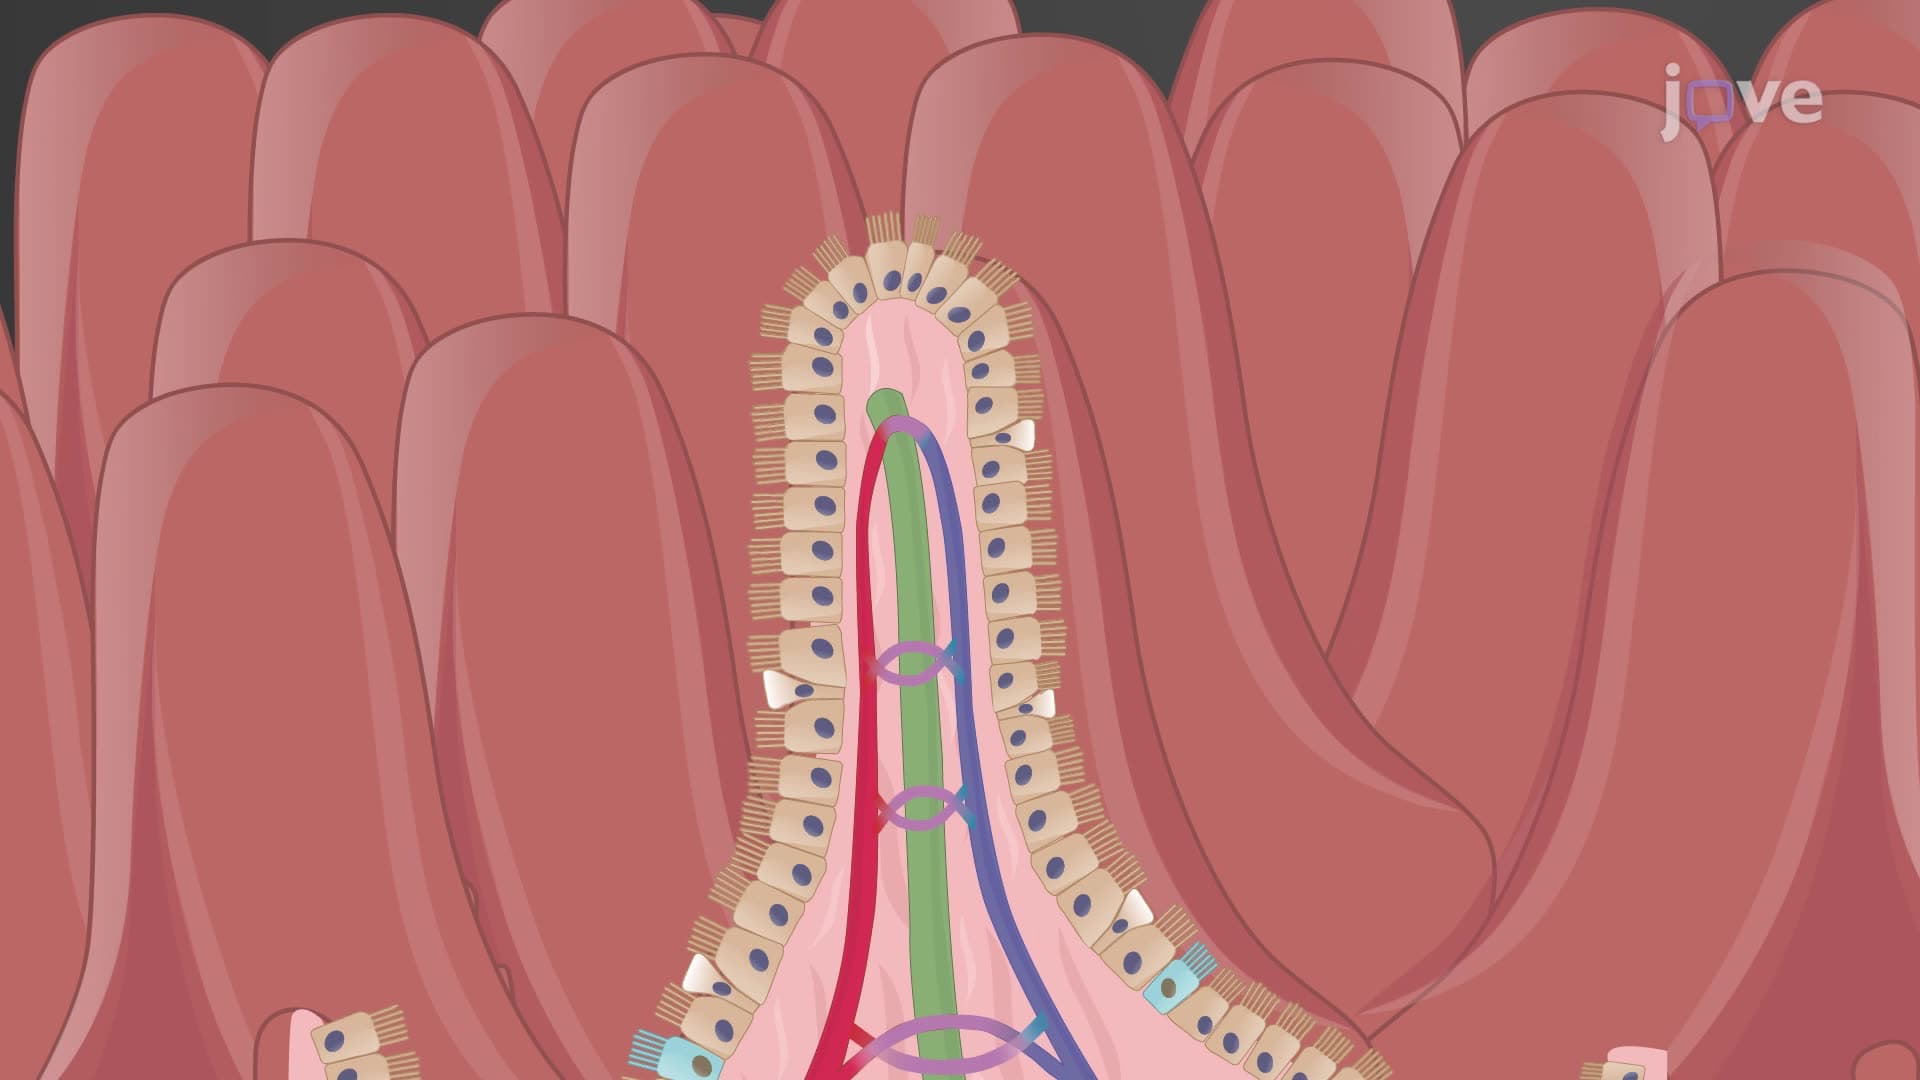
The intestinal lining features transverse folds called circular folds, each housing fingerlike projections known as intestinal villi. These villi are covered by a layer of simple columnar epithelium, also referred to as...
 01:24
Ostomy Care
An ostomy is a surgical procedure that creates an artificial opening from the intestines to the outside of the body, allowing for the rerouting of effluent. This opening is known as a stoma. A stoma usually protrudes above the skin surface, appearing pink or red, moist, and round, and it lacks nerve sensations.
There are different types of ostomies, including colostomies, ileostomies, and urostomies:
 01:17
Chronic Bowel Disorders: Introduction
Irritable Bowel Syndrome (IBS) is a common disorder affecting the gastrointestinal tract. The distinctive feature is recurrent abdominal pain associated with altered bowel movements, manifesting as constipation, diarrhea, or fluctuating between both. The...
 01:22
Appendicitis-I: Introduction
Etiology: Appendicitis can arise from various causes, primarily rooted in the obstruction of the appendix lumen. Factors contributing to this obstruction include fecal accumulation, lymphoid hyperplasia and, in...
 01:30
Inflammatory Bowel Disease II: Crohn's Disease
Inflammatory bowel disease, commonly known as IBD, refers to a collection of disorders that lead to persistent inflammation of the gastrointestinal tract. The two types of IBD are ulcerative colitis, which impacts the colon, and Crohn's disease, which can involve any part of the gastrointestinal segment.
Crohn's disease
Crohn's disease is a chronic, systemic inflammatory bowel disease (IBD) that predominantly affects the gastrointestinal tract. It is marked by...