Related Experiment Video
Updated: Mar 11, 2026
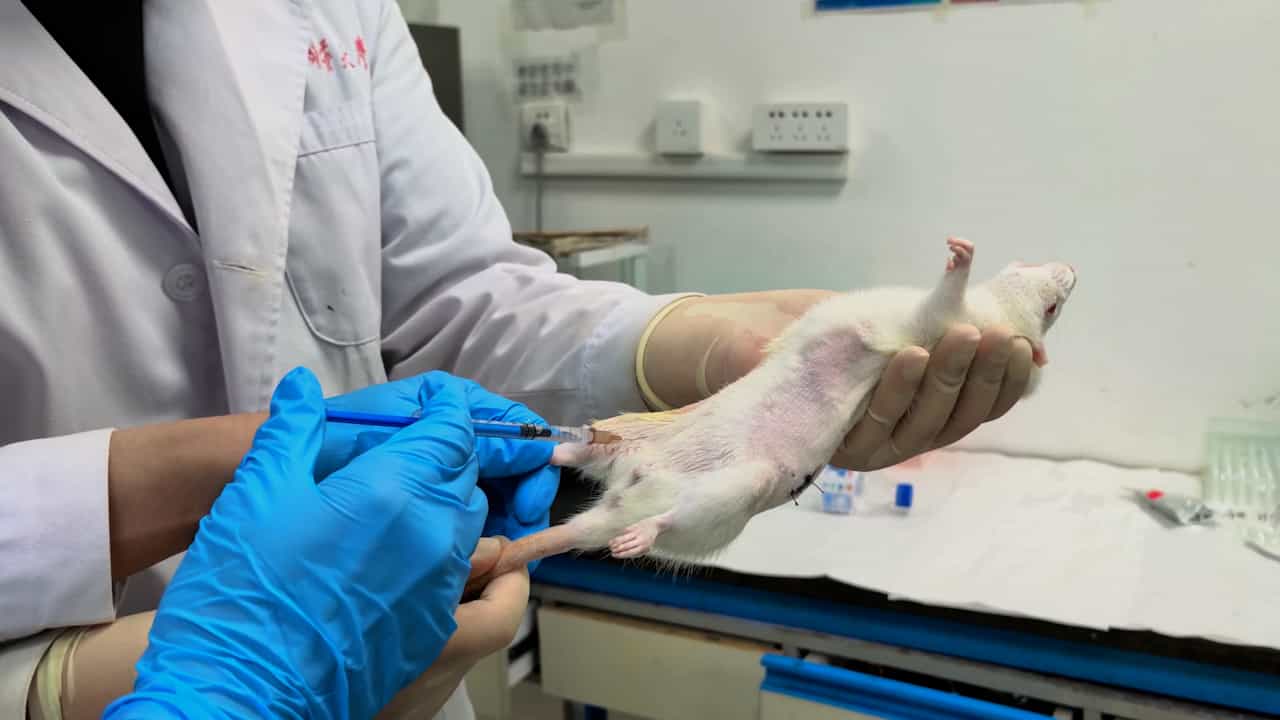

The Creation of a Rat Model for Osteosarcopenia via Ovariectomy
Published on: February 21, 2025
Sarcopenia among patients receiving hemodialysis: weighing the evidence
Piyawan Kittiskulnam1,2, Juan J Carrero3, Glenn M Chertow4
1Division of Nephrology, University of California San Francisco and San Francisco VA Medical Center, CA, USA.

Background:
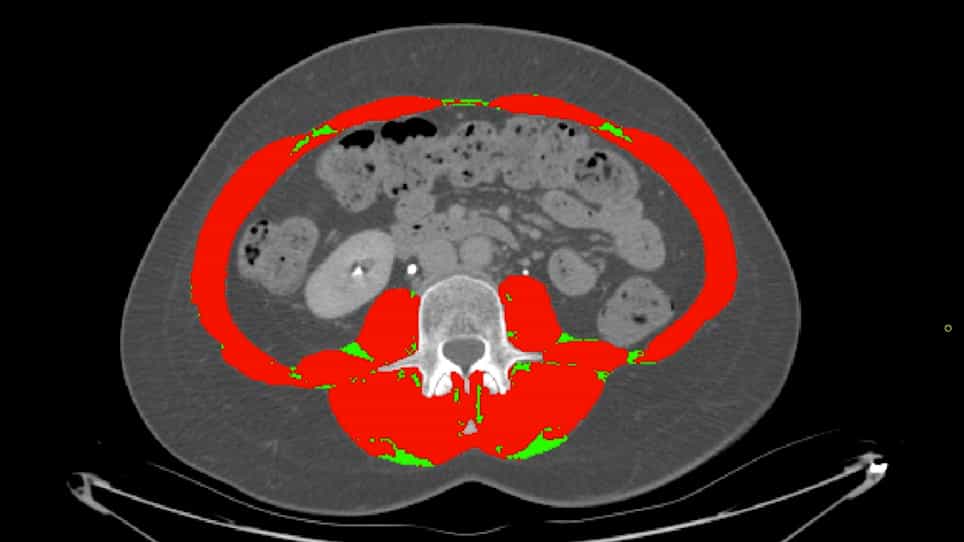
There is no consensus on how best to define low muscle mass in patients with end-stage renal disease. Use of muscle mass normalized to height-squared has been suggested by geriatric societies but may underestimate sarcopenia, particularly in the setting of excess adiposity. We compared four definitions of low muscle mass in a prevalent hemodialysis cohort.
Methods:
ACTIVE/ADIPOSE enrolled prevalent patients receiving hemodialysis from the San Francisco and Atlanta areas from June 2009 to August 2011. Whole-body muscle mass was estimated using bioelectrical impedance spectroscopy, performed before a midweek dialysis session (n = 645; age 56.7 ± 14.5 years, 41% women). We defined low muscle mass as muscle mass of 2SD or more below sex-specific bioelectrical impedance spectroscopy-derived means for young adults (18-49 years) from National Health and Nutrition Examination Survey and indexed to height2 , body weight (percentage), body surface area (BSA) by the DuBois formula, or Quételet's body mass index (BMI). We compared prevalence of low muscle mass among the four methods and assessed their correlation with strength and physical performance.
Results:
The prevalence of low muscle mass ranged from 8 to 32%. Muscle mass indexed to height2 classified the smallest percentage of patients as having low muscle mass, particularly among women, whereas indexing by BSA classified the largest percentage. Low muscle mass/height2 was present almost exclusively among normal or underweight patients, whereas indexing to body weight and BMI classified more overweight and obese patients as having low muscle mass. Handgrip strength was lower among those with low muscle mass by all methods except height2 . Handgrip strength was directly and modestly correlated with muscle mass normalized by percentage of body weight, BSA, and BMI (ρ = 0.43, 0.56, and, 0.64, respectively) and less so with muscle/height2 (ρ = 0.31, P < 0.001). The difference in grip strength among patients with low vs. normal muscle mass was largest according to muscle/BMI (-6.84 kg, 95% CI -8.66 to -5.02, P < 0.001). There were significant direct correlations of gait speed with muscle mass indexed to percentage of body weight, BSA, and BMI but not with muscle mass indexed to height2 .
Conclusions:
Skeletal muscle mass normalized to height2 may underestimate the prevalence of low muscle mass, particularly among overweight and obese patients on hemodialysis. Valid detection of sarcopenia among obese patients receiving hemodialysis requires adjustment for body size.
Related Concept Videos
 01:24
Hemodialysis II: Procedure and Complications
 01:28
Chronic Kidney Disease III: Interprofessional Care
 01:25
Hemodialysis III: Nursing Management
 01:27
Dialysis
Acute kidney injury develops suddenly and can be caused by pre-renal causes (e.g., hypovolemia, shock), intrinsic renal causes (e.g., acute tubular necrosis), or post-renal causes (e.g., urinary obstruction). In contrast, chronic renal failure progresses gradually over time and is often...
 01:15
Dialysis
 01:25
Hemodialysis I: Introduction