Liver stiffness predicts variceal bleeding in HIV/HCV-coinfected patients with compensated cirrhosis
Related Experiment Video
Updated: Mar 10, 2026

Measurement of Liver Stiffness Using Atomic Force Microscopy Coupled with Polarization Microscopy
Published on: July 20, 2022
Nicolás Merchante1, Antonio Rivero-Juárez, Francisco Téllez
1aUnidad Clínica de Enfermedades Infecciosas y Microbiología, Instituto de Biomedicina de Sevilla (IBiS), Hospital Universitario de Valme, Sevilla bUnidad de Enfermedades Infecciosas, Instituto Maimónides de Investigación Biomédica de Córdoba (IMIBIC), Hospital Universitario Reina Sofía, Universidad de Córdoba (UCO), Córdoba cUnidad de Gestión Clínica de Enfermedades Infecciosas y Microbiología, Hospital de La Línea de la Concepción, AGS Campo de Gibraltar, Cádiz dUnidad de Gestión Clínica de Enfermedades Infecciosas, Complejo Hospitalario de Huelva, Huelva eUnidad de Enfermedades Infecciosas, Hospital Universitario Virgen Macarena, Sevilla fUnidad de Gestión Clínica de Enfermedades Infecciosas, Hospital Virgen de la Victoria, Complejo Hospitalario de Málaga, Málaga gUnidad de Enfermedades Infecciosas, Complejo Hospitalario de Jaén, Jaén, Spain.

Insights
Liver stiffness measurement effectively predicts portal hypertensive gastrointestinal bleeding (PHGB) risk in HIV/HCV-coinfected patients. A liver stiffness below 21 kPa safely excludes PHGB, allowing avoidance of upper gastrointestinal endoscopy (UGE).
Area of Science:
- Hepatology
- Infectious Diseases
- Gastroenterology
Background:
- Hepatitis C virus (HCV) and human immunodeficiency virus (HIV) coinfection often leads to liver cirrhosis.
- Esophageal varices are a common complication, posing a bleeding risk.
- Upper gastrointestinal endoscopy (UGE) is used for screening, but its routine use is debated.
Purpose of the Study:
- To evaluate liver stiffness as a predictor of portal hypertensive gastrointestinal bleeding (PHGB).
- To assess the safety of avoiding UGE in HIV/HCV-coinfected patients with compensated cirrhosis based on liver stiffness measurements.
Main Methods:
- A prospective study of 446 HIV/HCV-coinfected patients with newly diagnosed compensated cirrhosis.
- Liver stiffness was measured using transient elastography.
- Patients were followed for the development of PHGB, with UGE use changing based on liver stiffness thresholds.
Main Results:
- No patient with baseline liver stiffness below 21 kPa developed PHGB during a median follow-up of 49 months.
- The negative predictive value of liver stiffness < 21 kPa for PHGB was 100%.
- All 15 patients who experienced PHGB had baseline liver stiffness of at least 21 kPa.
Conclusions:
- Liver stiffness measurement is a reliable, non-invasive tool to identify patients at very low risk of PHGB.
- A liver stiffness threshold of 21 kPa can safely guide the decision to forgo UGE screening for esophageal varices in this population.
- This strategy can reduce healthcare costs and patient burden without compromising safety.
Background:
A liver stiffness below 21 kPa has a high negative predictive value to exclude the presence of esophageal varices at risk of bleeding in HIV/hepatitis C virus (HCV)-coinfected patients. Consequently, upper gastrointestinal endoscopy (UGE) for the screening of esophageal varices could be avoided in these patients. However, this strategy has not been widely accepted due to concerns about its safety.
Objective:
To assess the ability of liver stiffness to predict the risk of portal hypertensive gastrointestinal bleeding (PHGB) in HIV/HCV-coinfected patients with compensated cirrhosis.
Methods:
Prospective study of 446 HIV/HCV-coinfected patients with a new diagnosis of cirrhosis and no previous decompensation. All patients underwent a UGE for the screening of esophageal varices at entry in the cohort before November 2009. From this date, UGE was not recommended in patients with liver stiffness below 21 kPa. The time from diagnosis of cirrhosis to the emergence of PHGB was evaluated.
Results:
After a median (quartile1-quartile3) follow-up of 49 (25-68) months, 15 (3.4%, 95% confidence interval 1.7-5%) patients developed a first PHGB episode. In all cases, baseline liver stiffness was at least 21 kPa. Thus, the negative predictive value of a liver stiffness below 21 kPa to predict PHGB during follow-up was 100%. At the time of the bleeding episode, liver stiffness was above this threshold in all patients.
Conclusions:
Liver stiffness identifies HIV/HCV-coinfected patients with compensated cirrhosis with a very low risk of PHGB. In fact, no individual with liver stiffness below 21 kPa developed this outcome. Our results confirm that UGE can be safely spared in patients with liver stiffness below 21 kPa.

Related Concept Videos
 01:28
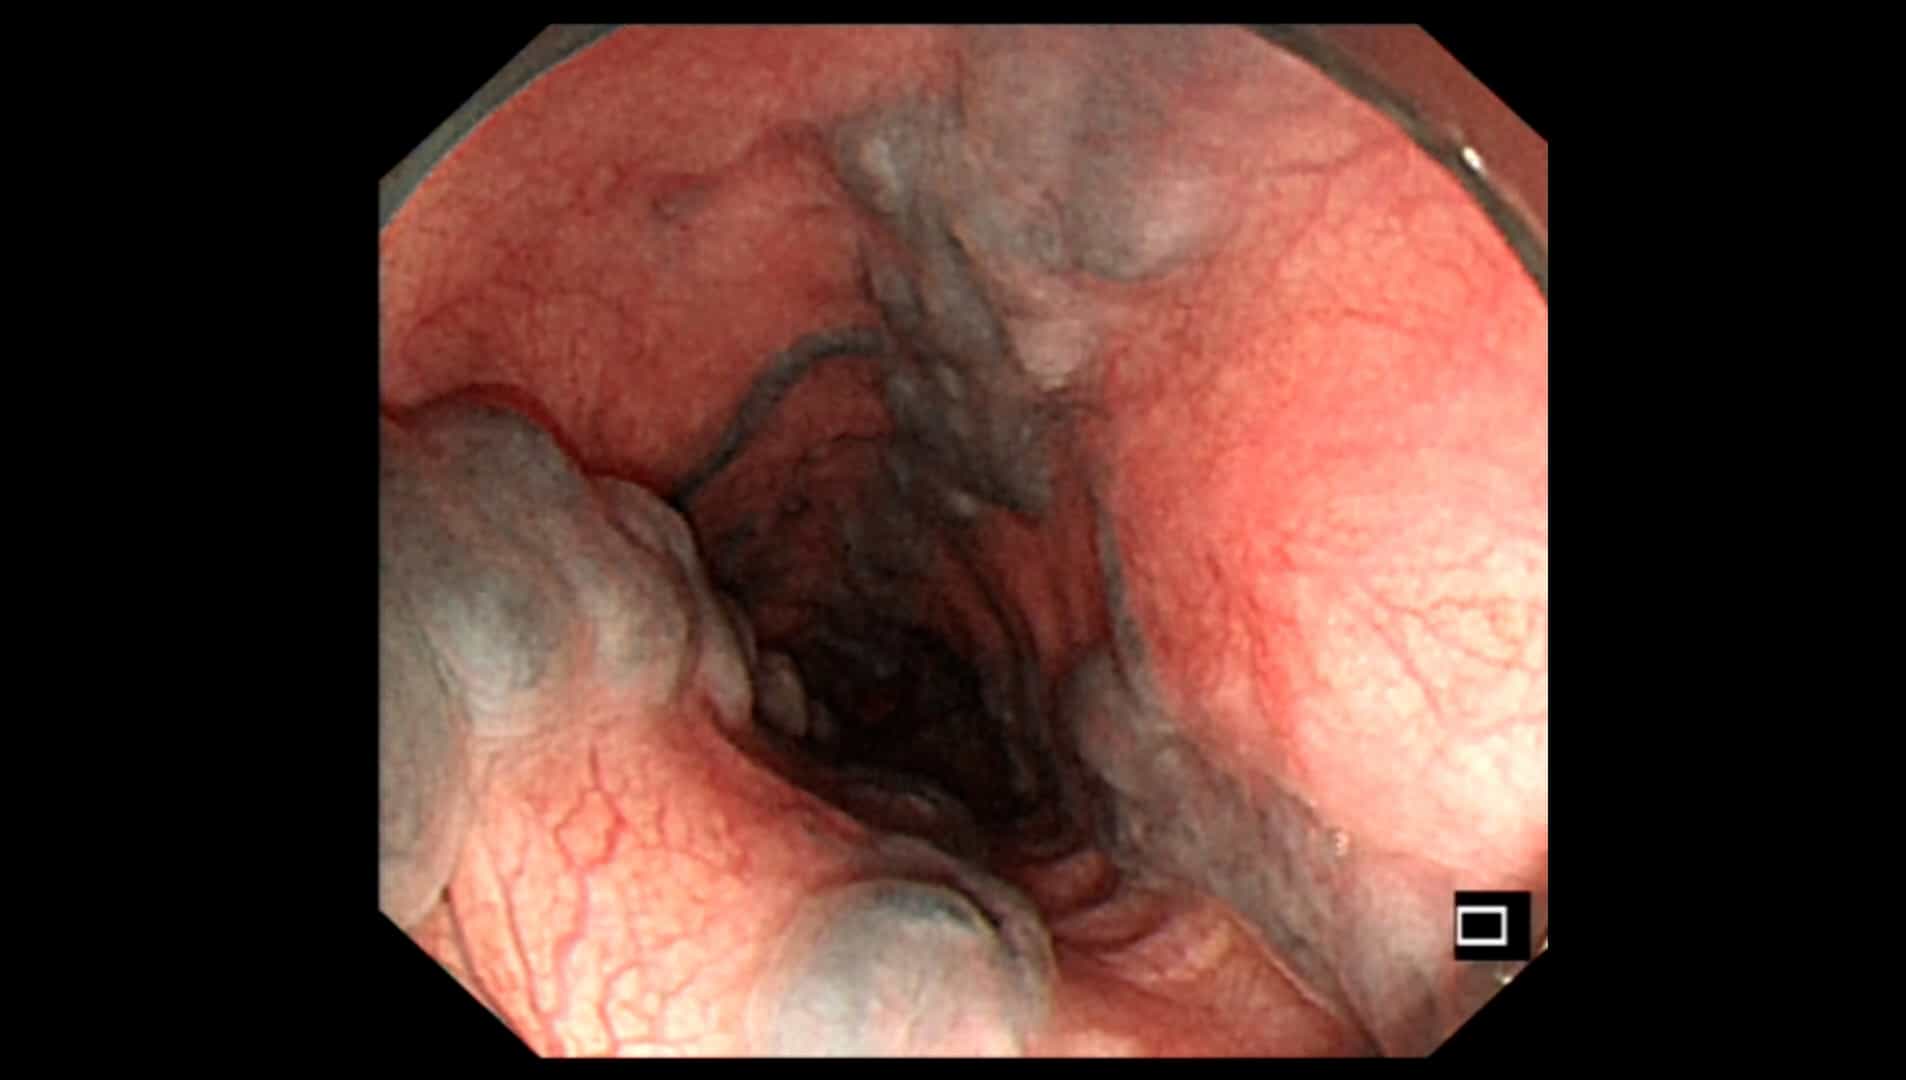
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...
 01:24
Esophageal Varices-I: Introduction
 01:26
Diseases of the Liver and Gallbladder
Cirrhosis is characterized by the scarring of hepatic lobules in the liver, which are replaced by fibrous tissue, affecting the liver's normal functioning. NAFLD, on the other hand, is caused by an excessive build-up of fat in the liver, not...
 01:27
Inflammatory Bowel Disease I: Ulcerative Colitis
Inflammatory bowel disease, or IBD, encompasses a group of disorders characterized by chronic inflammation or ulceration of the gastrointestinal tract.
Risk Factors
The exact cause of IBD remains unclear, although it is believed to be due to a mix of genetic, environmental, microbial, and immune factors. Genetic factors are significant in determining susceptibility to IBD, with family history being a critical risk factor. Individuals with a first-degree relative who has IBD are at...
 01:26
Effect of Hepatic Disease on Pharmacokinetics: Drug Dosing and Hepatic Blood Flow
 01:22
Effect of Hepatic Disease on Pharmacokinetics: Pathophysiologic Assessment and Liver Function Test