Related Experiment Video
Updated: Mar 10, 2026
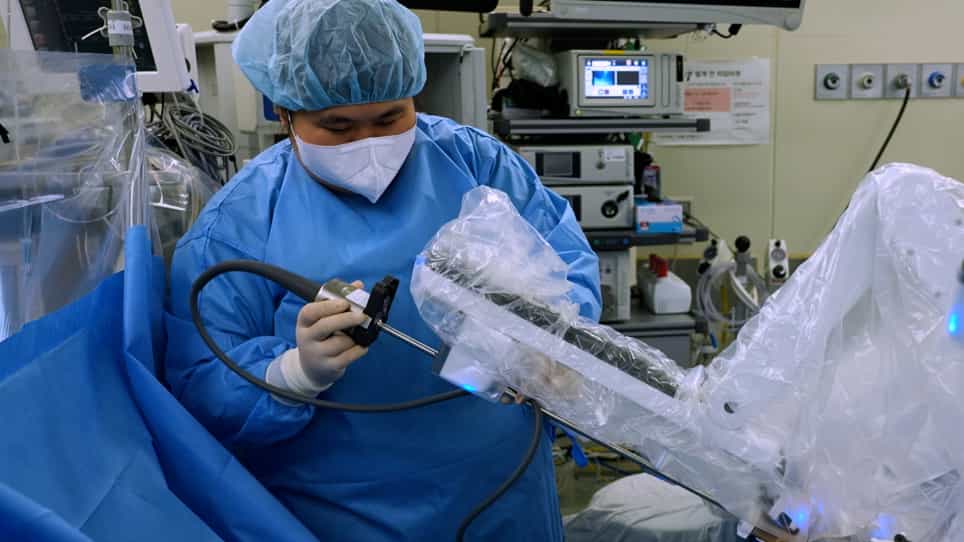

Robot-Assisted Kidney Transplantation
Published on: July 19, 2021
Risk Evaluation and Outcome of Pneumocystis jirovecii Pneumonia in Kidney Transplant Patients
S Brakemeier1, M Dürr1, F Bachmann1
1Charité Campus Mitte, Department of Internal Medicine, Division of Nephrology, Berlin, Germany.

Insights
Pneumocystis jirovecii pneumonia (PJP) is increasingly seen long after kidney transplants. This study found PJP outcomes were 13% mortality and 13% graft loss, highlighting risks in kidney transplant recipients.
Area of Science:
- Nephrology
- Infectious Diseases
- Immunology
Background:
- Pneumocystis jirovecii pneumonia (PJP) is a significant opportunistic infection in immunocompromised individuals, particularly kidney transplant recipients.
- While effective prophylaxis reduces early PJP incidence, long-term post-transplant PJP remains a concern.
- This study investigates the clinical course and outcomes of PJP in kidney transplant patients diagnosed beyond the immediate post-transplant period.
Purpose of the Study:
- To evaluate the incidence, clinical presentation, and outcomes of Pneumocystis jirovecii pneumonia (PJP) in kidney transplant recipients.
- To identify risk factors and patient characteristics associated with PJP in the long-term post-transplant period.
- To compare PJP risk in specific patient groups, including those undergoing ABO-incompatible transplantation or treated with belatacept.
Main Methods:
- Retrospective analysis of 23 kidney transplant patients diagnosed with PJP between 2010 and 2015.
- Comparison of PJP incidence and outcomes against control cohorts: general kidney transplant follow-up patients (n=575), ABO-incompatible transplant patients (n=45), and belatacept-treated patients (n=69).
- Assessment of clinical parameters including timing of PJP post-transplant, immunosuppression status, rejection therapy, lymphopenia, and respiratory function.
Main Results:
- Twenty-three kidney transplant patients developed PJP at a mean of 53.7 months post-transplant, with no patients on PJP prophylaxis.
- PJP was associated with a 13% mortality rate and 13% graft loss, resulting in 87% patient survival and 73.9% graft survival.
- Patients undergoing ABO-incompatible transplantation and those treated with belatacept demonstrated an increased risk for PJP, with contributing factors including age, low eGFR, and lymphopenia.
Conclusions:
- Long-term PJP in kidney transplant recipients carries significant morbidity and mortality, emphasizing the need for vigilant monitoring.
- ABO-incompatible transplantation and belatacept use are associated with an elevated risk of PJP, necessitating careful risk stratification and management.
- Severe lymphopenia at diagnosis is a key indicator of PJP risk and severity in kidney transplant patients.
Abstract:
Pneumocystis jirovecii pneumonia (PJP) affects immunocompromised patients. As a result of effective prophylaxis in the 1st months after kidney transplantation, PJP is increasingly diagnosed in the long term after transplantation. The present study evaluates course and outcome of PJP in a single transplant center from 2010 to 2015. Twenty-three patients presented with PJP at a mean of 53.7 ± 50.2 months after transplantation. Of these, 3 patients underwent ABO-incompatible (ABO-i) living-donor transplantation and 3 patients were treated with the use of belatacept. For risk estimation, 3 control cohorts were defined: a control group of all kidney transplant patients presenting for routine follow up (n = 575), all patients transplanted in an ABO-i setting (n = 45), and all patients treated with belatacept in our clinic (n = 69). Mortality in patients with PJP was 3/23 (13%) and graft loss after PJP was 3/23 (13%) resulting in patient and graft survivals of 87% and 73.9%, respectively. All patients were without PJP prophylaxis at time of diagnosis. Five of the 23 PJP patients received rejection therapy or dose escalation of immunosuppression 6 months before PJP infection, and 1 patient experienced acute rejection within 6 months after PJP treatment. In the course of PJP, 8 patients developed acute respiratory insufficiency. At time of PJP diagnosis, patients presented with severe lymphopenia (mean ± SD lymphocyte count, 0.64 ± 0.27/nL; normal range: 1.5-3/nL). Patients after ABO-i transplantation, as well as patients treated with belatacept, showed an increased risk for PJP (7.3% and 4.3%, respectively); however, in belatacept patients, other risk factors, such as age, low estimated glomerular filtration rate (eGFR), and lymphopenia seemed to contribute to this increased risk.


Related Concept Videos
 01:28
Kidney Transplant I: Introduction
 01:16
Kidney Transplant III: Nursing Management
 01:26
Kidney Transplant II: Surgical Procedure
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
 01:22
Acute Kidney Injury I: Introduction
 01:29
Acute Kidney Injury III: Clinical Manifestations