Related Experiment Video
Updated: Mar 10, 2026


Inverse Probability of Treatment Weighting Propensity Score using the Military Health System Data Repository and National Death Index
Published on: January 8, 2020
Quantifying Geographic Variation in Health Care Outcomes in the United States before and after Risk-Adjustment
Barry L Rosenberg1, Joshua A Kellar1, Anna Labno1
1The Boston Consulting Group, Boston, Massachusetts, United States of America.

Background:
Despite numerous studies of geographic variation in healthcare cost and utilization at the local, regional, and state levels across the U.S., a comprehensive characterization of geographic variation in outcomes has not been published. Our objective was to quantify variation in US health outcomes in an all-payer population before and after risk-adjustment.
Methods And Findings:
We used information from 16 independent data sources, including 22 million all-payer inpatient admissions from the Healthcare Cost and Utilization Project (which covers regions where 50% of the U.S. population lives) to analyze 24 inpatient mortality, inpatient safety, and prevention outcomes. We compared outcome variation at state, hospital referral region, hospital service area, county, and hospital levels. Risk-adjusted outcomes were calculated after adjusting for population factors, co-morbidities, and health system factors. Even after risk-adjustment, there exists large geographical variation in outcomes. The variation in healthcare outcomes exceeds the well publicized variation in US healthcare costs. On average, we observed a 2.1-fold difference in risk-adjusted mortality outcomes between top- and bottom-decile hospitals. For example, we observed a 2.3-fold difference for risk-adjusted acute myocardial infarction inpatient mortality. On average a 10.2-fold difference in risk-adjusted patient safety outcomes exists between top and bottom-decile hospitals, including an 18.3-fold difference for risk-adjusted Central Venous Catheter Bloodstream Infection rates. A 3.0-fold difference in prevention outcomes exists between top- and bottom-decile counties on average; including a 2.2-fold difference for risk-adjusted congestive heart failure admission rates. The population, co-morbidity, and health system factors accounted for a range of R2 between 18-64% of variability in mortality outcomes, 3-39% of variability in patient safety outcomes, and 22-70% of variability in prevention outcomes.
Conclusion:
The amount of variability in health outcomes in the U.S. is large even after accounting for differences in population, co-morbidities, and health system factors. These findings suggest that: 1) additional examination of regional and local variation in risk-adjusted outcomes should be a priority; 2) assumptions of uniform hospital quality that underpin rationale for policy choices (such as narrow insurance networks or antitrust enforcement) should be challenged; and 3) there exists substantial opportunity for outcomes improvement in the US healthcare system.


Related Concept Videos
 01:23
Types of Biopharmaceutical Studies: Controlled and Non-Controlled Approaches
Non-controlled studies, commonly employed for initial exploration, lack a control group, rendering them susceptible to biases and external influences. In contrast,...
 01:25
Strategies for Assessing and Addressing Confounding
Confounding can be addressed at both the design phase of a study and through analytical methods after data...
 01:52
Regression Toward the Mean
 01:20
Comparing the Survival Analysis of Two or More Groups
 01:12
Relative Risk
 01:11
Variability: Analysis
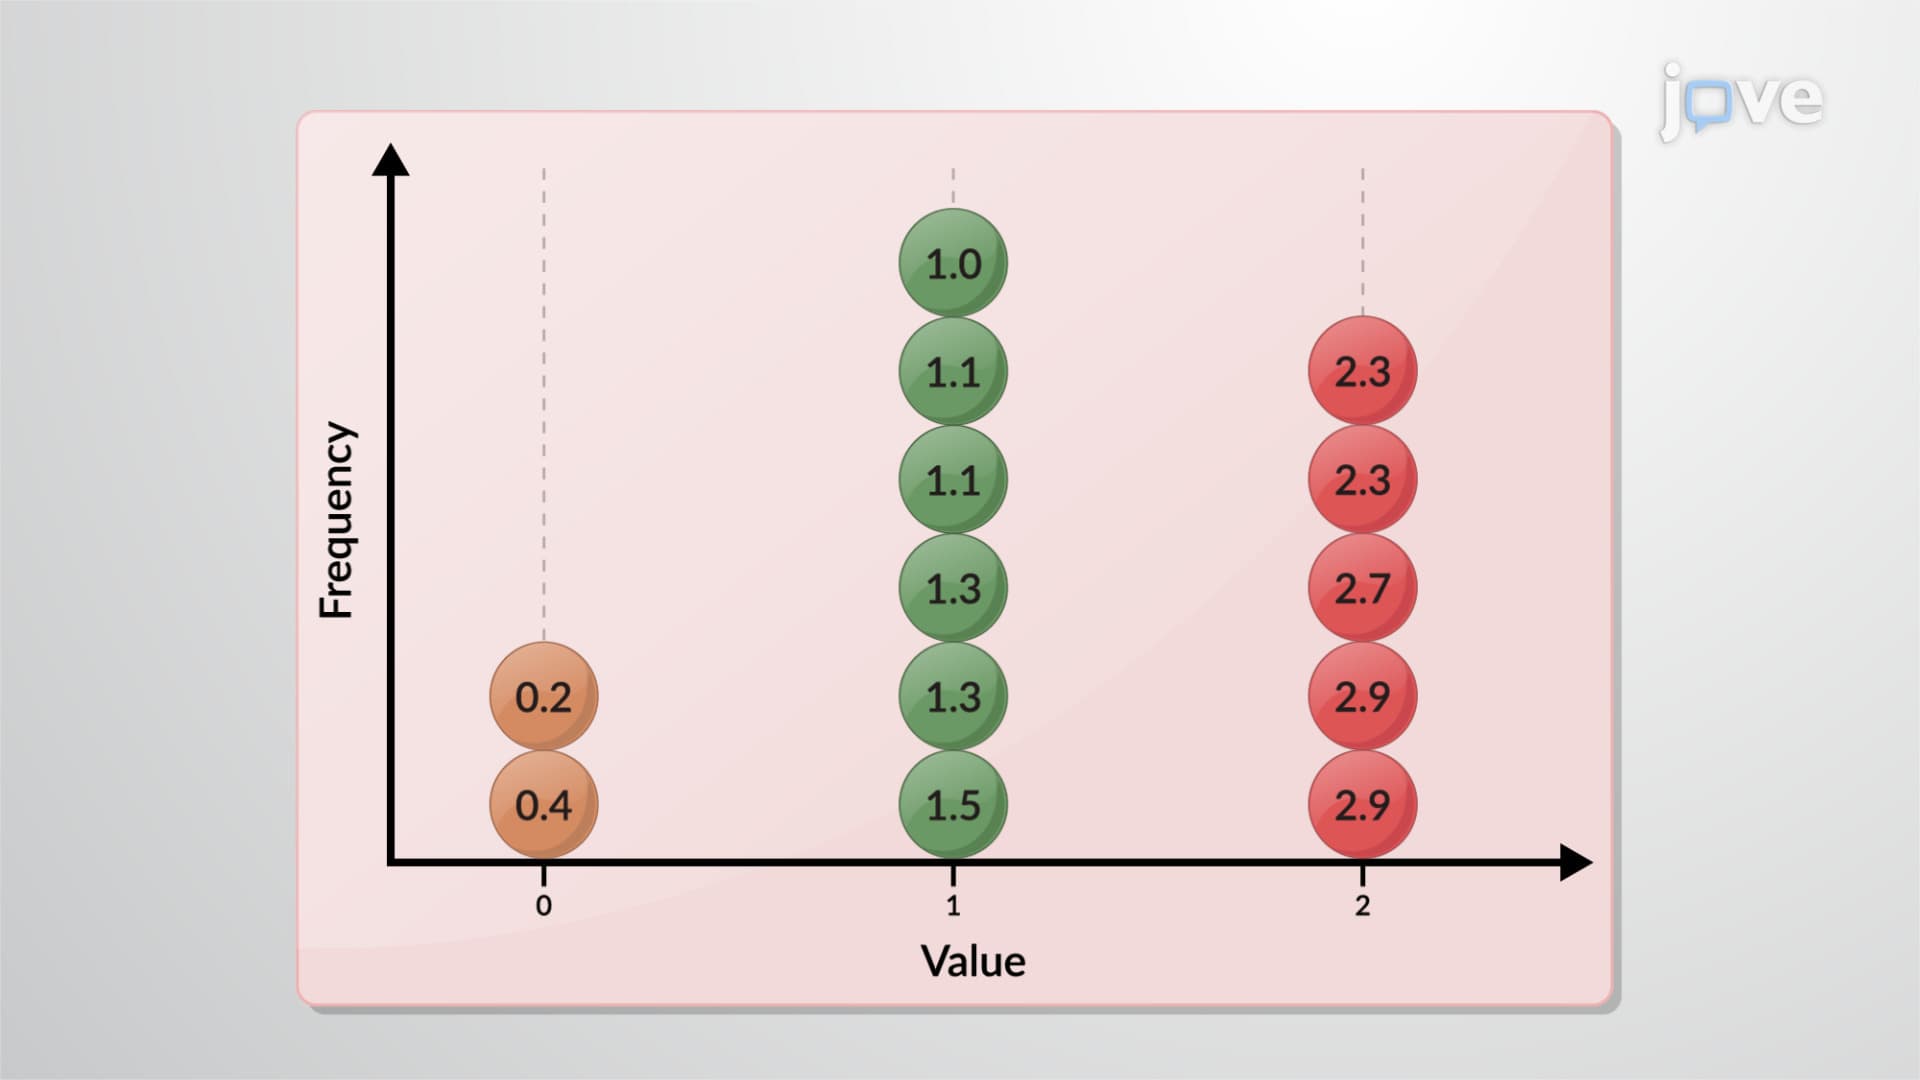
The range is a simple measure of variability, indicating the difference between the highest and...