Related Experiment Video
Updated: Mar 10, 2026


ADSC-sheet Transplantation to Prevent Stricture after Extended Esophageal Endoscopic Submucosal Dissection
Published on: February 10, 2017
Risk factors and management for pyloric stenosis occurred after endoscopic submucosal dissection adjacent to pylorus
Jae Un Lee1, Moon Sik Park, So Hee Yun
1Division of Gastroenterology, Department of Internal Medicine, Presbyterian Medical Center, Jeonju, Korea.

Abstract:
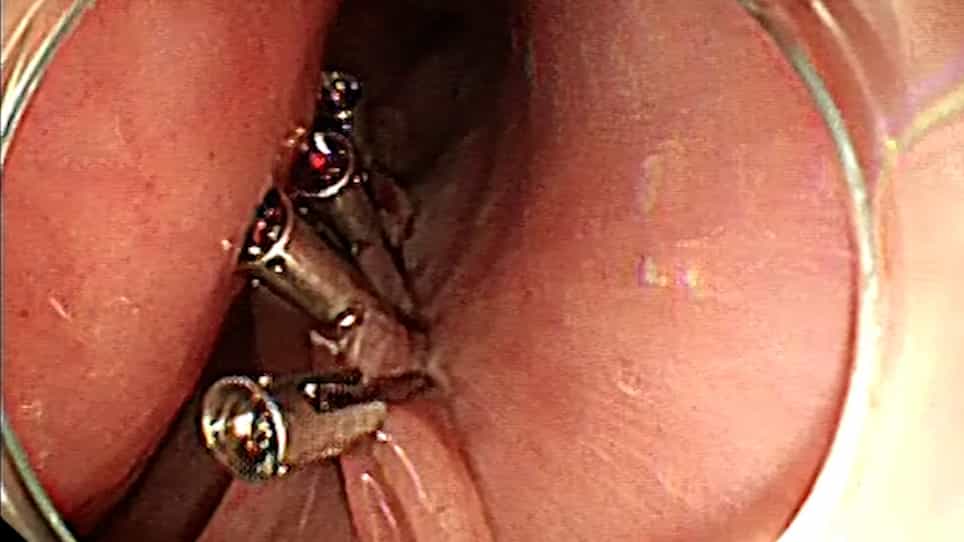
Endoscopic submucosal dissection (ESD) has been widely accepted as a curative treatment for gastric neoplasm. Pyloric stenosis is a chronic complication that can be caused by ESD. The aim of this study is to clarify the risk factors and management for pyloric stenosis. From January 2004 to January 2014, a total of 126 patients who underwent ESD adjacent to pylorus were reviewed retrospectively. Pyloric mucosal defect was defined as when any resection margin of ESD was involved in the pyloric ring. Pyloric stenosis was defined as when a conventional endoscope could not be passed to the duodenum. Among the 126 patients, pyloric stenosis was identified in 9. In a univariate analysis, pyloric stenosis was more common in older patients (P < 0.05) and in lesions with resections over 75% of the pyloric ring circumference (P < 0.001). In a multivariate analysis, the factor that was associated with pyloric stenosis was the extent of the pyloric ring dissection (P < 0.001). Four of the 9 patients with pyloric stenosis had mild dyspepsia, and the others had gastric outlet obstruction symptoms. The 5 symptomatic patients underwent endoscopic balloon dilation (EBD), and the frequency of EBD was 1 to 8 times. The asymptomatic patients were treated conservatively. The incidence of pyloric stenosis was higher in lesions with resections over 75% of the pyloric ring circumference. Although EBD was an effective treatment for pyloric stenosis, conservative management was also helpful in patients who had mild symptoms.
Related Concept Videos
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure...
 01:30
Peptic Ulcer Disease I: Introduction
An acute ulcer, marked by superficial erosion and minimal inflammation, swiftly resolves upon identifying and addressing the underlying cause. In contrast, a chronic ulcer persists, potentially eroding through the muscular wall and forming fibrous tissue.
Peptic ulcers can also be...