Related Experiment Video
Updated: Mar 10, 2026
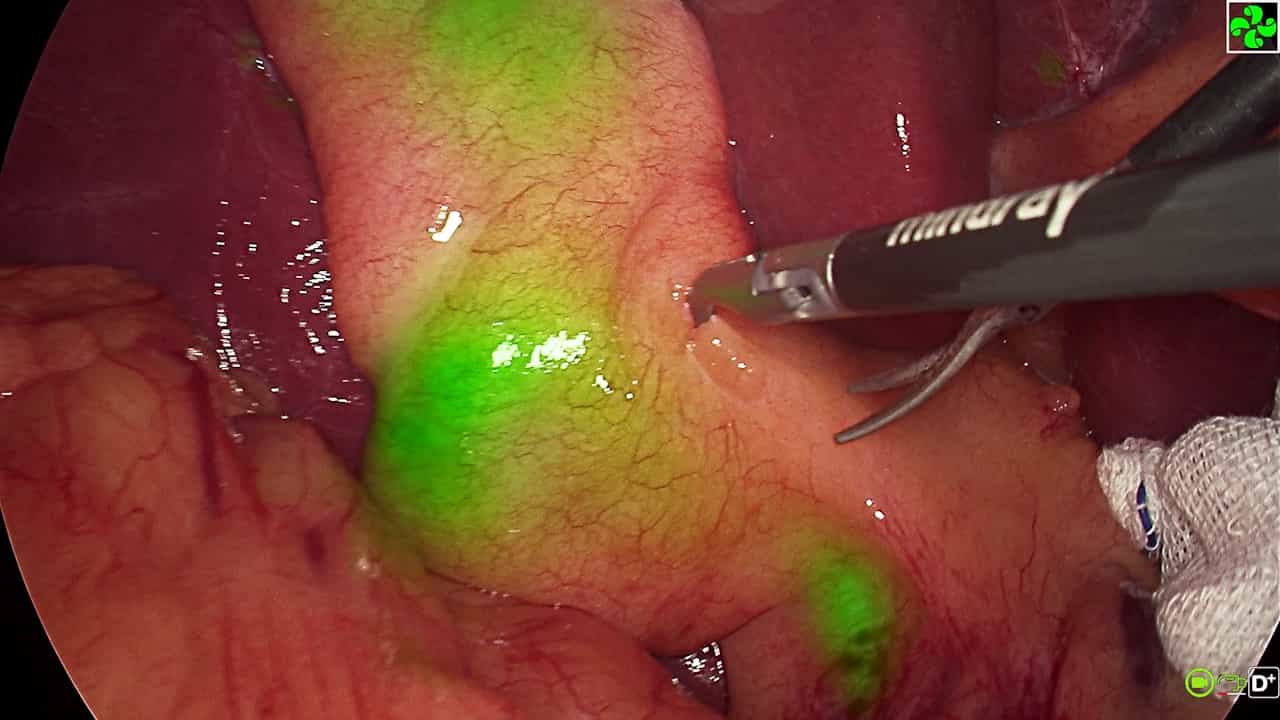

Laparoscopic Cholecystectomy with Indocyanine Green Fluorescence: Choledochoscopic Stone Extraction and Primary Duct Suture
Published on: November 25, 2025
Early cholecystectomy for non-severe acute gallstone pancreatitis: easier said than done
Simone Guadagni1, Ismail Cengeli2, Matteo Palmeri3
1Emergency Surgery Unit, Cisanello Hospital, Pisa, Italy - simone5c@virgilio.it.

Background:
Laparoscopic cholecystectomy (LC) carried out within 3 days after an attack of non-severe acute gallstone pancreatitis (NSAGP) is recommended to reduce hospital stay and overall costs. Aim of the study was to evaluate factors that may delay a timely surgical management of NSAGP and the consequences of this deviation.
Methods:
We reviewed the charts of patients admitted for NSAGP and managed by LC during the last 14 years. A total number of 316 patients entered the study, 98 of whom underwent early LC. A comparison of pre-operative and outcome data from the group of patients undergone early LC and those who received a delayed LC (>3 days since the admission) was made.
Results:
Only 31% of patients presenting with NSAGP were managed by early LC. Respect to these, patients who received a delayed LC were significantly older and had a greater occurrence of clinical signs suggesting common bile duct stones (CBDS). Stabilization of co-morbidities and need to investigate preoperatively the common duct were the main factors associated to the surgical delay. By comparing patients undergone early LC and those who received delayed LC, differences regarding conversion to open surgery (2% vs. 1.3%), need to explore the common bile duct (18.3% vs. 25.6%), CBDS clearance rates (94.4% vs. 94.6%), morbidity (8.1% vs. 8.7%), and postoperative hospital stay (3.9 vs. 3.2 days) were however statistically not significant.
Conclusions:
Several reasons could delay the 3-day recommendation for surgery in NSAGP. These include the need to achieve before surgery the control of age-related co morbidities, and the workup to investigate for common duct stones. A fast track program aiming to early surgery would be advisable for patients presenting with NSAGP. Compared to delayed LC, early LC appears to shorten overall hospitalization but it does not seem to have any clinical impact on the course.
Related Concept Videos
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:24
Chronic Pancreatitis I: Introduction
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...
 01:26
Endoscopic Procedures V: ERCP
Patient...
 01:27
Acute Pancreatitis I: Introduction
Acute pancreatitis is characterized by rapid inflammation of the pancreas, often caused by factors like gallstone blockage or excessive alcohol consumption. Chronic pancreatitis, on the other hand, is a slow, progressive inflammation that may result from long-term alcohol abuse, obstructions in the pancreatic duct, or genetic factors.
The causes of acute pancreatitis include: