Related Experiment Video
Updated: Mar 10, 2026
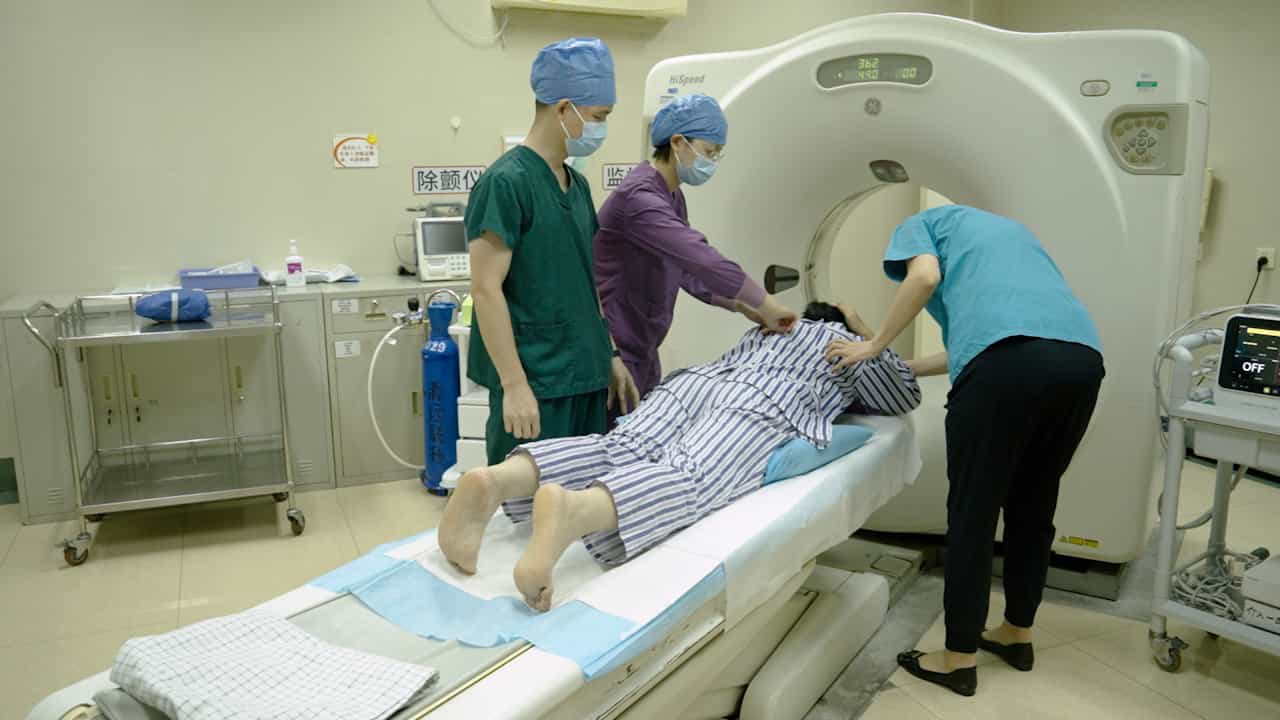

Improved Home Blood Pressure Control by CT-guided Ozone-mediated Renal Denervation for Patients with Resistant Hypertension
Published on: June 6, 2025
Blood Pressure Treatment Adherence and Control after Participation in the ReHOT
Nathália Silva de Jesus1, Armando da Rocha Nogueira2, Cacilda Oliveira Pachu2
1Programa de Pós-Graduação em Cardiologia, Universidade Federal do Rio de Janeiro, RJ - Brazil.

Insights
Treatment adherence and blood pressure control decreased in patients after 6 months in the Resistant Hypertension Optimal Treatment (ReHOT) trial. Lower adherence was linked to education level, while resistant hypertension impacted BP control.
Area of Science:
- Cardiology
- Clinical Trials
- Hypertension Management
Background:
- Pharmacological treatment adherence is crucial for controlling hypertension.
- Low adherence rates contribute significantly to poor blood pressure (BP) control.
Purpose of the Study:
- To assess treatment adherence and its associated factors.
- To evaluate blood pressure (BP) control in participants of the Resistant Hypertension Optimal Treatment (ReHOT) trial.
Main Methods:
- A cross-sectional study of 109 patients completing at least 6 months of the ReHOT trial.
- BP control assessed via ambulatory BP monitoring (ABPM).
- Treatment adherence evaluated using the Morisky Medication Adherence Scale (MMAS).
Main Results:
- BP control decreased from 80% during the trial to 52.1% at reevaluation.
- Treatment adherence, measured by MMAS, dropped to 31.3%.
- Resistant hypertension and medication count were significantly associated with poorer BP control.
Conclusions:
- A notable decrease in BP control and adherence was observed after 6 months in the ReHOT trial.
- Education level showed a trend towards influencing adherence.
- Resistant hypertension was linked to a lack of both BP control and adherence.
Background::
Lack of adherence to pharmacological treatment is one of the main causes of low control rates in hypertension.
Objective::
To verify treatment adherence and associated factors, as well as blood pressure (BP) control in participants of the Resistant Hypertension Optimal Treatment (ReHOT) clinical trial.
Method::
Cross-sectional study including all 109 patients who had completed the ReHOT for at least 6 months. We excluded those participants who failed to respond to the new recruitment after three phone contact attempts. We evaluated the BP control by ambulatory BP monitoring (ABPM; controlled levels: 24-hour systolic and diastolic BP < 130 x 80 mmHg) and analyzed the patients' treatment adherence using the Morisky Medication Adherence Scale (MMAS) questionnaire validated by Bloch, Melo, and Nogueira (2008). The statistical analysis was performed with the software IBM SPSS statistics 21.0. We tested the normality of the data distribution with kurtosis and skewness. The variables tested in the study are presented with descriptive statistics. Comparisons between treatment adherence and other variables were performed with Student's t test for independent variables and Pearson's chi-square or Fisher's exact test. To conduct analyses among patients considering adherence to treatment and BP control, we created four groups: G0, G1, G2, and G3. We considered a 5% significance level in all tests.
Results::
During the ReHOT, 80% of the patients had good BP control and treatment adherence. Of 96 patients reevaluated in the present study, only 52.1% had controlled hypertension when assessed by ABPM, while 31.3% were considered adherent by the MMAS. Regarding other ABPM measures, we observed an absence of a nocturnal dip in 64.6% of the patients and a white-coat effect and false BP control in 23% and 12.5%, respectively. Patients' education level showed a trend towards being a determinant factor associated with lack of adherence (p = 0.05). Resistant hypertension and number of medications were significantly associated with BP control assessed by ABPM (p = 0.009 and p = 0.001, respectively). Resistant hypertension was also significantly associated with group G0 (patients with no control or adherence, p = 0.012).
Conclusion::
There was a decrease in BP control and adherence measured by the MMAS after participation of at least 6 months in the ReHOT clinical trial.
Fundamento::
A falta de adesão ao tratamento medicamentoso da hipertensão arterial sistêmica (HAS) é uma das principais causas das baixas taxas de controle da doença.
Objetivo::
Verificar a adesão e fatores relacionados a ela, além do controle pressórico de pacientes que participaram do ensaio clínico Resistant Hypertension Optimal Treatment (ReHOT).
MéTodo::
Estudo transversal que incluiu todos os 109 pacientes que concluíram o ReHOT há pelo menos 6 meses. Foram excluídos aqueles que não responderam ao novo recrutamento após três tentativas de contato telefônico. Foi realizada avaliação do controle pressórico através de monitorização ambulatorial da pressão arterial (MAPA; PA controlada: pressão arterial [PA] sistólica e diastólica de 24 horas < 130 x 80 mmHg) e avaliação da adesão através de respostas ao questionário Morisky Medication Adherence Scale (MMAS) validado por Bloch, Melo e Nogueira (2008). A análise estatística foi realizada com o programa IBM SPSS statistics 21.0. Para verificar a normalidade da distribuição dos dados, utilizamos testes de curtose e assimetria. As variáveis relacionadas ao objeto de estudo são apresentadas por meio de estatística descritiva. Comparações entre a adesão ao tratamento e demais variáveis foi realizada com o teste t de Student para variáveis independentes e teste do qui-quadrado de Pearson ou exato de Fisher. Para a análise entre pacientes considerando a adesão ao tratamento e controle da PA, foram criados quatro grupos: G0, G1, G2 e G3. Em todos os testes estatísticos consideramos um nível de significância de 5%.
Resultados::
Durante o ReHOT, 80% dos pacientes apresentaram controle pressórico e adesão ao tratamento. Do total de 96 pacientes reavaliados, apenas 52,1% foram identificados como tendo HAS controlada através da avaliação da MAPA e 31,3% apresentaram adesão pelo MMAS. Quando consideradas outras medidas da MAPA, verificou-se que 64,6% dos pacientes não apresentavam descenso noturno e 23% e 12,5% apresentavam efeito do avental branco e falso controle da PA, respectivamente. A escolaridade apresentou tendência a ser um fator determinante de falta de adesão (p = 0,05). O número de medicamentos e a HAS resistente (HAR) tiveram uma relação significativa com o controle da PA medida por MAPA (p = 0,009 e p = 0,001, respectivamente). A HAR teve relação significativa com o grupo G0 (sem controle e sem adesão, p = 0,012).
ConclusãO::
Houve redução do controle da PA e da adesão pelo MMAS após pelo menos 6 meses de participação no ensaio clínico ReHOT.

Related Concept Videos
 01:25
Errors occurring during blood pressure monitoring
Several factors...
 01:28
Special considerations while measuring blood pressure
Monitoring Both Arms:
Monitoring BP in both arms during the initial assessment is advisable, as the systolic value may differ by five to ten mm Hg between arms. For subsequent BP assessments, use the arm with the higher reading.
 01:10
Pre-Procedural Guidelines for Assessing Blood Pressure
 01:23
Hypertension V: Nursing Management
 01:23
Assessment of blood pressure in brachial artery(two-step method)
 01:18
Hypertension and Regulation of Blood Pressure