Related Experiment Video
Updated: Mar 10, 2026


Author Spotlight: Advancements in Retroperitoneal Approach for Necrotizing Pancreatitis
Published on: March 15, 2024
Surgical Management of Complicated Necrotizing Pneumonia in Children
Jin-Yao Lai1, Wendy Yang1, Yung-Ching Ming1
1Division of Pediatric Surgery, Department of Surgery, Chang Gung Memorial Hospital, Chang Gung University, College of Medicine, Linkou, Taiwan.

Background:
There are no well-established indications for the surgical management of acute necrotizing pneumonitis in children. This study presents our experience regarding this challenging topic.
Methods:
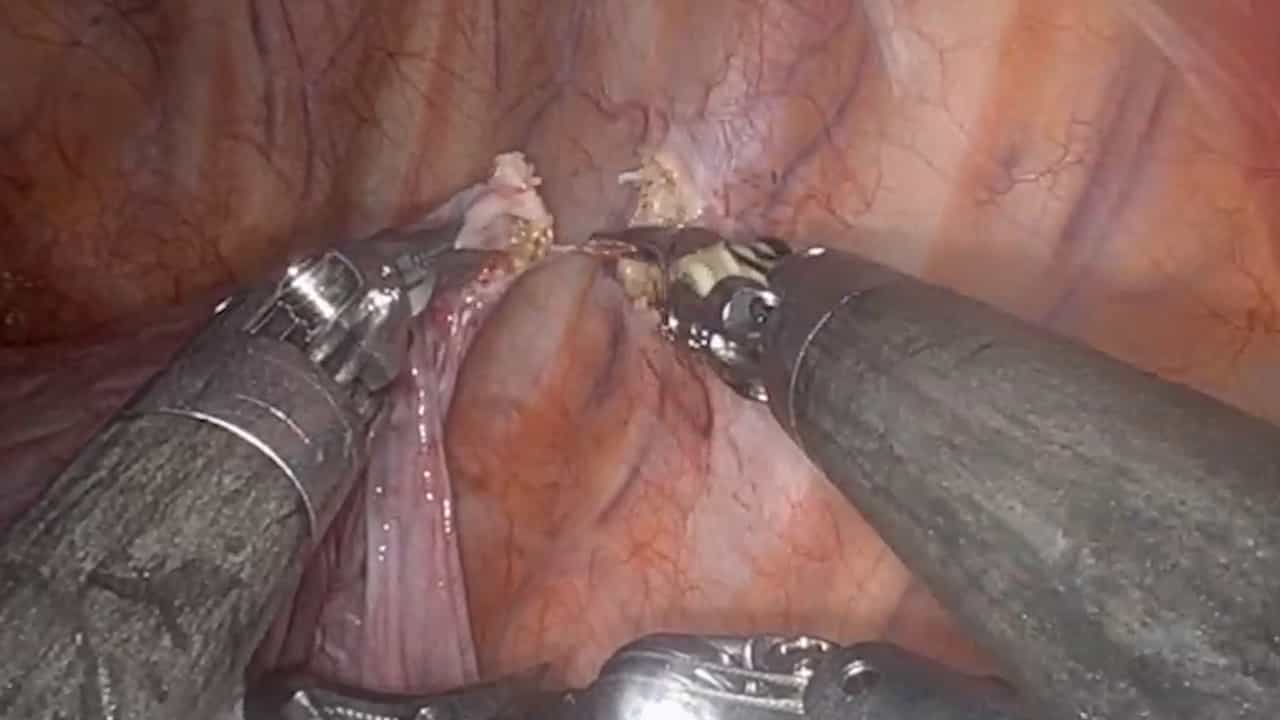
Between 2002 and 2009, 56 necrotizing pneumonitis patients with empyema were treated surgically. The outcomes were analyzed retrospectively. Computed tomography findings of massive lung necrosis or large cavities involving more than 50% of the involved lobe were deemed to be complicated necrotizing pneumonitis. Patients without the above indications were considered uncomplicated.
Results:
Thirty-one cases were uncomplicated and 25 were complicated. Operative procedures included 38 decortications (31 uncomplicated and seven complicated), 14 wedge resections, and four lobectomies (complicated only). Preoperatively, patients with complicated necrotizing pneumonia had a higher incidence of pneumothorax (32% vs. 14.3%; p = 0.001), endotracheal intubation (44% vs. 9.7%; p = 0.008), and hemolytic uremic syndrome (20% vs. 3.2%; p = 0.01). These patients also had higher incidences of intraoperative transfusion (68% vs. 9.7%; p = 0.03), major postoperative complications (16% vs. 0%; p = 0.02), reoperations (16% vs. 0%; p = 0.02), and longer postoperative stay (19.8 ± 24.2 days vs. 11.2 ± 5.8 days; p = 0.03). Four complicated patients, who initially had decortications and limited resections, underwent reoperations. Compared with uncomplicated patients, those who underwent decortications and wedge resection required longer postoperative stays (23.6 ± 9.9 days, p < 0.01 and 21.1 ± 30.7 days, p = 0.04, respectively), whereas patients who had lobectomy had a similar duration of recovery (9.0 ± 2.1 days, p = 0.23). All patients improved significantly at follow-up.
Conclusion:
Children with complicated necrotizing pneumonitis have more preoperative morbidities, more major postoperative complications, and require longer postoperative stays. Aggressive surgical treatment results in significant clinical improvement. Lobectomy in patients with complicated necrotizing pneumonitis may shorten the postoperative course and avoid subsequent surgery.
Related Concept Videos
 01:30
Pneumonia V: Nursing management and Prevention
The nurse must practice strict medical asepsis and adhere to infection control guidelines to minimize healthcare-associated infections.
Enhance airway patency
Position the patient correctly to facilitate drainage of the affected lung segments. Manual or mechanical percussion and vibration can also be employed....
 01:28
Pneumonia IV: Management
Bacterial Pneumonia Treatment
For bacterial pneumonia, antibiotics serve as the cornerstone of therapy. Initial treatment often begins with empirical antibiotics, tailored to the anticipated causative organism and adjusted based on culture results. Key antibiotic choices include:
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:30
Pneumonia III: Complications and Assessment
 01:28
Acute Pyelonephritis II: Diagnostic Studies and Management
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...