An Unexpected Fever Post Serogroup B Meningococcal Sepsis
Related Experiment Video
Updated: Mar 9, 2026

Inducing Meningococcal Meningitis Serogroup C in Mice via Intracisternal Delivery
Published on: November 5, 2019
Daniele Donà1, Elisa Gnoato2, Carlo Giaquinto1
1Pediatric Infectious Diseases Division, University of Padua , Italy.

Abstract:
This case report describes an invasive meningococcal group B infection followed by the development of Kawasaki disease (KD) complicated by macrophage activation syndrome (MAS) in a 2-year-old child. The presented case indicates the possible etiologic relationship between meningococcal sepsis and KD as support of bacterial toxin induced theory. It's important to maintain a high grade of suspicious for KD in every relapse of fever also during convalescence phase of severe infection. Usually, initial treatment with intravenous immunoglobulin is sufficient to control the disease; but, in case of refractory KD complicated by MAS, corticosteroid therapy represents a good option inducing prompt fever resolution and clinical improvement.
Insights
A 2-year-old experienced invasive meningococcal group B infection, leading to Kawasaki disease (KD) and macrophage activation syndrome (MAS). This case suggests a bacterial toxin link between meningococcal sepsis and KD, highlighting the need for vigilance in fever relapses.
Area of Science:
- Pediatrics
- Infectious Diseases
- Rheumatology
Background:
- Invasive meningococcal group B infection can have severe sequelae.
- Kawasaki disease (KD) is an acute febrile vasculitis primarily affecting young children.
- Macrophage activation syndrome (MAS) is a severe, life-threatening hyperinflammation.
Observation:
- A 2-year-old child presented with invasive meningococcal group B infection.
- The child subsequently developed Kawasaki disease (KD) complicated by macrophage activation syndrome (MAS).
- This sequence suggests a potential link between meningococcal sepsis and KD etiology.
Findings:
- The case supports the bacterial toxin-induced theory for Kawasaki disease.
- Persistent or relapsing fever during or after severe infections warrants suspicion for KD.
- Intravenous immunoglobulin is the standard initial treatment for KD.
Implications:
- Refractory KD complicated by MAS may benefit from corticosteroid therapy.
- Corticosteroids demonstrated prompt fever resolution and clinical improvement in this case.
- Clinicians should consider KD in children with recurrent fevers post-severe infection, particularly meningococcal sepsis.
Related Concept Videos
 01:25
Increased Body Temperature
 01:25
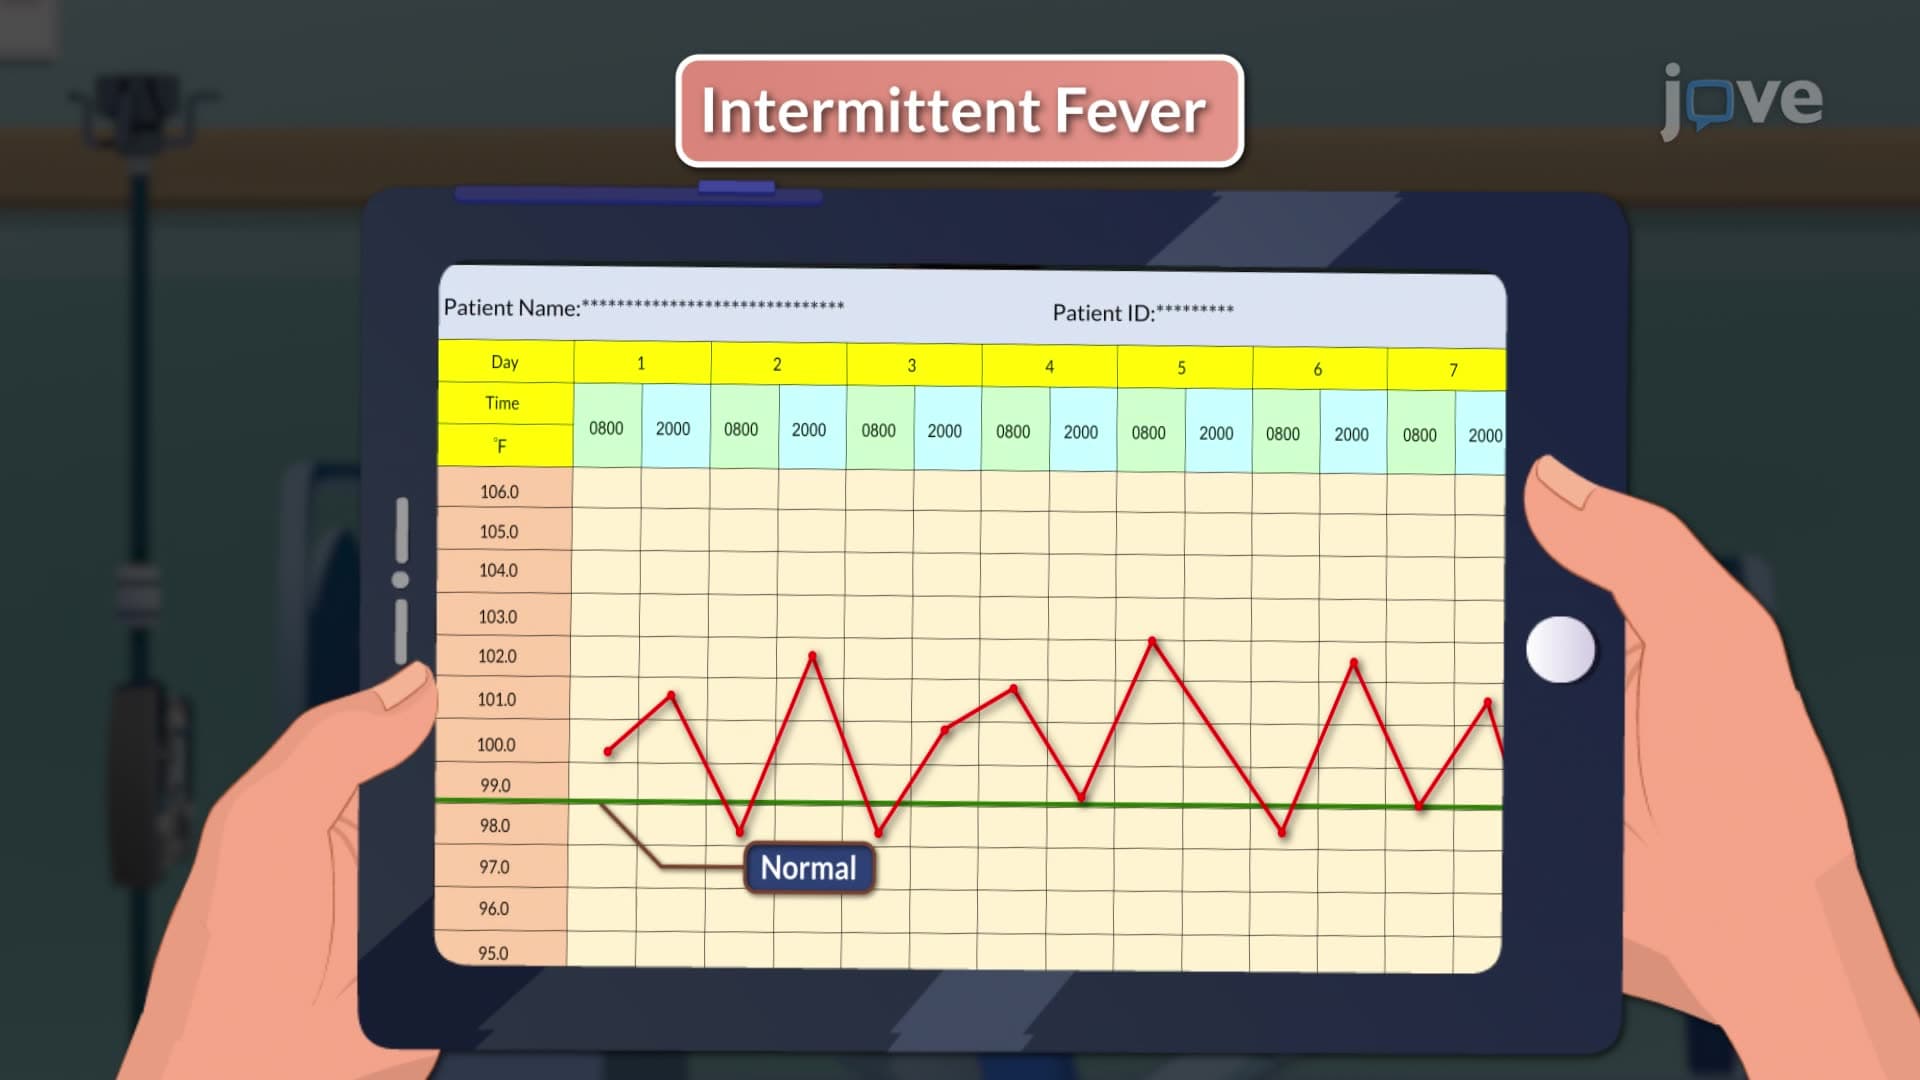
Types of Fever
Here are the different types of fever:
 01:26
Patterns of Fever
 01:28
Acute Pyelonephritis II: Diagnostic Studies and Management
 01:27
Acute Pyelonephritis I: Introduction
 01:29
Endocarditis IV: Nursing Management