Related Experiment Video
Updated: Mar 9, 2026
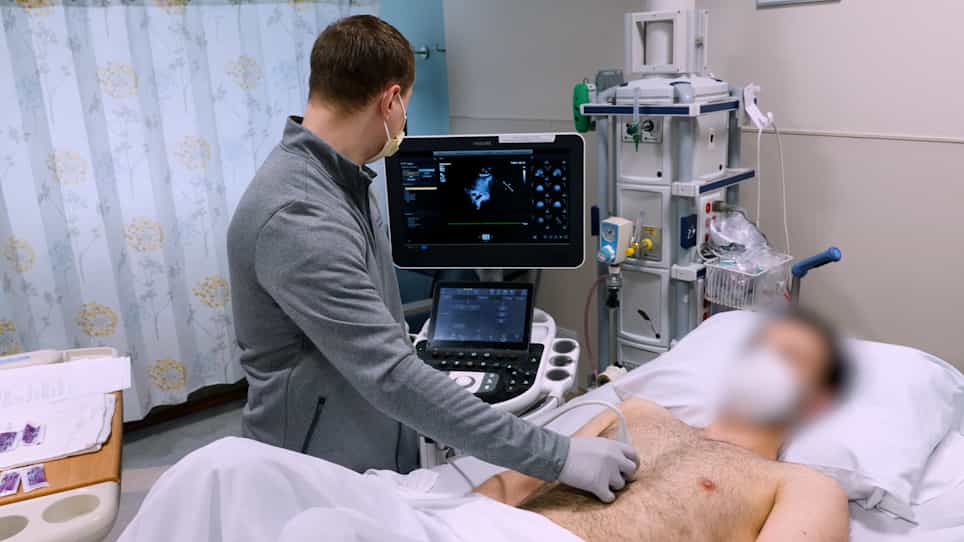

Image Acquisition Method for the Sonographic Assessment of the Inferior Vena Cava
Published on: January 13, 2023
Inferior vena cava filters
1Department of Medicine, The Ottawa Hospital Research Institute, University of Ottawa, Ottawa, ON, Canada.

Use of inferior vena cava (IVC) filters has increased dramatically in recent decades, despite a lack of evidence that their use has impacted venous thromboembolism (VTE)-related mortality. This increased use appears to be primarily driven by the insertion of retrievable filters for prophylactic indications. A growing body of evidence, however, suggests that IVC filters are frequently associated with clinically important adverse events, prompting a closer look at their role. We sought to narratively review the current evidence on the efficacy and safety of IVC filter placements. Inferior vena cava filters remain the only treatment option for patients with an acute (within 2-4 weeks) proximal deep vein thrombosis (DVT) or pulmonary embolism and an absolute contraindication to anticoagulation. In such patients, anticoagulation should be resumed and IVC filters removed as soon as the contraindication has passed. For all other indications, there is insufficient evidence to support the use of IVC filters and high-quality trials are required. In patients where an IVC filter remains, regular follow-up to reassess removal and screen for filter-related complications should occur.
Use of inferior vena cava (IVC) filters has increased dramatically in recent decades, despite a lack of evidence that their use has impacted venous thromboembolism (VTE)-related mortality. This increased use appears to be primarily driven by the insertion of retrievable filters for prophylactic indications. A growing body of evidence, however, suggests that IVC filters are frequently associated with clinically important adverse events, prompting a closer look at their role. We sought to narratively review the current evidence on the efficacy and safety of IVC filter placements. Inferior vena cava filters remain the only treatment option for patients with an acute (within 2-4 weeks) proximal deep vein thrombosis (DVT) or pulmonary embolism and an absolute contraindication to anticoagulation. In such patients, anticoagulation should be resumed and IVC filters removed as soon as the contraindication has passed. For all other indications, there is insufficient evidence to support the use of IVC filters and high-quality trials are required. In patients where an IVC filter remains, regular follow-up to reassess removal and screen for filter-related complications should occur.
More Related Videos
Related Concept Videos
 01:29
Venous Thrombosis III: Interprofessional Care
 01:18
Veins of the Abdomen and Pelvis
The inferior vena cava is fed by numerous smaller veins. The lumbar veins, for instance, drain the posterior abdominal wall, emptying both directly into the inferior vena cava and into the...
 01:25
Hemodialysis I: Introduction
 01:11
Overview of Systemic Veins
The coronary sinus, the heart's principal vein, resides in the coronary sulcus on the heart's posterior aspect. This broad venous channel receives nearly all venous blood from the myocardium, the heart muscle. It is fed by three primary veins: the great cardiac vein, the...
 01:11
Overview of Systemic Arteries
Systemic circulation is the part of the cardiovascular system that carries oxygenated blood away from the heart to the body's tissues and returns deoxygenated blood back to the...
 01:26
Extracorporeal Removal of Drugs: Continuous Renal Replacement Therapy