Related Experiment Video
Updated: Feb 6, 2026


Testing Acetylcholine Followed by Adenosine for Invasive Diagnosis of Coronary Vasomotor Disorders
Published on: February 3, 2021
Ticagrelor Compared with Clopidogrel Increased Adenosine and Cyclic Adenosine Monophosphate Plasma Concentration in
Xiaoye Li1, Qibing Wang2, Ying Xue1
1Department of Clinical Pharmacy, Zhongshan Hospital, Fudan University, Shanghai, China.

Insights
Ticagrelor shows a stronger antiplatelet effect than clopidogrel in acute coronary syndrome (ACS) patients. Ticagrelor also increases plasma adenosine and cyclic adenosine monophosphate (cAMP) levels, correlating with its enhanced antiplatelet activity.
Area of Science:
- Cardiology
- Pharmacology
- Biochemistry
Background:
- Ticagrelor offers superior antiplatelet efficacy compared to clopidogrel.
- Ticagrelor's inhibition of adenosine cellular uptake has potential cardiovascular implications.
- Dual antiplatelet therapy (DAPT) is standard for acute coronary syndrome (ACS).
Purpose of the Study:
- To investigate the relationship between adenosine and cyclic adenosine monophosphate (cAMP) plasma concentrations and the antiplatelet effect of ticagrelor versus clopidogrel.
- To compare the impact of ticagrelor and clopidogrel on adenosine and cAMP levels in ACS patients.
Main Methods:
- Prospective, observational, single-centre cohort study of 68 non-ST-segment elevation ACS patients.
- Measurement of platelet aggregation inhibition (IPA), adenosine, adenosine deaminase (ADA), and cAMP plasma concentrations via immunoassay.
- Data collection included demographics, clinical information, and biochemical assays on admission and 48 hours post-angiography.
Main Results:
- Ticagrelor group exhibited significantly higher mean IPA (93.5%) than the clopidogrel group (67.2%; p=0.000).
- Patients on ticagrelor showed significantly increased plasma adenosine (p=0.029) and cAMP (p=0.037) levels compared to clopidogrel.
- A weak positive correlation was observed between IPA and plasma adenosine (r=0.390, p=0.001) and cAMP (r=0.335, p=0.005).
Conclusions:
- Ticagrelor demonstrates a more potent antiplatelet effect than clopidogrel in ACS patients.
- Ticagrelor significantly increases plasma adenosine and cAMP concentrations, which may contribute to its enhanced antiplatelet activity.
- The findings suggest a link between elevated adenosine/cAMP levels and improved platelet inhibition with ticagrelor therapy.
Abstract:
Ticagrelor produces a more potent antiplatelet effect than clopidogrel and inhibits cellular uptake of adenosine, which is associated with several cardiovascular consequences. We aimed to explore the correlation between adenosine and cyclic adenosine monophosphate (cAMP) plasma concentration and antiplatelet effect by clopidogrel or ticagrelor in patients with acute coronary syndrome (ACS) receiving dual antiplatelet therapy (DAPT). We conducted a prospective, observational and single-centre cohort study enrolling 68 patients with non-ST-segment elevation ACS from January 2016 to May 2016. We monitored the inhibition of platelet aggregation (IPA) and assessed adenosine, adenosine deaminase (ADA) and cAMP plasma concentrations by immunoassay on admission and 48 hr after coronary angiography. The demographic and clinical data were collected by reviewing their medical records. The two groups exhibited similar baseline characteristics including adenosine, ADA and cAMP. The mean IPA in patients receiving ticagrelor was significantly higher than that in patients receiving clopidogrel (93.5% versus 67.2%; p = 0.000). Also, we observed that patients treated with ticagrelor had a significantly higher increase in levels of adenosine and cAMP compared with those treated with clopidogrel (1.04 (0.86; 1.41) versus 0.04 (-0.25; 0.26); p = 0.029 and 0.78 (-1.67; 1.81) versus 0.60 (-1.91; 4.60); p = 0.037, respectively). And there was a weak correlation between IPA and adenosine as well as cAMP plasma concentration (r = 0.390, p = 0.001 and r = 0.335, p = 0.005, respectively). Ticagrelor increased adenosine and cAMP plasma concentration compared with clopidogrel in patients with ACS.
More Related Videos
 05:12
Portable Thermographic Screening for Detection of Acute Wallenberg's Syndrome
Published on: September 19, 2019
 18:11
A Research Method For Detecting Transient Myocardial Ischemia In Patients With Suspected Acute Coronary Syndrome Using Continuous ST-segment Analysis
Published on: December 28, 2012
Related Concept Videos
 01:26
Acute Coronary Syndrome V: Nursing Management
 01:28
Acute Coronary Syndrome IV: Interprofessional Care
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations
 01:30
Acute Coronary Syndrome I: Introduction
 01:08
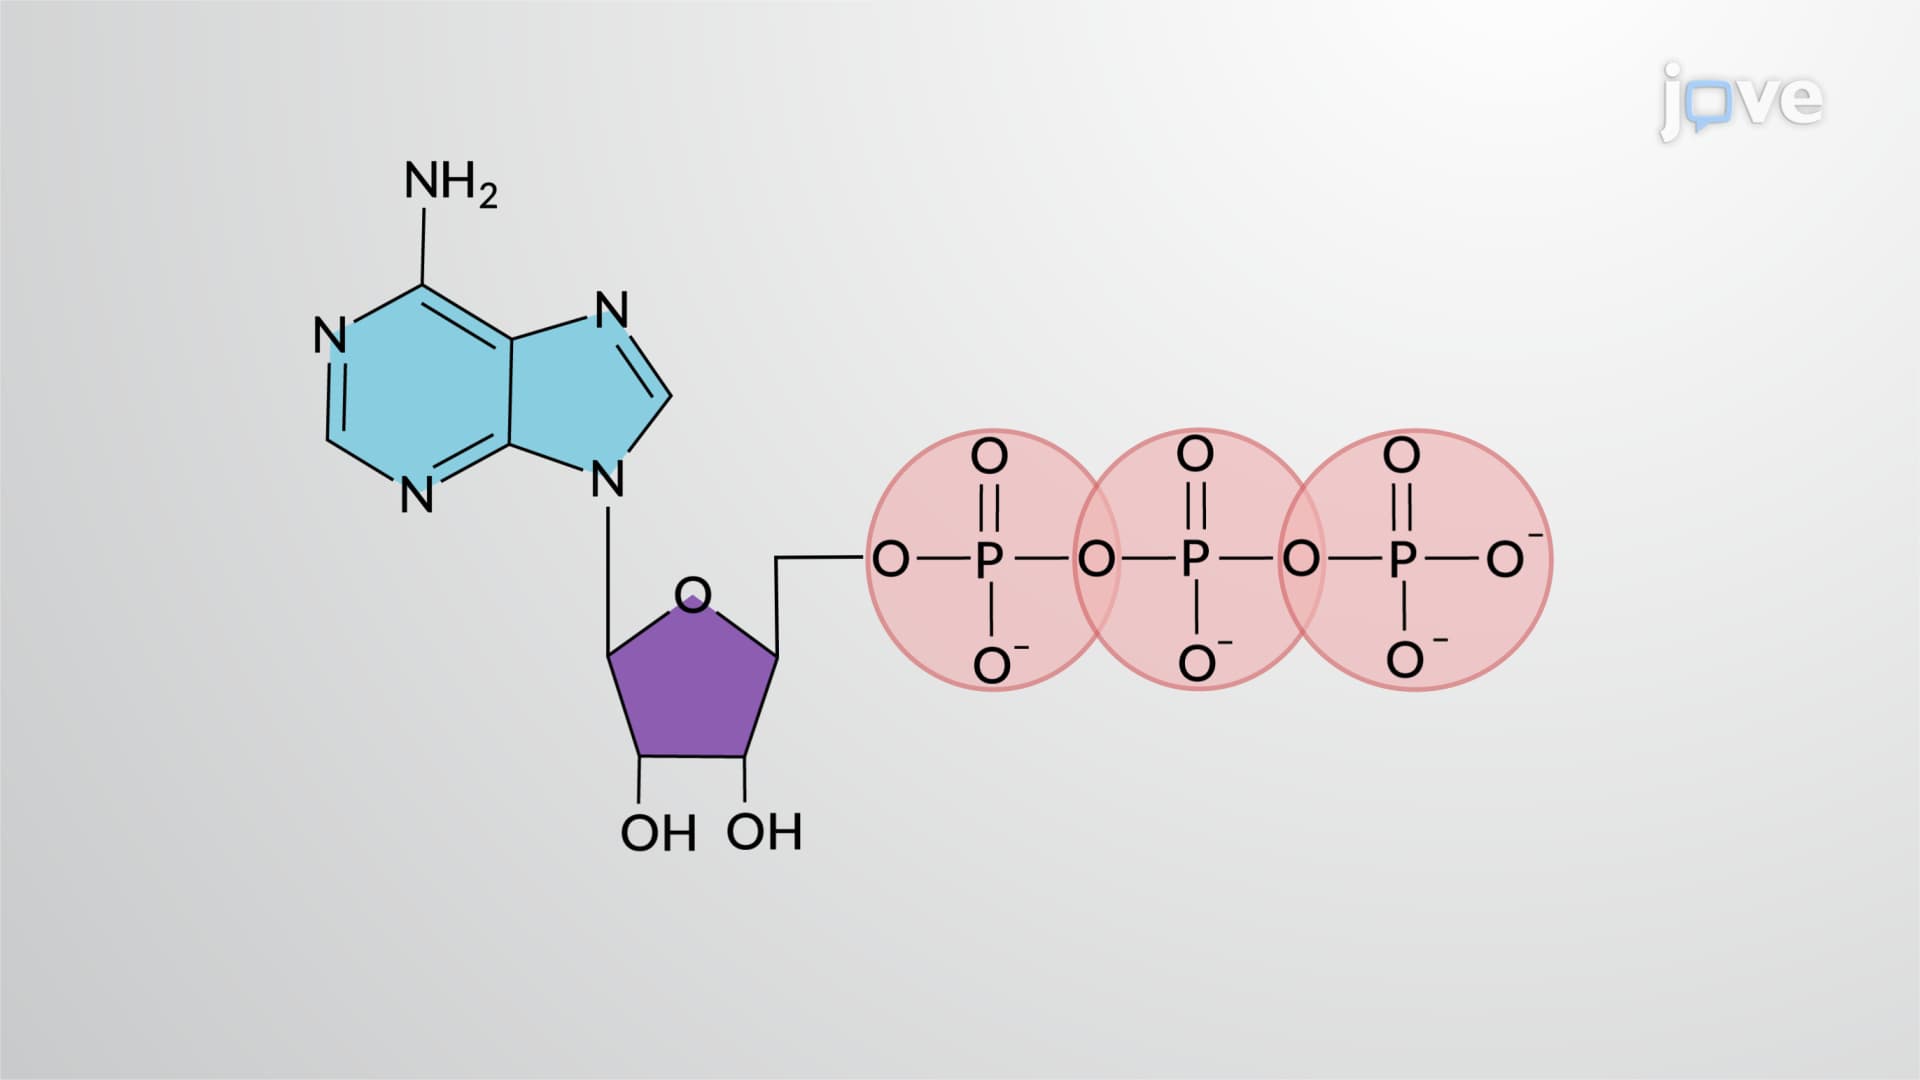
Hydrolysis of ATP
If one phosphate group is removed, a molecule of ADP—adenosine diphosphate—remains, along with inorganic phosphate. ADP can be further hydrolyzed to AMP—adenosine...