

HIV Infects Bronchial Epithelium and Suppresses Components of the Mucociliary Clearance Apparatus
S Chinnapaiyan1, T Parira1, R Dutta1
1Department of Immunology, Institute of Neuroimmune Pharmacology, Herbert Wertheim College of Medicine, Florida International University. Miami, Florida, United States of America.

Abstract:
Recurrent lung infections and pneumonia are emerging as significant comorbidities in the HIV-infected population in the era of combination antiretroviral therapy (cART). HIV infection has been reported to suppress nasal mucociliary clearance (MCC). Since the primary components driving nasal MCC and bronchial MCC are identical, it is possible that bronchial MCC is affected as well. Effective MCC requires optimal ciliary beating which depends on the maintenance of the airway surface liquid (ASL), a function of cystic fibrosis transmembrane conductance regulator (CFTR) activity and the integrity of the signaling mechanism that regulates ciliary beating and fluid secretion. Impairment of either component of the MCC apparatus can compromise its efficacy and promote microbial colonization. We demonstrate that primary bronchial epithelium expresses HIV receptor CD4 and co-receptors CCR5 and CXCR4 and can be infected by both R5 and X4 tropic strains of HIV. We show that HIV Tat suppresses CFTR biogenesis and function in primary bronchial epithelial cells by a pathway involving TGF-β signaling. HIV infection also interferes with bronchial epithelial cell differentiation and suppresses ciliogenesis. These findings suggest that HIV infection suppresses tracheobronchial mucociliary clearance and this may predispose HIV-infected patients to recurrent lung infections, pneumonia and chronic bronchitis.
More Related Videos
 08:42
Isolating Bronchial Epithelial Cells from Resected Lung Tissue for Biobanking and Establishing Well-Differentiated Air-Liquid Interface Cultures
Published on: May 26, 2023
 09:02
Infection of Primary Nasal Epithelial Cells Grown at an Air-Liquid Interface to Characterize Human Coronavirus-Host Interactions
Published on: September 22, 2023
Related Concept Videos
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:23
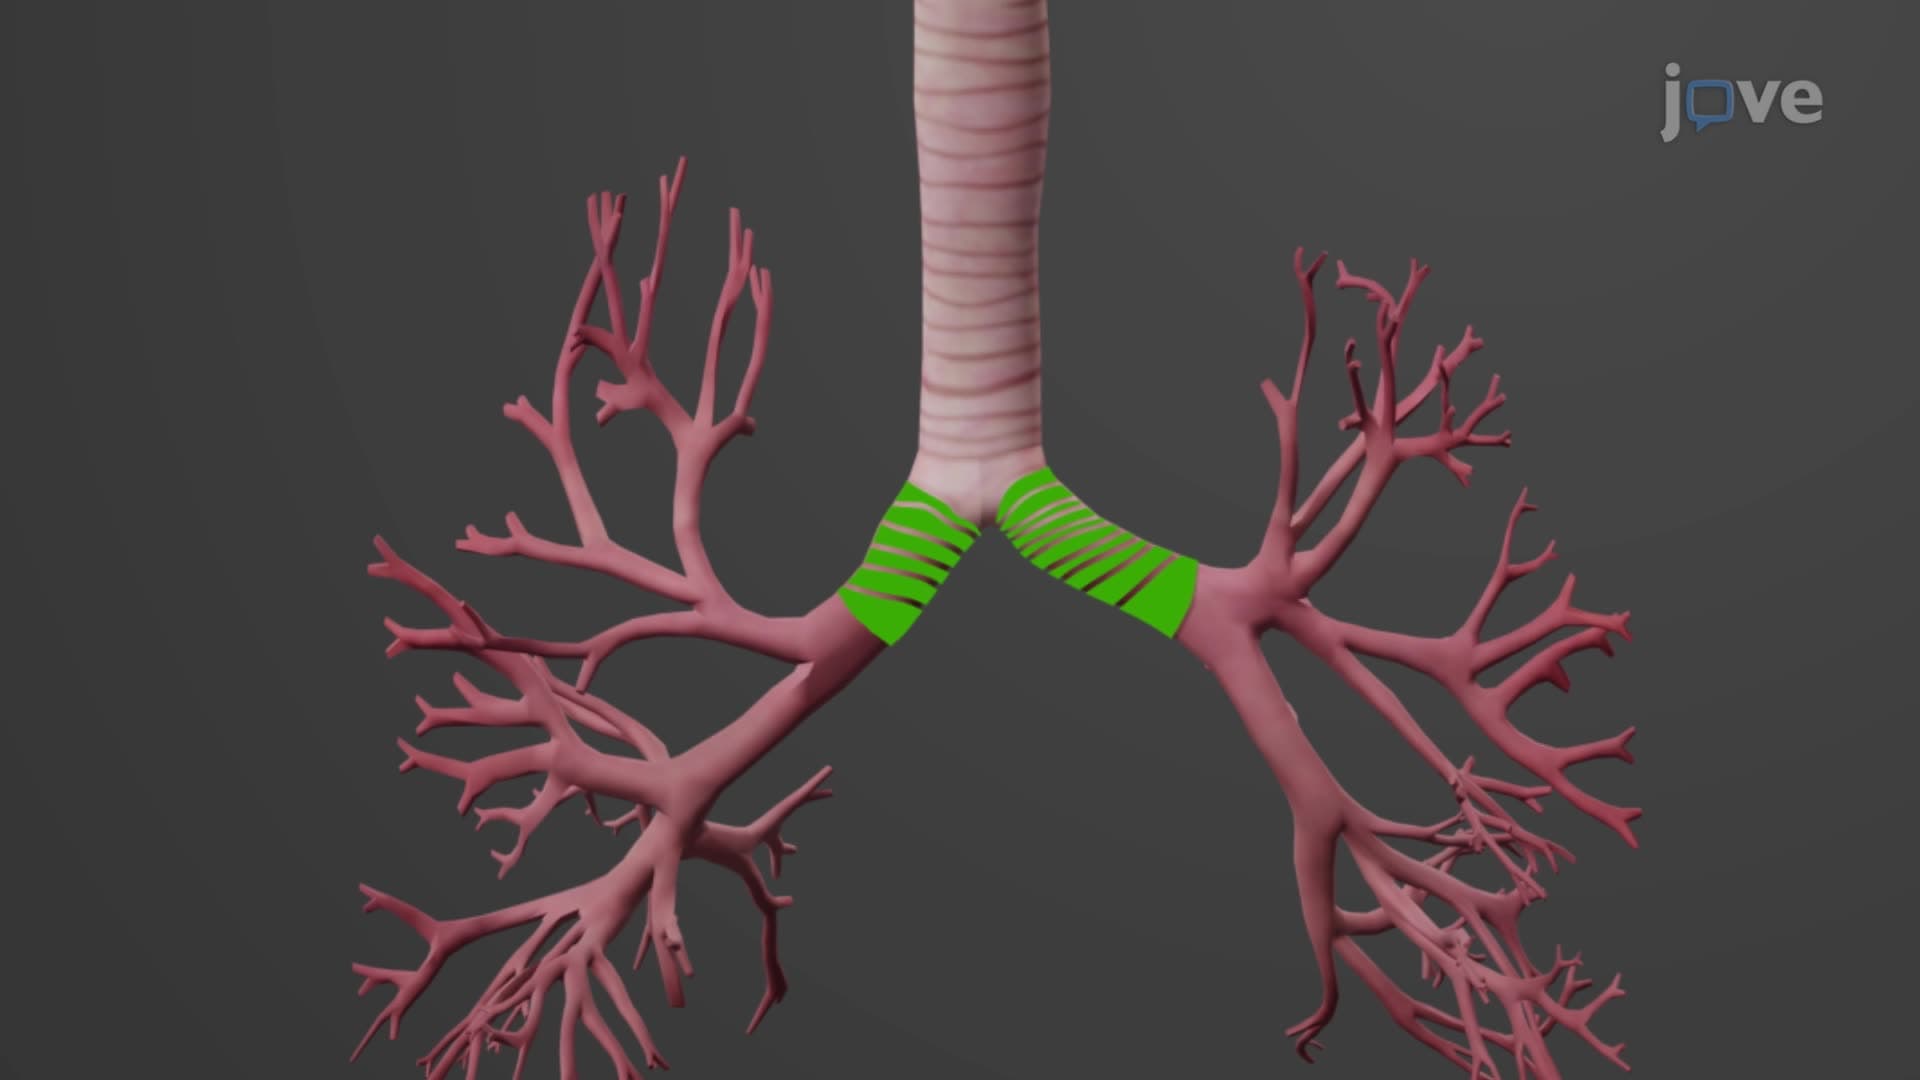
The Bronchial Tree
The trachea, commonly known as the windpipe, is a tube that connects the larynx (voice box) to the bronchi. At a point called the carina, it bifurcates into two primary bronchi. The right primary bronchus is wider, shorter, and more vertical than the left primary...
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...
 01:28
Pulmonary Tuberculosis II
Here is a detailed explanation of its pathophysiology:
Transmission: The process begins when a person inhales droplet nuclei containing M. tuberculosis. These are typically released into the air when an individual with pulmonary or...
 01:23
Cystic Fibrosis: Pathogenesis
CF is primarily caused by a genetic mutation in a chromosome 7 gene coding for the cystic fibrosis transmembrane conductance regulator (CFTR) protein. The most common gene mutation leading to CF is the ΔF508 mutation,...