Related Experiment Video
Updated: Mar 8, 2026
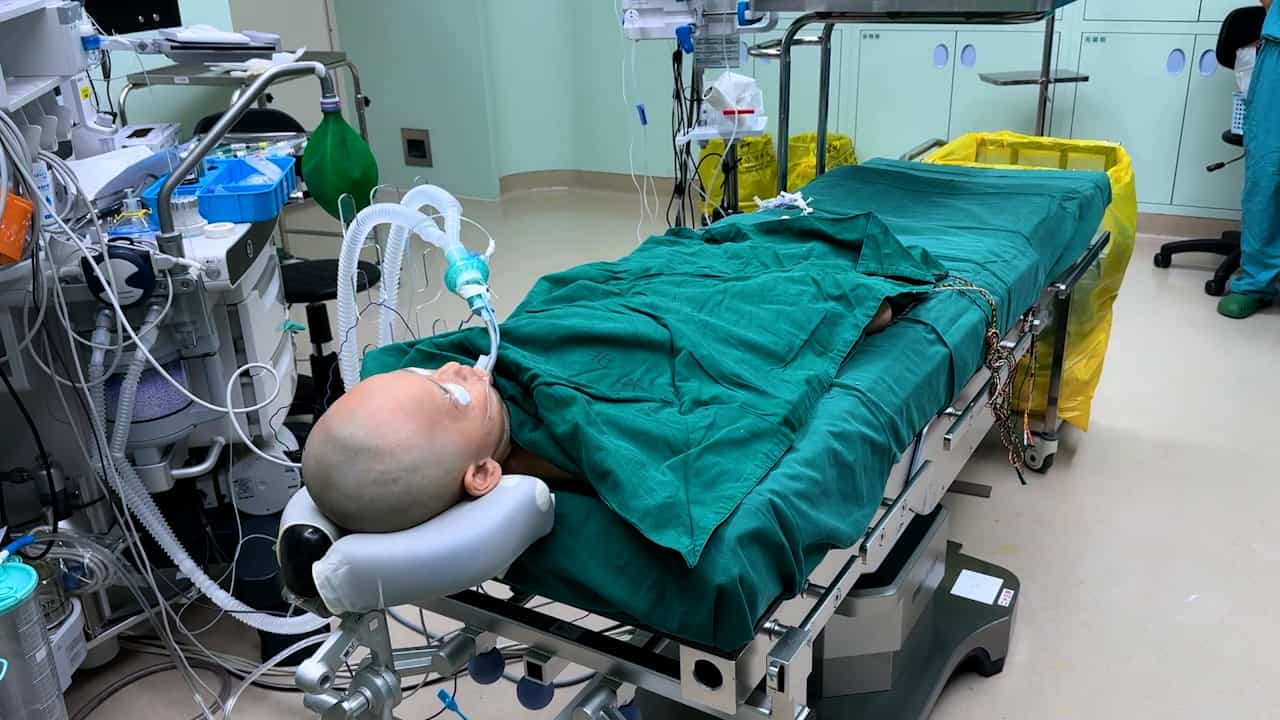

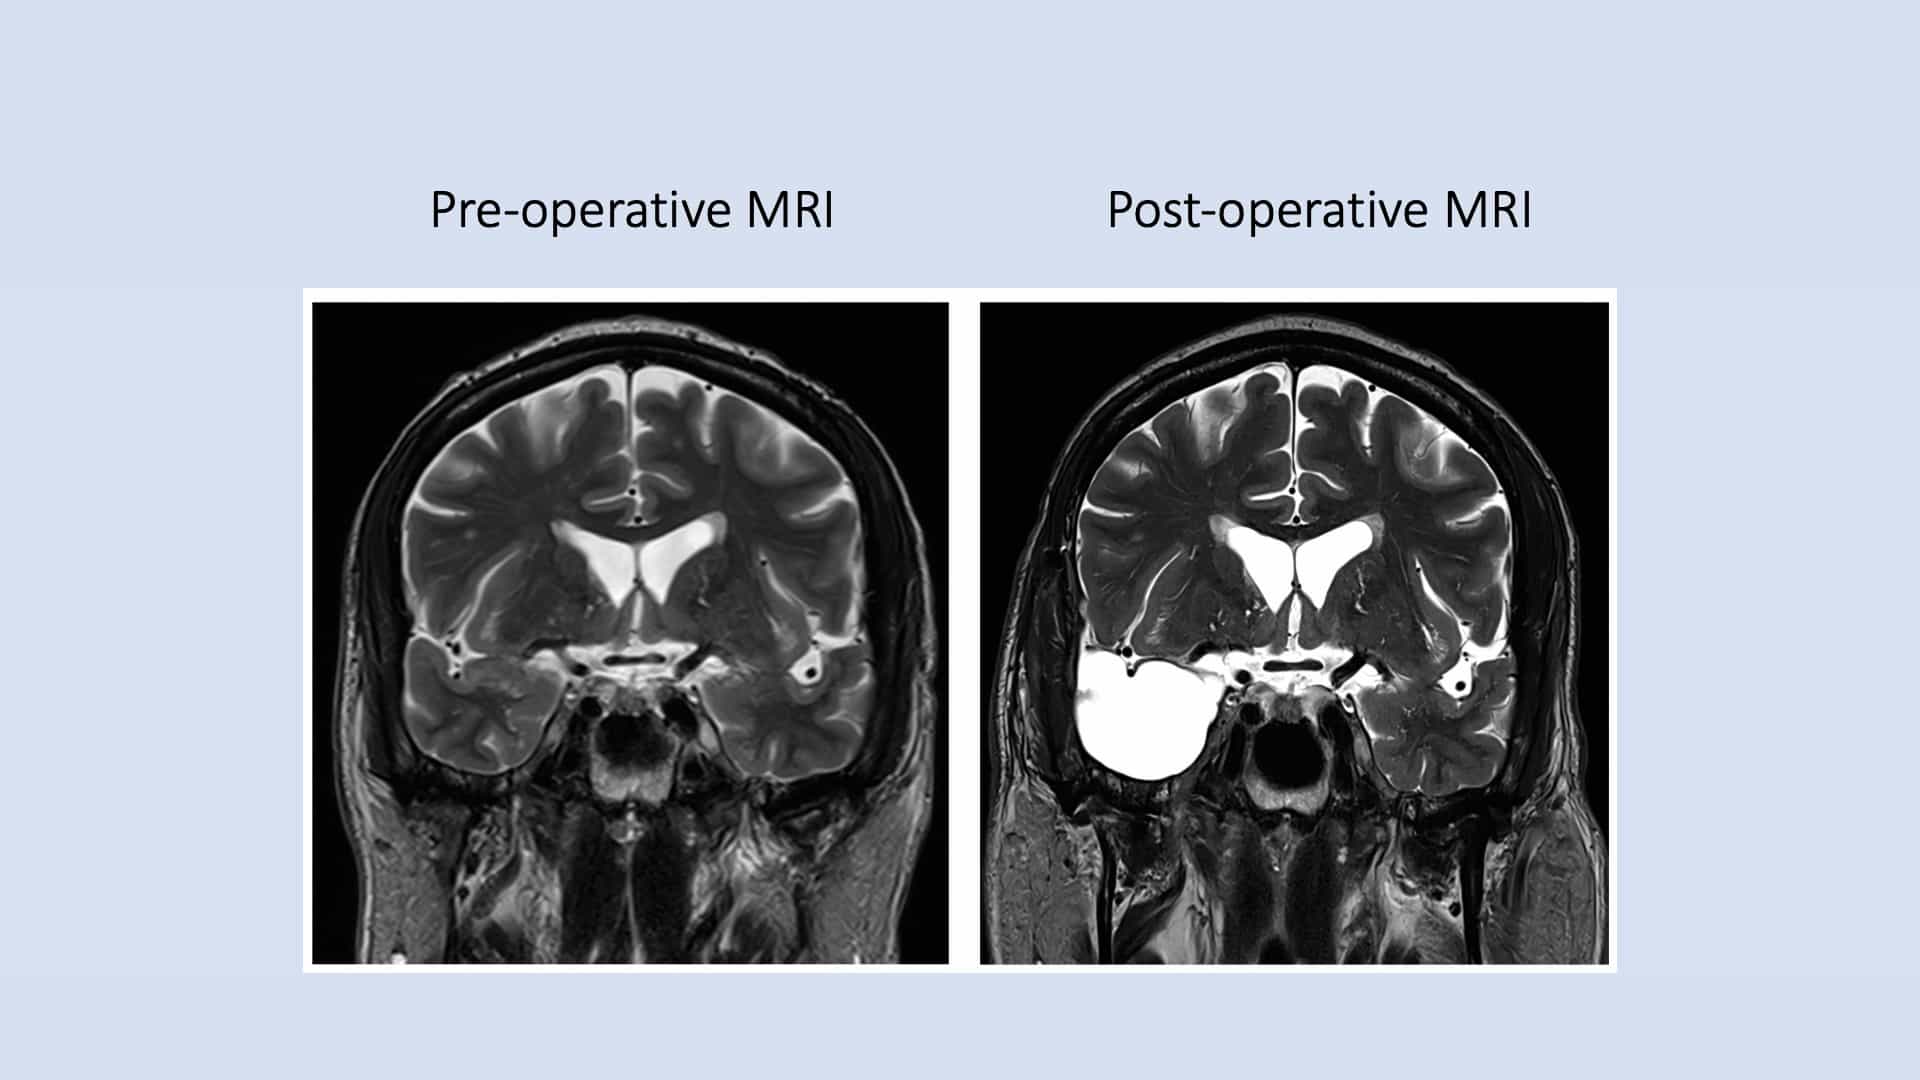
Author Spotlight: Studying Clinical Characters and Epilepsy Outcomes After Frontal Disconnection in Patients with MOGHE
Published on: August 16, 2024
Neuropsychological outcome following frontal lobectomy for pharmacoresistant epilepsy in adults
Robyn M Busch1, Darlene P Floden2, Lisa Ferguson2
1From the Epilepsy Center (R.M.B., L.F., S.J., L.J., W.B., I.M.N.), Psychiatry & Psychology (R.M.B., D.P.F., L.F., A.M.), Center for Neurological Restoration (D.P.F.), and Diagnostic Radiology (S.M., S.J.), Neurological Institute, Cleveland Clinic, OH. buschr@ccf.org.

Objective:
This retrospective cohort study characterized cognitive and motor outcomes in a large sample of adults who underwent frontal lobe resections for treatment of pharmacoresistant epilepsy.
Methods:
Ninety patients who underwent unilateral frontal lobe resection for epilepsy (42 language-dominant hemisphere/48 nondominant hemisphere) between 1989 and 2014 completed comprehensive preoperative and postoperative neuropsychological evaluations that included measures of verbal and nonverbal intellectual functioning, attention/working memory, processing speed, language, executive functioning, verbal and visual memory, and motor functioning. Objective methods were used to assess meaningful change across a wide range of abilities and to identify factors associated with neuropsychological decline following frontal lobectomy. Detailed postoperative neuroimaging analysis was conducted to characterize region, extent, and volume of resection.
Results:
Forty-eight percent of patients did not demonstrate meaningful postoperative declines in cognition and an additional 42% demonstrated decline in 1 or 2 cognitive domains. When cognitive decline was observed, it usually occurred on measures of intelligence, visuomotor processing speed, or executive functioning. Side and site of resection were unrelated to cognitive outcome, but played a role in decline of contralateral manual dexterity following supplementary motor area resection. Higher preoperative ability, older age at surgery, absence of a malformation of cortical development on MRI, and poor seizure outcome were related to cognitive decline on some measures, but had poor sensitivity in identifying at-risk patients.
Conclusions:
The vast majority of patients who undergo frontal lobectomy for treatment of pharmacoresistant epilepsy demonstrate good cognitive and motor outcomes.
More Related Videos
Related Concept Videos
 01:24
Epilepsy and Seizures: Overview
Various factors can trigger epilepsy, including genetic factors, brain damage, metabolic causes, and unknown etiology. Diagnosis of epilepsy involves electroencephalography (EEG), which...
 01:30
Psychosurgery
Historical Development of Psychosurgery
In the 1930s, Portuguese neurologist Antonio Egas Moniz introduced a surgical procedure designed...