Related Experiment Video
Updated: Mar 8, 2026


Author Spotlight: Assessment of Cardiac Output Calculation by Thermodilution in Pigs for Effective Perfusion Flow During EVLP
Published on: June 28, 2024
Cardiac output and systemic vascular resistance: Clinical assessment compared with a noninvasive objective
Asma Razavi1, Christopher J L Newth2, Robinder G Khemani2
1Loma Linda University Medical Center, Loma Linda, CA.

Insights
Physician assessment of cardiac output and systemic vascular resistance in shock patients showed poor agreement with ultrasonic cardiac output monitor (USCOM) data, highlighting variability in clinical decisions.
Area of Science:
- Pediatric Intensive Care Medicine
- Hemodynamic Monitoring
- Critical Care Research
Background:
- Accurate assessment of cardiac output (CO) and systemic vascular resistance (SVR) is crucial for managing patients in shock.
- Physician clinical assessment is commonly used, but its accuracy and consistency can be variable.
- The ultrasonic cardiac output monitor (USCOM) offers an objective method for hemodynamic assessment.
Purpose of the Study:
- To compare physician assessments of CO and SVR with measurements obtained from the USCOM in pediatric shock patients.
- To investigate how the availability of USCOM data might influence physician therapeutic decisions.
Main Methods:
- A prospective, observational study was conducted in a pediatric intensive care unit involving 40 children with shock.
- Physicians clinically assessed CO and SVR, categorizing them as high, normal, or low.
- An investigator simultaneously measured cardiac index (CI) and systemic vascular resistance index (SVRI) using USCOM and categorized these values.
Main Results:
- Overall agreement between physician assessments and USCOM measurements for CI and SVRI was poor (κ = 0.18 and κ = 0.16, respectively).
- Interobserver agreement among physicians for both CI and SVRI was also poor (κ = 0.33 and κ = 0.28, respectively).
- A significant proportion (21%) of theoretical physician interventions were deemed 'unacceptable' based on USCOM measurements.
Conclusions:
- There is a substantial lack of agreement between physician-based hemodynamic assessments and objective USCOM data in pediatric shock.
- Significant interobserver variability exists among physicians in assessing CI and SVRI.
- Objective hemodynamic monitoring with tools like USCOM may be necessary to reduce variability and enhance diagnostic accuracy in shock management.
Purpose:
To evaluate physician assessment of cardiac output and systemic vascular resistance in patients with shock compared with an ultrasonic cardiac output monitor (USCOM). To explore potential changes in therapy decisions if USCOM data were available using physician intervention answers.
Study Design:
Double-blinded, prospective, observational study in a tertiary hospital pediatric intensive care unit. Forty children (<18years) admitted with shock, requiring ongoing volume resuscitation or inotropic support. Two to 3 physicians clinically assessed cardiac output and systemic vascular resistance, categorizing them as high, normal, or low. An investigator simultaneously measured cardiac index (CI) and systemic vascular resistance index (SVRI) with USCOM categorized as high, normal, or low.
Results:
Overall agreement between physician and USCOM for CI (48.5% [κ = 0.18]) and SVRI (45.9% [κ = 0.16]) was poor. Interobserver agreement was also poor for CI (58.7% [κ = 0.33]) and SVRI (52.3% [κ = 0.28]). Comparing theoretical physician interventions to "acceptable" or "unacceptable" clinical interventions, based on USCOM measurement, 56 (21%) physician interventions were found to be "unacceptable."
Conclusions:
There is poor agreement between physician-assessed CI and SVRI and USCOM, with significant interobserver variability among physicians. Objective measurement of CI and SVRI may reduce variability and improve diagnostic accuracy.

Related Concept Videos
 01:11
Cardiac Output and Stroke Volume
In an average resting adult male, the typical cardiac...
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:19
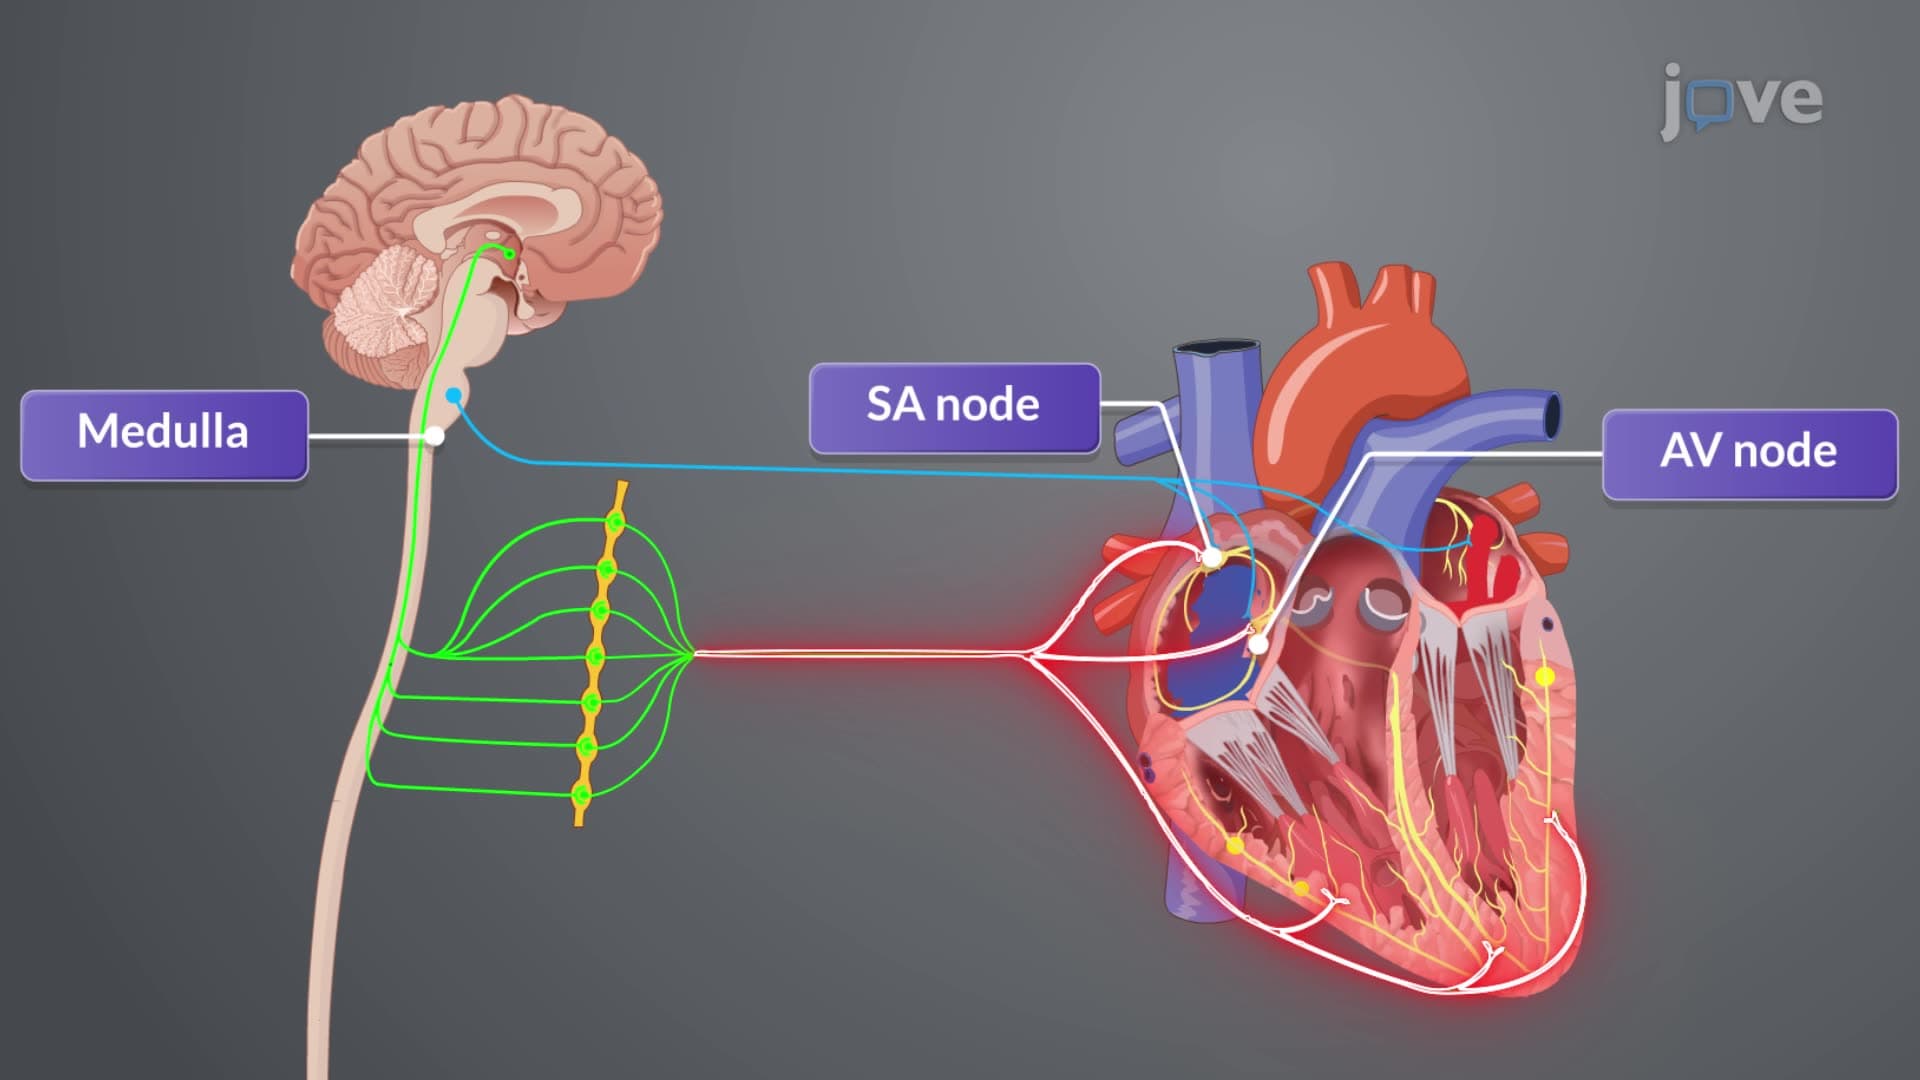
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...
 01:05
Pulse
Pulse Rate and its Significance
Pulse rate, often measured in beats per minute (bpm), reflects the heart rate (HR), which is influenced by numerous factors such as stress, physical activity, and hormonal changes. A normal resting adult pulse rate falls...
 01:20
Vascular Resistance
The primary determinants of vascular resistance are vessel diameter, blood viscosity, and vessel length. Among these, vessel diameter plays the most significant role due to the fourth power relationship described by...
 01:24
Blood Pressure Imbalances and Circulatory Shock
Blood Pressure: Hypertension and Hypotension
Normal blood pressure is 120/80 mm Hg. Elevated blood pressure is 120-129/under 80 mm Hg. Hypertension, warranting treatment at 130/80 mm Hg, is often asymptomatic and can lead to severe cardiovascular events, aneurysms, peripheral arterial disease, chronic renal disease, or cardiac...