Related Experiment Video
Updated: Mar 8, 2026


Monitoring Dynamic Growth of Retinal Vessels in Oxygen-Induced Retinopathy Mouse Model
Published on: April 2, 2021
Adenosine receptors and caffeine in retinopathy of prematurity
Jiang-Fan Chen1, Shuya Zhang1, Rong Zhou2
1Molecular Neuropharmacology Laboratory, School of Optometry and Ophthalmology and Eye Hospital, Wenzhou Medical University, Wenzhou, Zhejiang, China; State Key Laboratory Cultivation Base and Key Laboratory of Vision Science, Ministry of Health of China, Wenzhou, Zhejiang, China.

Insights
Adenosine receptor-based therapies offer a promising alternative for treating retinopathy of prematurity (ROP), potentially avoiding side effects of current anti-VEGF treatments. Caffeine shows therapeutic effects in ROP models.
Area of Science:
- Ophthalmology and Developmental Biology
- Vascular Biology and Angiogenesis
- Pharmacology and Therapeutics
Background:
- Retinopathy of prematurity (ROP) is a leading cause of childhood blindness, stemming from oxygen-induced damage to developing retinal vasculature.
- Current anti-VEGF therapies for ROP have limitations, including adverse effects on eye growth and retinal vascular development in preterm infants.
- Hypoxia triggers increased extracellular adenosine and adenosine receptors, presenting a potential therapeutic target for controlling pathological angiogenesis.
Purpose of the Study:
- To review experimental evidence supporting adenosine receptor-based therapeutic strategies for ROP.
- To examine the role of adenosine receptor subtypes (A1R, A2AR, A2BR) in ROP development and treatment.
- To highlight the therapeutic potential of caffeine as an adenosine receptor antagonist for ROP.
Main Methods:
- Review of experimental evidence on aberrant adenosine signaling in oxygen-induced retinopathy.
- Analysis of studies using oxygen-induced retinopathy models to investigate adenosine receptor subtypes.
- Evaluation of clinical and animal evidence for caffeine's therapeutic effect in ROP.
Main Results:
- Aberrant adenosine signaling is implicated in oxygen-induced retinopathy.
- Adenosine receptor subtypes play distinct roles in ROP development and response to therapy.
- Caffeine demonstrates therapeutic potential in preclinical ROP models.
Conclusions:
- Adenosine receptor-based strategies offer a targeted approach to control pathological angiogenesis in ROP without compromising normal vascular development.
- Caffeine, a non-selective adenosine receptor antagonist, shows promise for ROP treatment.
- Adenosine receptor and caffeine-based therapies hold translational potential for ROP and other proliferative retinopathies.
Abstract:
Retinopathy of prematurity (ROP) is a major cause of childhood blindness in the world and is caused by oxygen-induced damage to the developing retinal vasculature, resulting in hyperoxia-induced vaso-obliteration and subsequent delayed retinal vascularization and hypoxia-induced pathological neovascularization driven by vascular endothelial growth factor (VEGF) signaling pathway in retina. Current anti-VEGF therapy has shown some effective in a clinical trial, but is associated with the unintended effects on delayed eye growth and retinal vasculature development of preterm infants. Notably, cellular responses to hypoxia are characterized by robust increases in extracellular adenosine production and the markedly induced adenosine receptors, which provide a novel target for preferential control of pathological angiogenesis without affecting normal vascular development. Here, we review the experimental evidence in support of adenosine receptor-based therapeutic strategy for ROP, including the aberrant adenosine signaling in oxygen-induced retinopathy and the role of three adenosine receptor subtypes (A1R, A2AR, A2BR) in development and treatment of ROP using oxygen-induced retinopathy models. The clinical and initial animal evidence that implicate the therapeutic effect of caffeine (a non-selective adenosine receptor antagonist) in treatment of ROP are highlighted. Lastly, we discussed the translational potential as well therapeutic advantage of adenosine receptor- and caffeine-based therapy for ROR and possibly other proliferative retinopathy.


Related Concept Videos
 01:26
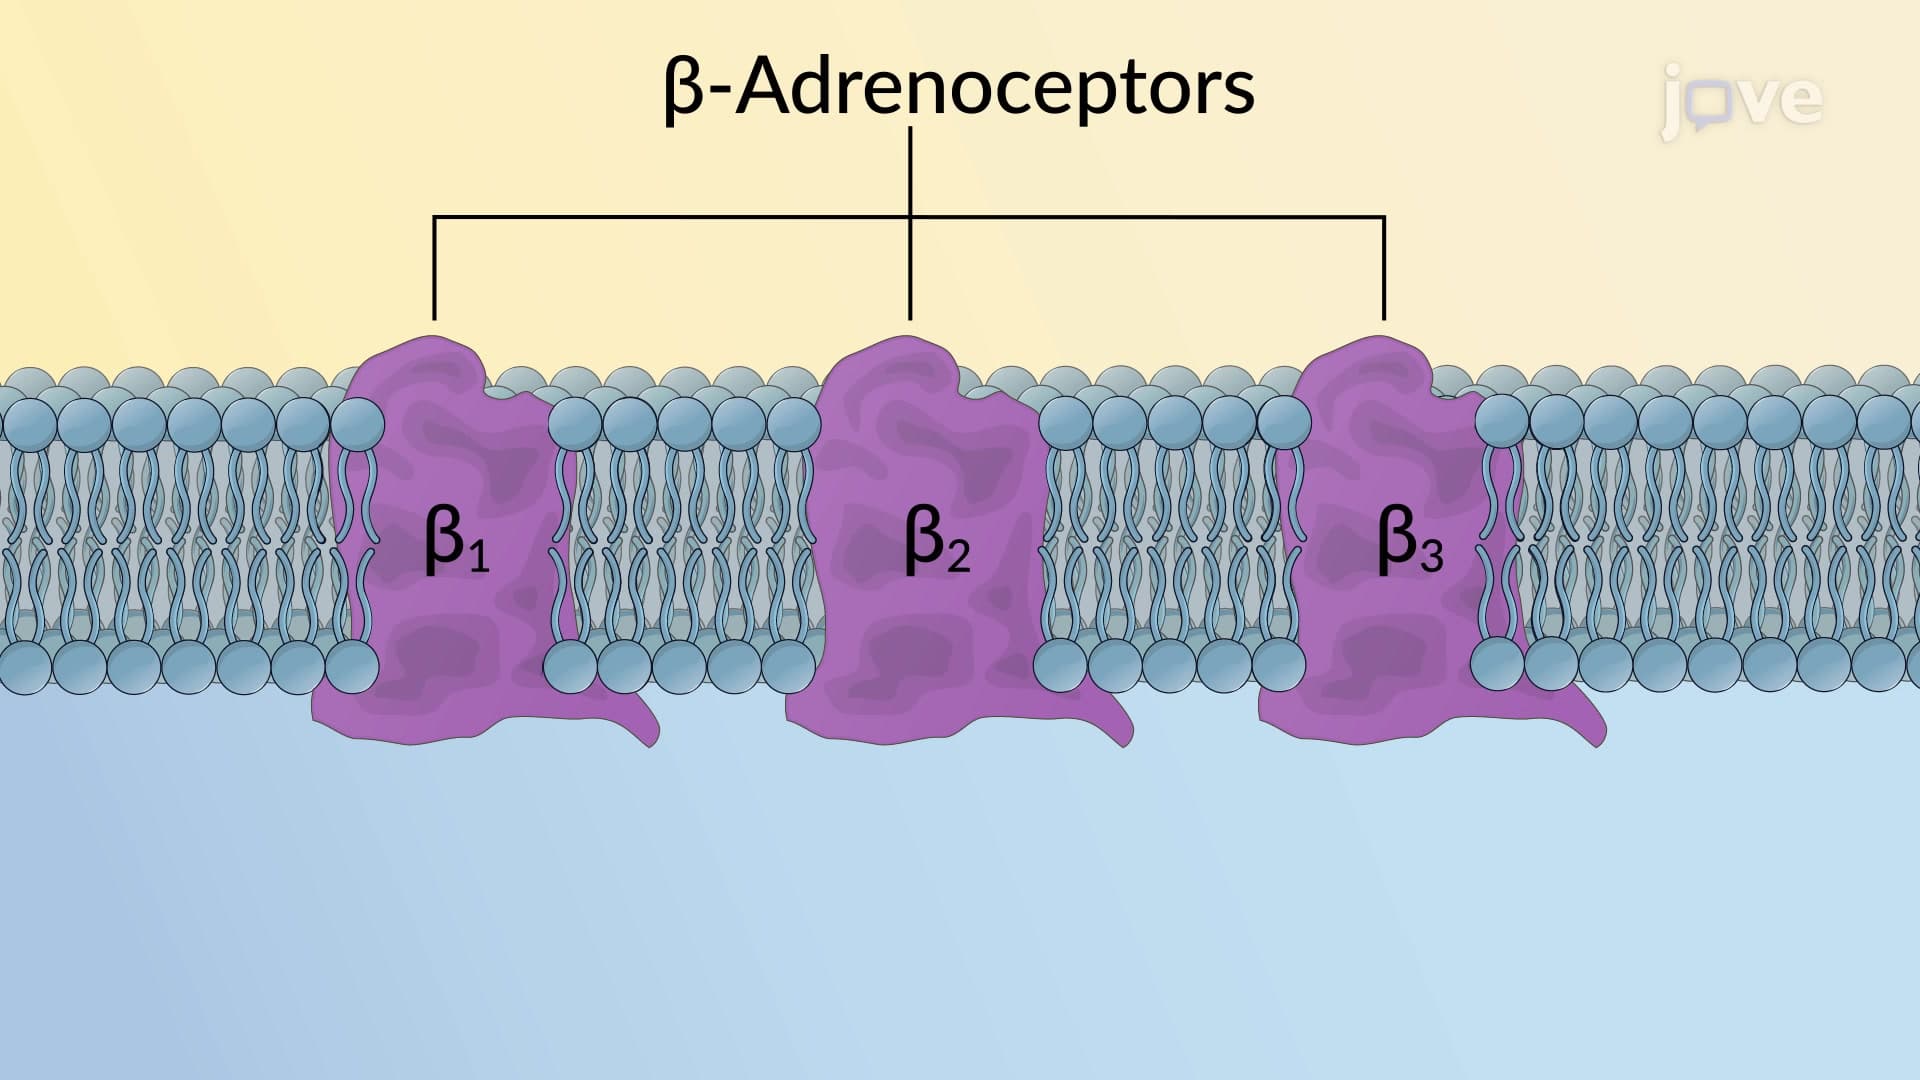
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors...
 01:31
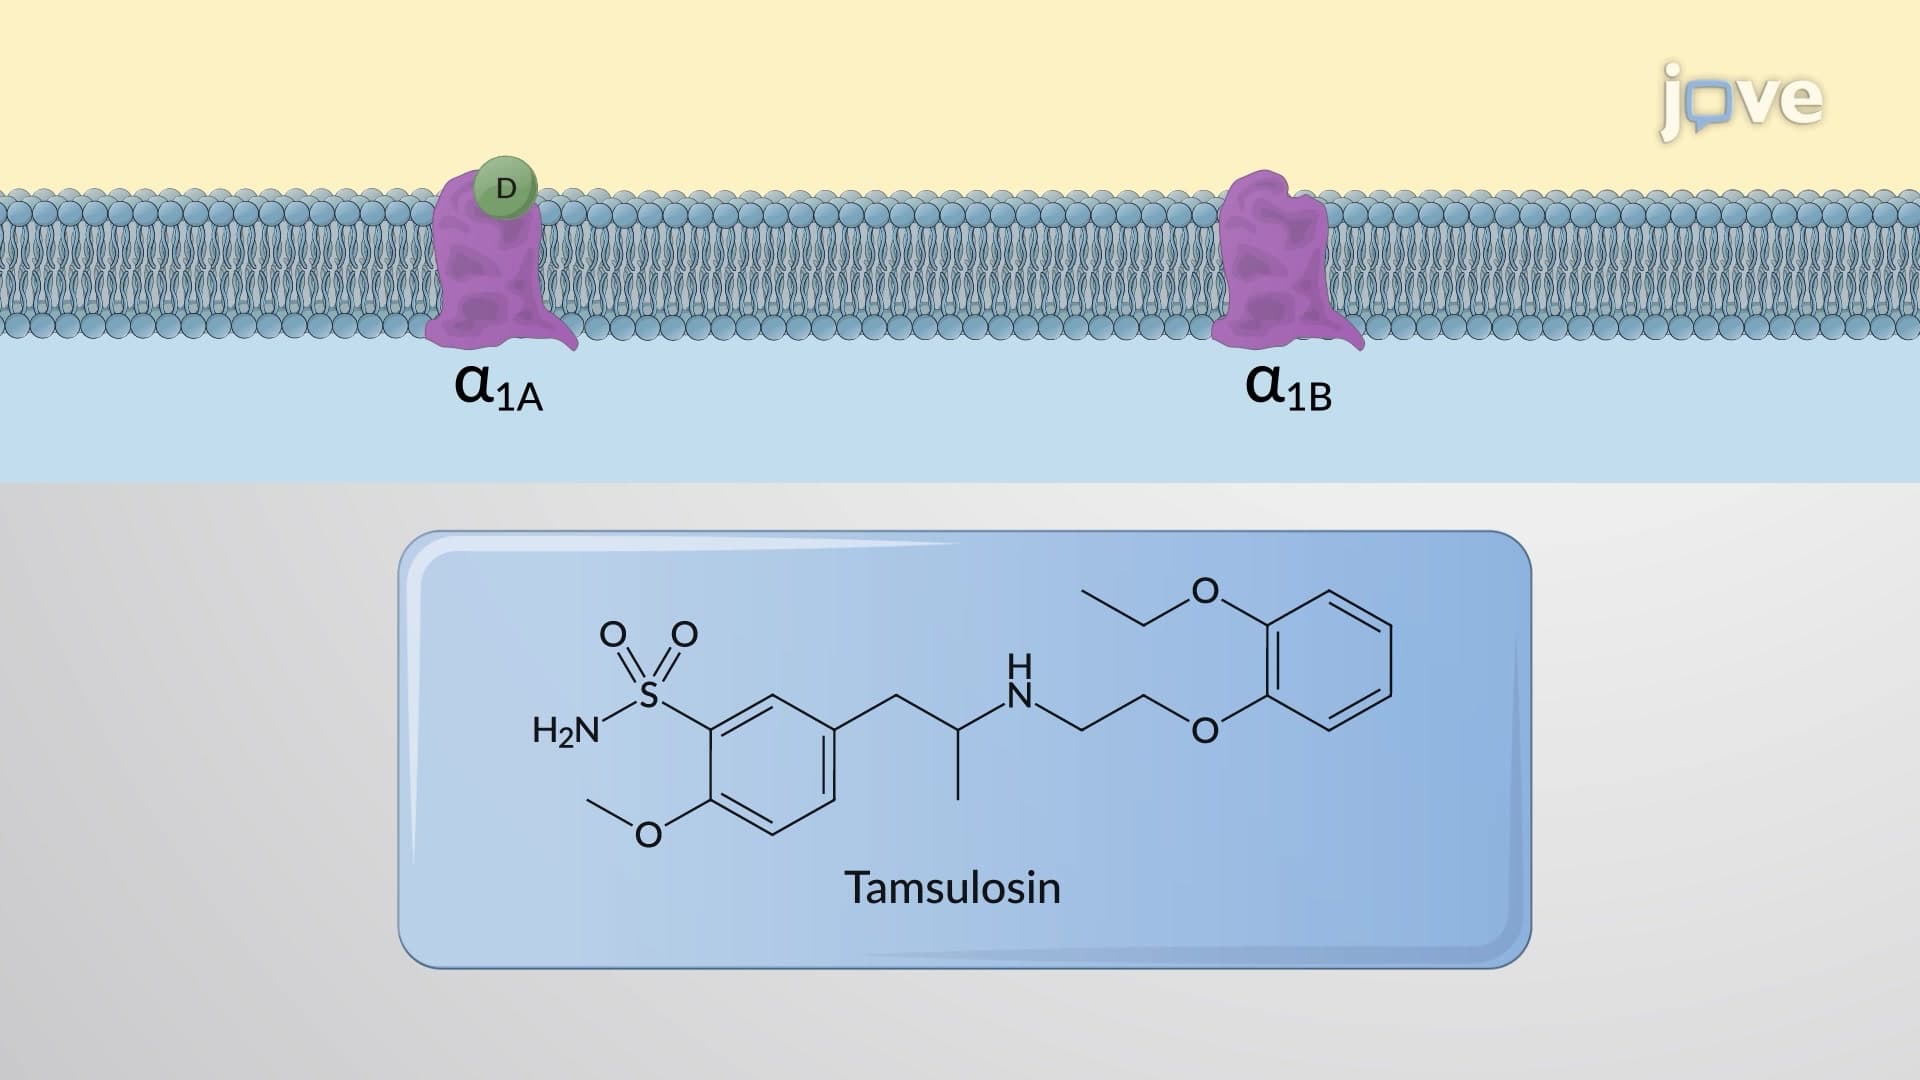
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase...
 01:25
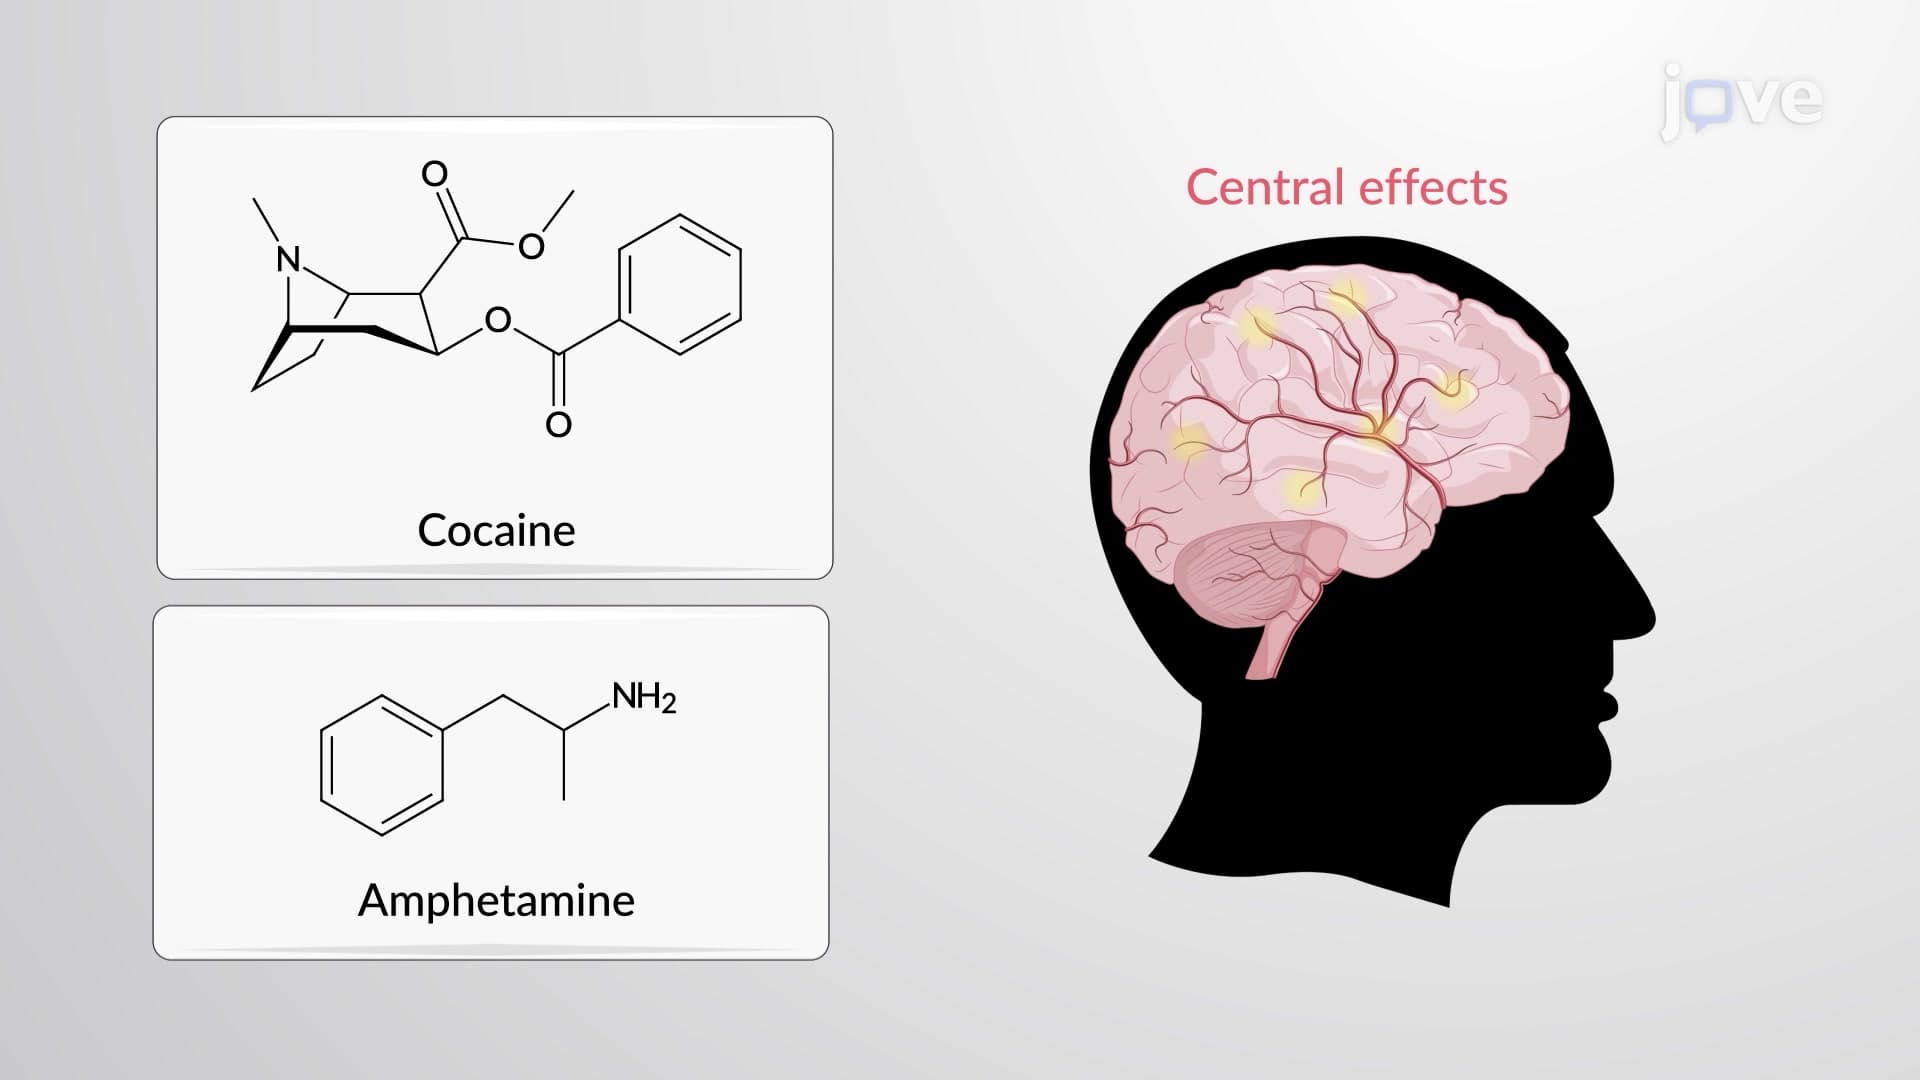
Adrenergic Agonists: Indirect-Acting Agents
One mechanism involves depleting stored catecholamines by displacing them from synaptic vesicles. These agents, known as "displacers," are transported into vesicles at the expense of noradrenaline. Examples include amphetamine and tyramine, which lack a catechol moiety, resulting in prolonged action, improved oral...
 01:24
Antiarrhythmic Drugs: Class II Agents as β-Adrenergic Blockers
 01:27
Adrenergic Receptors (Adrenoceptors): Classification
α-Adrenoceptors
α-Adrenoceptors are classified into two main subtypes: α1 and α2. The α1 adrenoceptors,...
 01:21
Drugs Affecting Neurotransmitter Release or Uptake