Related Experiment Video
Updated: Mar 8, 2026
Laminectomy for the Removal of Thoracic Ossification of the Ligamentum Flavum TOLF Using Ultrasonic and Conventional Osteotomes
Published on: April 21, 2023
Surgical Technique for Decompression of Severe Thoracic Myelopathy due to Tuberous Ossification of Ligamentum Flavum
Ting Wang1, Chuqiang Yin, Dechun Wang
1Department of Spinal Surgery, Affiliated Hospital of Qingdao University, Qingdao, China.

Study Design:
Retrospective review.
Objective:
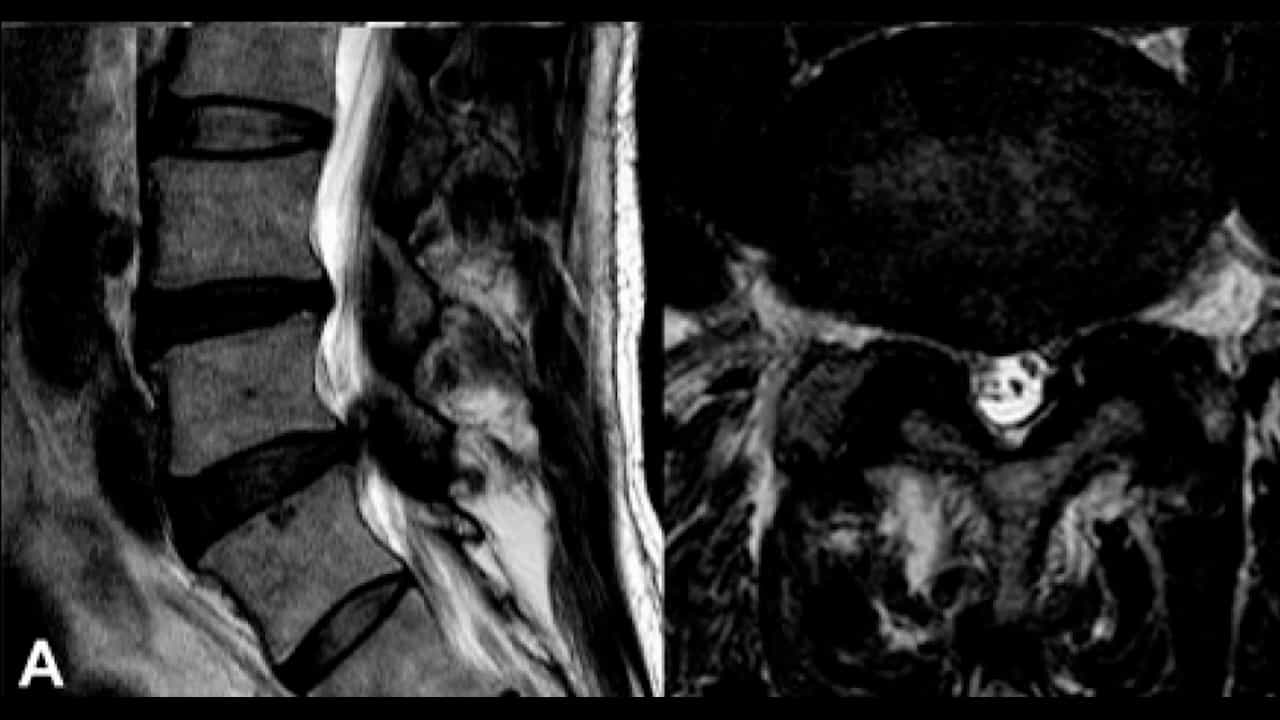
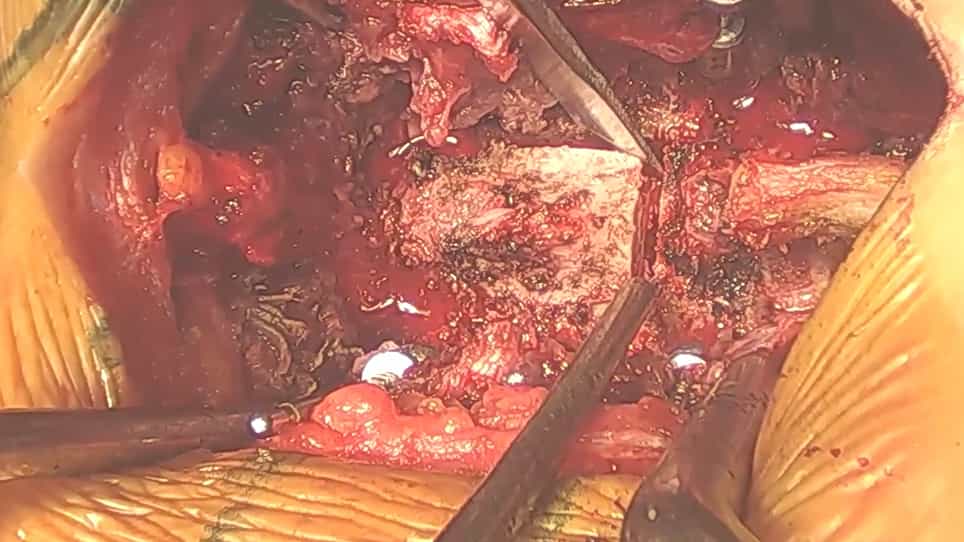
To describe a safe surgical procedure, en bloc resection of the posterior wall of the thoracic canal, for the decompression of severe thoracic myelopathy caused by tuberous ossification of the ligamentum flavum (OLF).
Summary Of Background Data:
OLF has been widely recognized as a cause of thoracic myelopathy in East Asia. Surgical decompression of thoracic myelopathy caused by OLF is technically demanding. Although several surgical decompression procedures have been described, acute neurological deterioration is common.
Materials And Methods:
Eighteen patients with severe thoracic myelopathy caused by tuberous OLF underwent posterior decompression via segmental en bloc resection of the posterior wall of the thoracic canal. The ossified ligamentum flavum, laminae, and partial facet joints of each segment were resected en bloc. Ossified dura mater was removed if present. Posterior fixation with pedicle screws was followed by lateral bone graft fusion.
Results:
The mean preoperative modified Japanese Orthopaedic Association score (total score, 11) was 4.1 (range, 2-5). Postoperatively, no neurological deterioration occurred, and all patients improved clinically. With an average follow-up of 31.2 months (range, 24-42 mo), the average modified Japanese Orthopaedic Association score was 7.8 (range, 6-10), representing a 2- to 5-point improvement. The average improvement rate was 55.2% (range, 33.3%-83.3%). Most patients were functionally independent at the last follow-up. Forty ossified segments were resected. The average time required for the resection of 1 segment was 77 minutes. Intraoperatively, dural ossification was noted in 11 patients. Complete resection was performed in all patients. Cerebrospinal fluid leakage occurred in 5 patients.
Conclusion:
Segmental en bloc resection of the posterior wall of the thoracic canal is a safe and effective alternative for OLF-related severe thoracic myelopathy.