Related Experiment Video
Updated: Mar 8, 2026
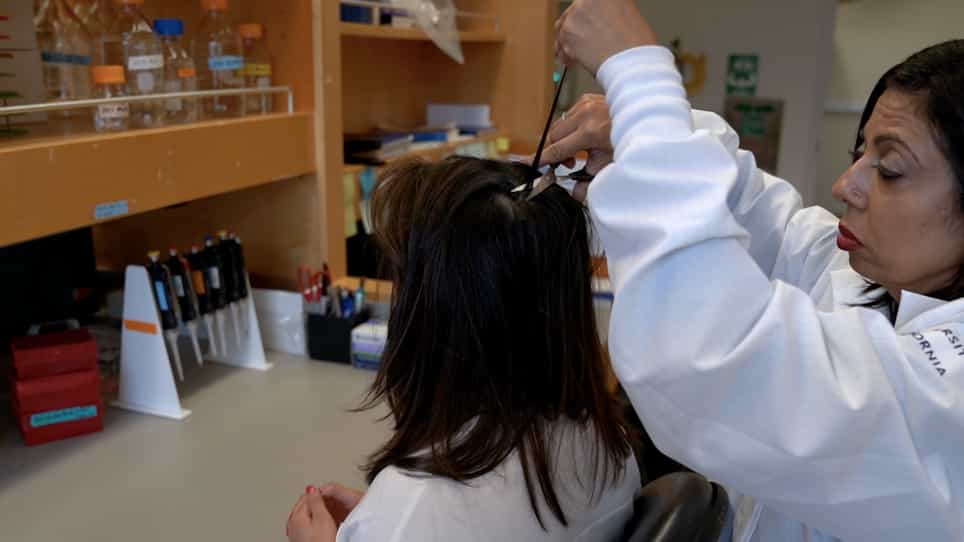
Validated LC-MS/MS Panel for Quantifying 11 Drug-Resistant TB Medications in Small Hair Samples
Published on: May 19, 2020
Anti-TB drug concentrations and drug-associated toxicities among TB/HIV-coinfected patients
C Sekaggya-Wiltshire1, A von Braun1, A U Scherrer2,3
1Infectious Diseases Institute, College of Health Sciences, Makerere University, Kampala, Uganda.

Background:
Toxicities due to anti-TB treatment frequently occur among TB/HIV-coinfected patients.
Objectives:
To determine the association between anti-TB drug concentrations and the occurrence of hepatotoxicity and peripheral neuropathy among TB/HIV-coinfected patients.
Methods:
TB/HIV-coinfected patients were started on standard dose anti-TB treatment according to WHO guidelines. Anti-TB drug concentrations were measured using HPLC 1, 2 and 4 h after drug intake at 2, 8 and 24 weeks following initiation of TB treatment. Participants were assessed for hepatotoxicity using Division of AIDS toxicity tables and for peripheral neuropathy using clinical assessment of tendon reflexes, vibration sensation or symptoms. Cox regression was used to determine the association between toxicities and drug concentrations.
Results:
Of the 268 patients enrolled, 58% were male with a median age of 34 years. Participants with no hepatotoxicity or mild, moderate and severe hepatotoxicity had a median C max of 6.57 (IQR 4.83-9.41) μg/mL, 7.39 (IQR 5.10-10.20) μg/mL, 7.00 (IQR 6.05-10.95) μg/mL and 3.86 (IQR 2.81-14.24) μg/mL, respectively. There was no difference in the median C max of rifampicin among those who had hepatotoxicity and those who did not ( P = 0.322). There was no difference in the isoniazid median C max among those who had peripheral neuropathy 2.34 (1.52-3.23) μg/mL and those who did not 2.21 (1.45-3.11) μg/mL ( P = 0.49).
Conclusions:
There was no association between rifampicin concentrations and hepatotoxicity or isoniazid concentrations and peripheral neuropathy among TB/HIV-coinfected patients.
More Related Videos


Related Concept Videos
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:28
Pulmonary Tuberculosis V
Latent tuberculosis infection occurs when TB bacteria are present in a person's body, but are not causing illness or symptoms. It is not contagious, and preventive treatment is crucial to avoid the...
 01:26
Pulmonary Tuberculosis IV
Several diagnostic approaches are used to detect TB. The conventional method is the Tuberculin Skin Test (TST), also known as the Mantoux test. However, this method has...
 01:16
Drug toxicity: Idiosyncratic Reactions
 01:28
Pulmonary Tuberculosis II
Here is a detailed explanation of its pathophysiology:
Transmission: The process begins when a person inhales droplet nuclei containing M. tuberculosis. These are typically released into the air when an individual with pulmonary or...
 01:29
Therapeutic Drug Monitoring: Affecting Factors