Related Experiment Video
Updated: Mar 8, 2026


Scanning Skeletal Remains for Bone Mineral Density in Forensic Contexts
Published on: January 29, 2018
The relationship of maternal bone density with nutritional rickets in Nigerian children
Jennifer Hsu1, Philip R Fischer2, John M Pettifor3
1Mayo Medical School, Mayo Clinic, 200 First Street, SW, Rochester, MN 55905, United States; Department of Pediatrics, Kaiser Permanente Oakland Medical Center, 3600 Broadway, Oakland, CA 94611, United States.

Abstract:
Factors that affect maternal bone mineral density may be related to the risk of nutritional rickets in their offspring. Our aim was to determine the relationship between maternal areal bone mineral density (aBMD) and rickets in Nigerian children. Using a case-control design, we measured forearm aBMD in 56 and 135 mothers of children with and without nutritional rickets, respectively. Active rickets was confirmed or excluded in all children radiographically. Using logistic regression, we assessed the association of maternal aBMD, adjusted for parity, pregnancy and lactation status, duration of most recent completed lactation, age of menarche, height, body mass index, and maternal age with nutritional rickets. The median (range) age of all mothers was 30years (17-47years), and parity was 4 (1-12). A total of 36 (19%) were pregnant and 55 (29%) were currently breast feeding. Mean (±SD) metaphyseal forearm aBMDs were 0.321±0.057 and 0.316±0.053g/cm2 in mothers of children with and without rickets, respectively (P=0.60). Diaphyseal forearm aBMDs were 0.719±0.071 and 0.715±0.072g/cm2, respectively (P=0.69). In an adjusted analysis, maternal forearm aBMD, bone mineral content and bone area at metaphyseal and diaphyseal sites were not associated with rickets in the child. In the adjusted analysis, rickets was associated with shorter duration of most recently completed lactation (aOR 0.91 for each additional month; 95% CI 0.83-0.99), older maternal age (aOR 1.07 for each additional year; 1.00-1.14), and less frequent maternal use of lead-containing eye cosmetics (aOR 0.20; 95% CI 0.05-0.64), without any difference in maternal blood lead levels. Maternal age, parity, age of menarche, height, and body mass index were not associated with having had a child with rickets in multivariate analysis. Nutritional rickets in Nigerian children was not associated with maternal forearm aBMD. Other unidentified maternal characteristics and practices likely contribute to the risk of rickets in Nigerian children.


Related Concept Videos
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:25
Role of Vitamins in Maintaining Bone Health
Vitamin A
Vitamin A is involved in the process of bone remodeling. Retinoic acid, the active metabolite of Vitamin A, has nuclear receptors in osteoblasts and osteoclasts, which are involved in bone remodeling.
Vitamin B12
Vitamin B12 acts as a cofactor during the formation of osteoblast-related proteins, such as osteocalcin. Vitamin B12 plays a role...
 01:31
Essential Minerals for Bone Health
Calcium and Phosphorus
Calcium is a critical component of bones, especially in the form of calcium phosphate and calcium carbonate. Since the body cannot make calcium, it must be obtained from the diet. However, calcium cannot be absorbed from the small intestine without...
 01:10
Nature and Nurture
 01:17
Hormones and Bone Tissue
Hormones That Influence Osteoblasts and/or Maintain the Matrix
Several hormones are necessary for controlling bone growth and maintaining the bone matrix. The pituitary gland secretes growth hormone (GH), which, as its name implies, controls bone growth. This happens in several ways: first, it triggers chondrocyte...
 01:24
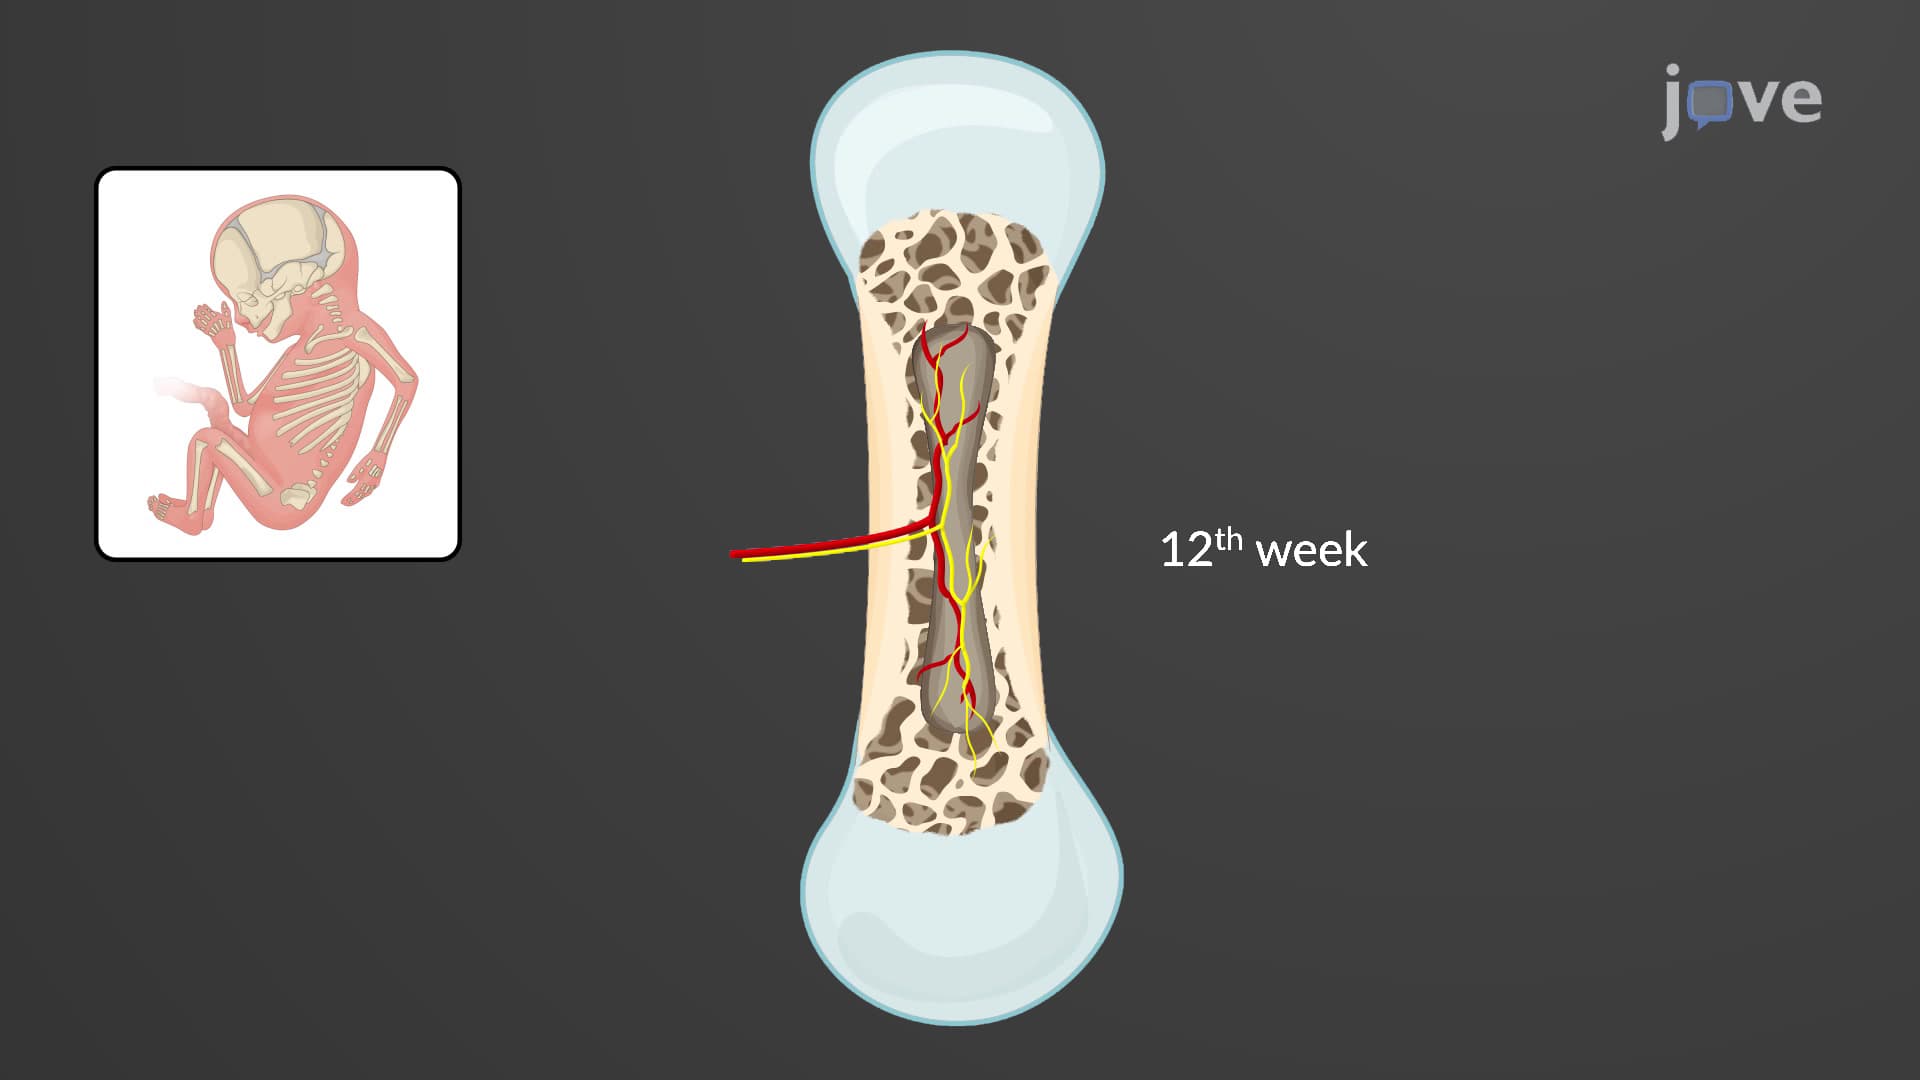
Bone Formation by Endochondral Ossification