Related Experiment Video
Updated: Mar 8, 2026
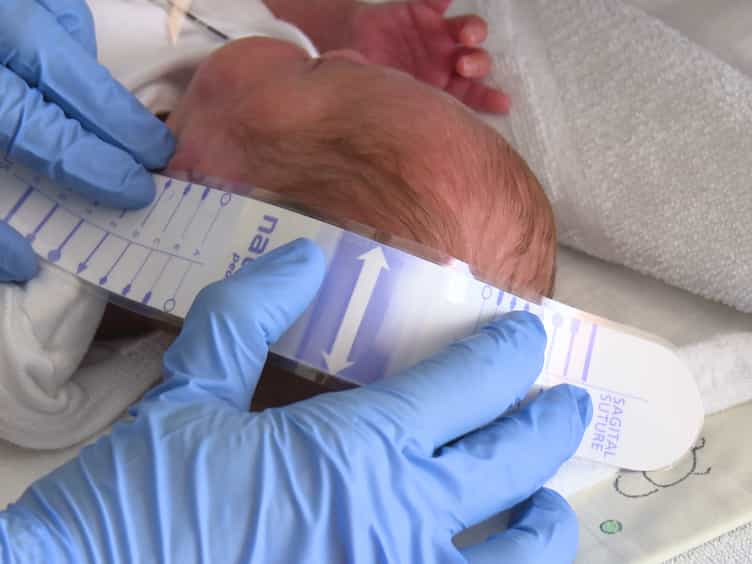

Application of an Amplitude-integrated EEG Monitor Cerebral Function Monitor to Neonates
Published on: September 6, 2017
Time to electroencephalography is independently associated with outcome in critically ill neonates and children
Iván Sánchez Fernández1,2, Arnold J Sansevere1, Rejean M Guerriero1
1Division of Epilepsy and Clinical Neurophysiology, Department of Neurology, Boston Children's Hospital, Harvard Medical School, Boston, Massachusetts, U.S.A.

Insights
Continuous EEG monitoring in the ICU is crucial for identifying mortality risk factors in critically ill neonates and children. Delays in starting monitoring and the presence of status epilepticus significantly increase mortality risk in both groups.
Area of Science:
- Neurology
- Critical Care Medicine
- Pediatrics
Background:
- Continuous electroencephalography (cEEG) monitoring is vital for managing critically ill neonates and children in the intensive care unit (ICU).
- Identifying factors associated with in-hospital mortality in this vulnerable population is essential for improving outcomes.
- Understanding these risk factors can guide timely interventions and resource allocation.
Purpose of the Study:
- To determine the independent factors associated with in-hospital mortality in neonates and pediatric patients undergoing cEEG monitoring in the ICU.
- To analyze the impact of time to cEEG initiation and seizure activity on mortality.
- To provide data that can inform clinical practice and patient management.
Main Methods:
- A retrospective observational study was conducted on 625 patients (birth to 21 years) who underwent clinically indicated cEEG in the ICU between 2011 and 2013.
- In-hospital mortality was the primary outcome measure.
- Statistical analysis controlled for relevant demographic factors to identify independent predictors of mortality.
Main Results:
- Overall in-hospital mortality was 14.2% (89 patients).
- In neonates, prematurity, presence of status epilepticus (SE), and longer time from ICU admission to cEEG initiation were independent predictors of mortality.
- In pediatric patients, absence of seizures, presence of SE, and longer time from ICU admission to cEEG initiation were independent predictors of mortality.
Conclusions:
- The presence of electrographic status epilepticus (SE) and delayed initiation of cEEG monitoring are significant independent factors associated with in-hospital mortality in both neonates and pediatric patients.
- These findings underscore the importance of prompt cEEG monitoring in critically ill children to identify and manage potentially life-threatening neurological events.
Objective:
To identify factors associated with in-hospital mortality in neonates and children undergoing continuous electroencephalography (cEEG) monitoring in the intensive care unit (ICU).
Methods:
We performed a retrospective observational study in patients from birth to 21 years of age who underwent clinically indicated cEEG in the ICU from 2011 to 2013. The main outcome measure was in-hospital mortality.
Results:
Six-hundred and twenty-five patients (54.2% male) met eligibility criteria, of whom 211 were neonates (55% male, 24.8% premature) and 414 were pediatric patients (53.9% male). Electrographic seizures occurred in 176 patients (28.2%) and status epilepticus (SE) occurred in 20 (11.4%). The time from ICU admission to cEEG initiation was 16.7 (5.1-94.4) h. Eighty-nine patients (14.2%) (30 [14.2%] neonates, and 59 [14.3%] pediatric patients) died in the hospital. In neonates-after controlling for gender and prematurity-independent factors associated with mortality were prematurity (odds ratio [OR] 2.63. 95% confidence interval [CI] 1.06-6.5, p = 0.037), presence of status epilepticus (SE); OR 8.82, 95% CI 1.74-44.57, p = 0.008), and time from ICU admission to initiation of cEEG (OR 1.002, 95% CI 1.001-1.004 per hour, p = 0.008]. In pediatric patients-after controlling for gender and age-independent factors associated with mortality were the absence of seizures factors associated with mortality were absence of seizures (OR = 4.3, (95% CI: 1.5-12.4), p = 0.007), the presence of SE (OR 7.76, 95% CI 1.47-40.91, p = 0.016), and the time from ICU admission to initiation of cEEG (OR 1.001, 95% CI 1.0002-1.001, per hour, p = 0.005].
Significance:
Both presence of electrographic SE and time from ICU admission to cEEG initiation were independent factors associated with mortality in neonates and pediatric patients with cEEG in the ICU.