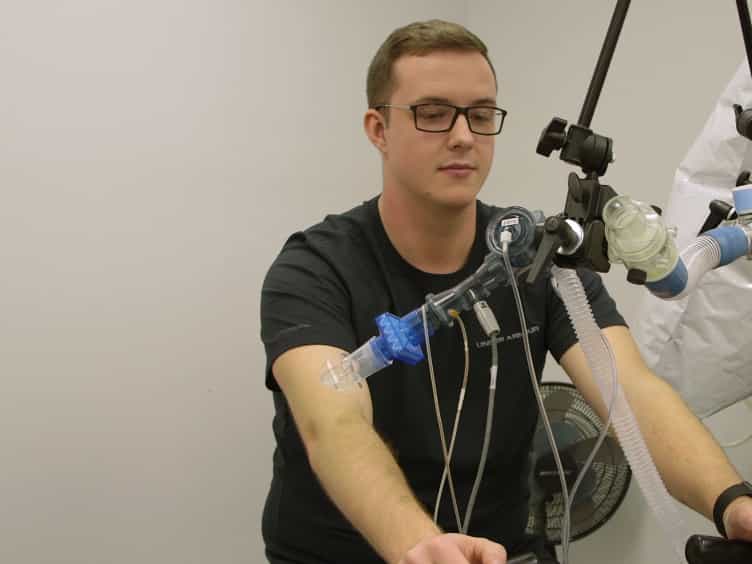
Evaluation of carbon dioxide rebreathing during exercise assisted by noninvasive ventilation with plateau exhalation
Yong-Er Ou1, Zhi-Min Lin1, Dong-Ming Hua1
1State Key Laboratory of Respiratory Disease, National Clinical Research Center for Respiratory Disease, Guangzhou Institute of Respiratory Disease, First Affiliated Hospital of Guangzhou Medical University, Guangzhou, People's Republic of China.

Abstract:
Noninvasive ventilation with a plateau exhalation valve (PEV) is often used as an adjunct to exercise to achieve a physiologic training effect in severe chronic obstructive pulmonary disease (COPD) patients. However, during exercise, with the increase of exhalation flow and respiratory rate and limited capability of PEV to exhale gases out of the circuit, it is still unknown whether CO2 rebreathing occurs in COPD patients ventilated during exercise assisted by single-limb circuit with a PEV. A maximal symptom-limited cycle exercise test was performed while ventilated on pressure support (inspiratory:expiratory pressure 14:4 cmH2O) in 18 male patients with stable severe COPD (mean ± standard deviation, forced expiratory volume in 1 s: 29.5%±6.9% predicted). At rest and during exercise, breathing pattern, mean expiratory flow, mean expiratory flow of PEV, and the mean inspiratory fraction of CO2 (tidal fractional concentration of inspired CO2 [FiCO2]) reinsufflated from the circuit was measured for each breath. In comparison with rest, with the significant increase of mean expiratory flow (0.39±0.15 vs 0.82±0.27 L/s), fractional concentration of end-tidal CO2 (2.6%±0.7% vs 5.5%±0.6%), and the significant decrease of mean expiratory flow of PEV (0.41±0.02 vs 0.39±0.03 L/s), tidal FiCO2 significantly increased at peak exercise (0.48%±0.19% vs 1.8%±0.6%) in patients with stable severe COPD. The inflection point of obvious CO2 rebreathing was 0.67±0.09 L/s (95% confidence interval 0.60-0.73 L/s). Ventilated by a single-limb tubing with PEV caused CO2 rebreathing to COPD patients during exercise. Patients with mean expiratory flow >0.60-0.73 L/s may be predisposed to a higher risk of CO2 rebreathing.
More Related Videos
 07:52
Expired CO2 Measurement in Intubated or Spontaneously Breathing Patients from the Emergency Department
Published on: January 29, 2011
 08:34
Investigation into Deep Breathing through Measurement of Ventilatory Parameters and Observation of Breathing Patterns
Published on: September 16, 2019
Related Concept Videos
 01:17
Assessment of Diffusion and Perfusion
The Role of Diffusion in Respiration
Diffusion is the process by which molecules move from an area of higher concentration to an area of lower concentration. In the respiratory system, this...
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation...
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:14
Ventilatory Modes
There are three ventilatory modes: full support, partial support, and spontaneous. These are described below.
Full Support Modes
Full support modes include controlled mechanical ventilation, continuous mandatory...
 01:23
Assessment of Respiration
Subjective Assessment: Nurses interview the patient to gather information directly during the subjective assessment. It includes questions about the individual's medical history, medications, and symptoms, focusing on past respiratory conditions like...