Related Experiment Video
Updated: Mar 8, 2026
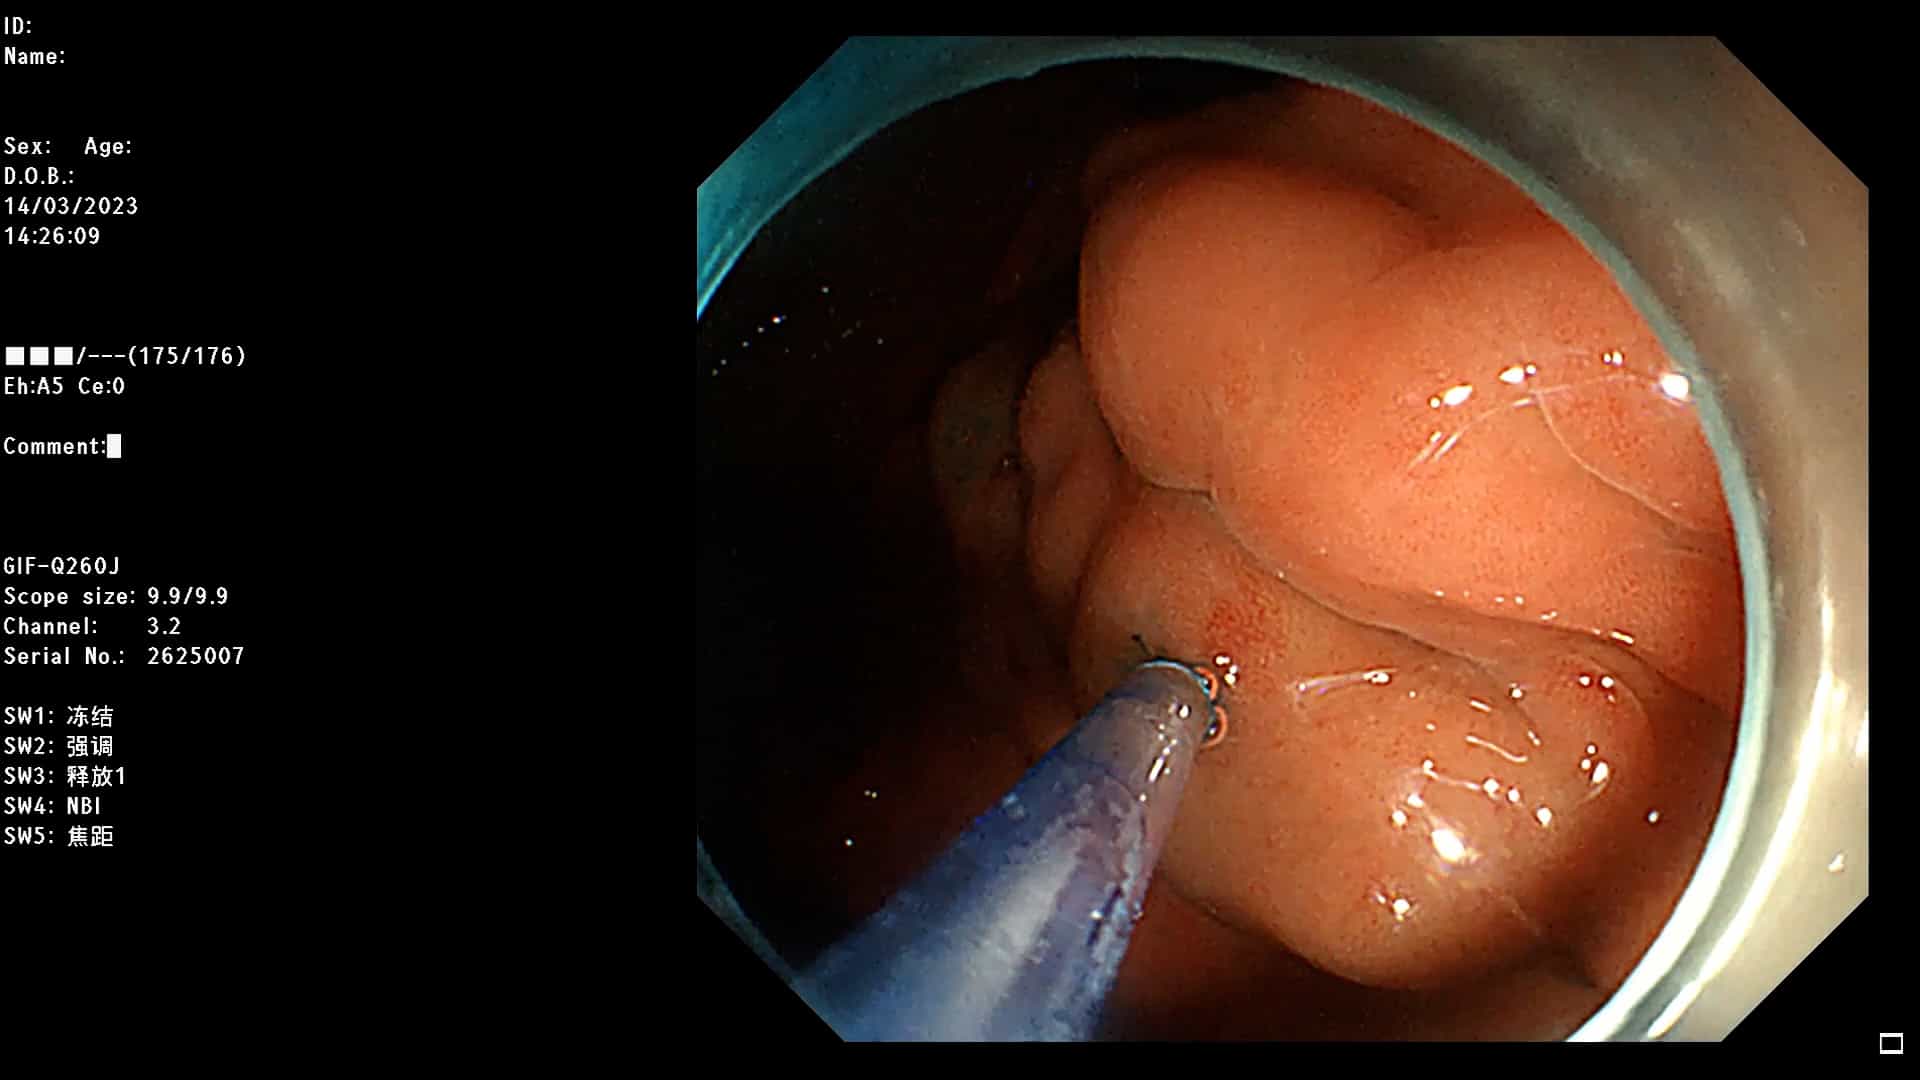
Endoscopic Injection Sclerotherapy Assisted by Cyanoacrylate and Clips for Gastroesophageal Varices
Published on: June 13, 2025
Acute lower GI bleeding in the UK: patient characteristics, interventions and outcomes in the first nationwide audit
Kathryn Oakland1, Richard Guy2, Raman Uberoi3
1Clinical Research, NHS Blood and Transplant, Oxford, UK.

Objective:
Lower GI bleeding (LGIB) is a common reason for emergency hospital admission, although there is paucity of data on presentations, interventions and outcomes. In this nationwide UK audit, we describe patient characteristics, interventions including endoscopy, radiology and surgery as well as clinical outcomes.
Design:
Multicentre audit of adults presenting with LGIB to UK hospitals over 2 months in 2015. Consecutive cases were prospectively enrolled by clinical teams and followed for 28 days.
Results:
Data on 2528 cases of LGIB were provided by 143 hospitals. Most were elderly (median age 74 years) with major comorbidities, 29.4% taking antiplatelets and 15.9% anticoagulants. Shock was uncommon (58/2528, 2.3%), but 666 (26.3%) received a red cell transfusion. Flexible sigmoidoscopy was the most common investigation (21.5%) but only 2.1% received endoscopic haemostasis. Use of embolisation or surgery was rare, used in 19 (0.8%) and 6 (0.2%) cases, respectively. 48% patients underwent no inpatient investigations. The most common diagnoses were diverticular bleeding (26.4%) and benign anorectal conditions (16.7%). Median length of stay was 3 days, 13.6% patients rebled during admission and 4.4% were readmitted with bleeding within 28 days. In-hospital mortality was 85/2528 (3.4%) and was highest in established inpatients (17.8%, p<0.0001) and in patients experiencing rebleeding (7.1%, p<0.0001).
Conclusions:
Patients with LGIB have a high burden of comorbidity and frequent antiplatelet or anticoagulant use. Red cell transfusion was common but most patients were not shocked and required no endoscopic, radiological or surgical treatment. Nearly half were not investigated. In-hospital mortality was related to comorbidity, not severe haemorrhage.
Related Concept Videos
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...
 01:23
Gastritis III: Clinical Manifestations and Management
Clinical manifestations of acute gastritis
The patient with acute gastritis may have a rapid onset of symptoms, such as epigastric pain or discomfort, dyspepsia, anorexia, hiccups, or nausea and vomiting, which can last from a few hours to a few days. Erosive or hemorrhagic gastritis may cause bleeding, which may manifest as blood in vomit or as...
 01:24
Esophageal Varices-I: Introduction
 01:23
Lower GI Series: Barium Enema
Procedure Details
The examination begins by inserting a lubricated rectal tube into the patient's rectum to administer a radiopaque barium solution. The barium flow is carefully...
 01:30
Peptic Ulcer Disease I: Introduction
An acute ulcer, marked by superficial erosion and minimal inflammation, swiftly resolves upon identifying and addressing the underlying cause. In contrast, a chronic ulcer persists, potentially eroding through the muscular wall and forming fibrous tissue.
Peptic ulcers can also be...
 01:27
Inflammatory Bowel Disease I: Ulcerative Colitis
Inflammatory bowel disease, or IBD, encompasses a group of disorders characterized by chronic inflammation or ulceration of the gastrointestinal tract.
Risk Factors
The exact cause of IBD remains unclear, although it is believed to be due to a mix of genetic, environmental, microbial, and immune factors. Genetic factors are significant in determining susceptibility to IBD, with family history being a critical risk factor. Individuals with a first-degree relative who has IBD are at...