Related Experiment Video
Updated: Mar 8, 2026


Author Spotlight: Improved Localization and Monitoring of Coronary Flow Reserve Using Modified PLAX View in Mice
Published on: August 25, 2023
Does heart rate variability correlate with long-term prognosis in myocardial infarction patients treated by early
Leonida Compostella1, Nenad Lakusic1, Caterina Compostella1
1Leonida Compostella, Li Van Stella Truong, Fabio Bellotto, Preventive Cardiology and Rehabilitation, Istituto Codivilla-Putti, I-32043 Cortina d'Ampezzo (BL), Italy.

Insights
Depressed heart rate variability (HRV) is not a significant predictor of long-term outcomes in patients with myocardial infarction (MI) treated with immediate reperfusion. Standard HRV parameters lack prognostic value in this modern era of acute cardiac care.
Area of Science:
- Cardiology
- Autonomic Nervous System Function
- Clinical Outcomes Research
Background:
- Heart rate variability (HRV) is a marker of autonomic function, and depressed HRV has been associated with adverse outcomes after myocardial infarction (MI).
- The prognostic significance of HRV may have changed with the advent of immediate reperfusion therapies for acute MI.
Purpose of the Study:
- To determine the prevalence of depressed HRV in patients following acute MI treated with early reperfusion.
- To evaluate the prognostic significance of HRV parameters in predicting long-term clinical outcomes in the current era of reperfusion therapy.
Main Methods:
- Time-domain HRV analysis (SDNN) was performed on 24-h Holter recordings in 326 patients (STEMI and NSTEMI) two weeks after acute MI treated with reperfusion.
- Patients were followed for a median of 25 months to assess all-cause mortality, cardiac death, and major clinical events (MCE).
- Multivariate Cox regression and Kaplan-Meier analyses were used to correlate HRV parameters with clinical features and long-term outcomes.
Main Results:
- Depressed HRV (SDNN < 70 ms) was found in 16% of patients; prevalence was similar between STEMI and NSTEMI groups.
- Female sex, history of diabetes, and left ventricular ejection fraction < 40% were associated with lower SDNN values.
- Long-term outcomes (mortality and MCE) did not significantly differ between patients with the lowest HRV quartile and those with higher HRV levels.
- Left ventricular ejection fraction < 40% was associated with worse event-free survival.
Conclusions:
- The prevalence of depressed HRV after acute MI treated with reperfusion is similar to historical data from the pre-reperfusion era.
- Traditional HRV parameters, such as SDNN, do not appear to hold significant prognostic value for long-term outcomes in patients receiving immediate coronary reperfusion.
- Left ventricular ejection fraction remains a crucial prognostic indicator in post-MI patients.
Aim:
To assess the prevalence of depressed heart rate variability (HRV) after an acute myocardial infarction (MI), and to evaluate its prognostic significance in the present era of immediate reperfusion.
Methods:
Time-domain HRV (obtained from 24-h Holter recordings) was assessed in 326 patients (63.5 ± 12.1 years old; 80% males), two weeks after a complicated MI treated by early reperfusion: 208 ST-elevation myocardial infarction (STEMI) patients (in which reperfusion was successfully obtained within 6 h of symptoms in 94% of cases) and 118 non-ST-elevation myocardial infarction (NSTEMI) patients (percutaneous coronary intervention was performed within 24 h and successful in 73% of cases). Follow-up of the patients was performed via telephone interviews a median of 25 mo after the index event (95%CI of the mean 23.3-28.0). Primary end-point was occurrence of all-cause or cardiac death; secondary end-point was occurrence of major clinical events (MCE, defined as mortality or readmission for new MI, new revascularization, episodes of heart failure or stroke). Possible correlations between HRV parameters (mainly the standard deviation of all normal RR intervals, SDNN), clinical features (age, sex, type of MI, history of diabetes, left ventricle ejection fraction), angiographic characteristics (number of coronary arteries with critical stenoses, success and completeness of revascularization) and long-term outcomes were analysed.
Results:
Markedly depressed HRV parameters were present in a relatively small percentage of patients: SDNN < 70 ms was found in 16% and SDNN < 50 ms in 4% of cases. No significant differences were present between STEMI and NSTEMI cases as regards to their distribution among quartiles of SDNN (χ2 =1.536, P = 0.674). Female sex and history of diabetes maintained a significant correlation with lower values of SDNN at multivariate Cox regression analysis (respectively: P = 0.008 and P = 0.008), while no correlation was found between depressed SDNN and history of previous MI (P = 0.999) or number of diseased coronary arteries (P = 0.428) or unsuccessful percutaneous coronary intervention (PCI) (P = 0.691). Patients with left ventricle ejection fraction (LVEF) < 40% presented more often SDNN values in the lowest quartile (P < 0.001). After > 2 years from infarction, a total of 10 patients (3.1%) were lost to follow-up. Overall incidence of MCE at follow-up was similar between STEMI and NSTEMI (P = 0.141), although all-cause and cardiac mortality were higher among NSTEMI cases (respectively: 14% vs 2%, P = 0.001; and 10% vs 1.5%, P = 0.001). The Kaplan-Meier survival curves for all-cause mortality and for cardiac deaths did not reveal significant differences between patients with SDNN in the lowest quartile and other quartiles of SDNN (respectively: P = 0.137 and P = 0.527). Also the MCE-free survival curves were similar between the group of patients with SDNN in the lowest quartile vs the patients of the other SDNN quartiles (P = 0.540), with no difference for STEMI (P = 0.180) or NSTEMI patients (P = 0.541). By the contrary, events-free survival was worse if patients presented with LVEF < 40% (P = 0.001).
Conclusion:
In our group of patients with a recent complicated MI, abnormal autonomic parameters have been found with a prevalence that was similar for STEMI and NSTEMI cases, and substantially unchanged in comparison to what reported in the pre-primary-PCI era. Long-term outcomes did not correlate with level of depression of HRV parameters recorded in the subacute phase of the disease, both in STEMI and in NSTEMI patients. These results support lack of prognostic significance of traditional HRV parameters when immediate coronary reperfusion is utilised.
More Related Videos


Related Concept Videos
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:30
Factors Influencing Heart Rate
Let us explore the significant factors affecting heart rate, including age, body temperature, posture, acute pain, chemical influences,...
 01:20
Blood Studies for Cardiovascular System I: Cardiac Biomarkers
The essential diagnostic tools for detecting myocardial necrosis and monitoring individuals suspected of having acute coronary syndrome (ACS) include:
Troponins
Troponins, particularly cardiac troponins I and T, are the most precise and sensitive markers of myocardial injury. They are detectable within 4-6 hours of myocardial injury and remain...
 01:17
Ischemic Heart Disease: Overview
Atherosclerosis, the primary malefactor, orchestrates this dangerous condition. It manifests as the accumulation of fatty deposits, akin to insidious plaques, within arterial walls. As time elapses, these plaques metamorphose, hardening and...
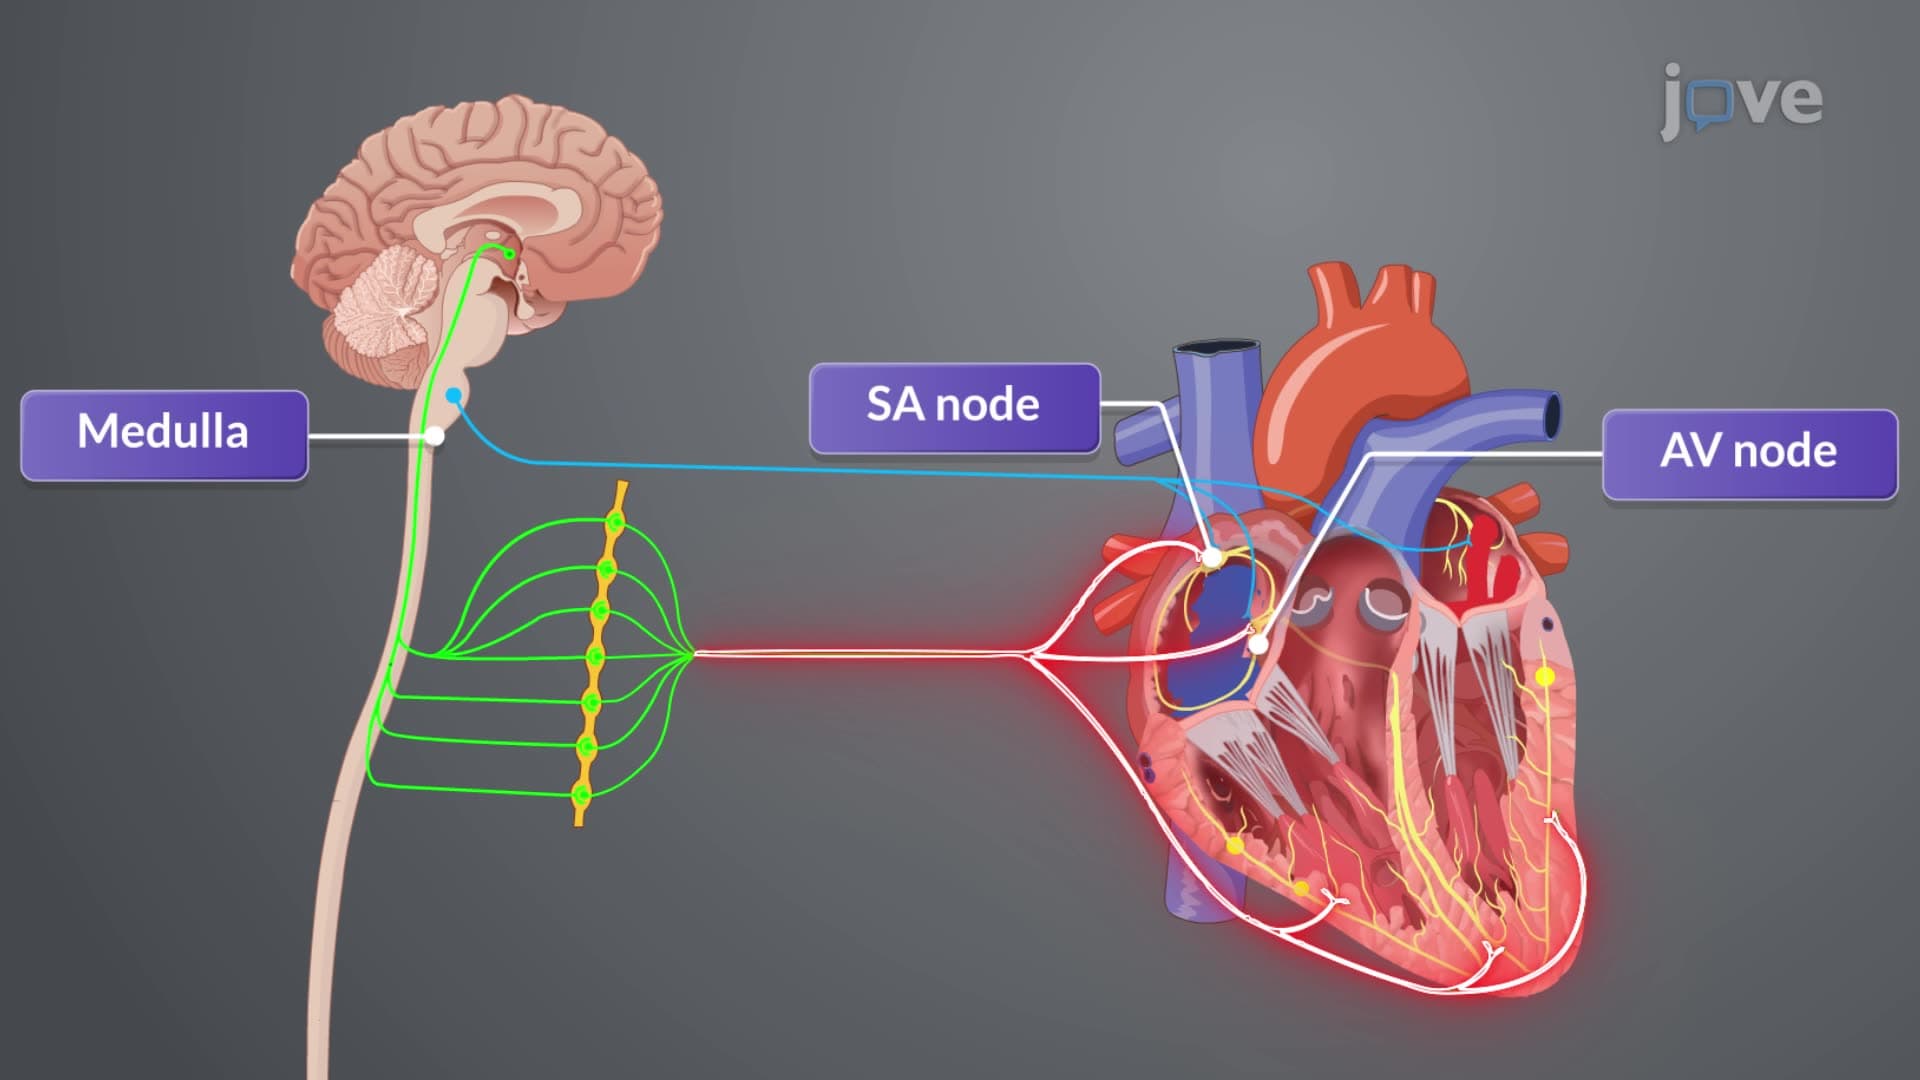 01:19
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...
 01:30
Heart Failure IV: Classification and Diagnostic Evaluation