Related Experiment Video
Updated: Mar 7, 2026
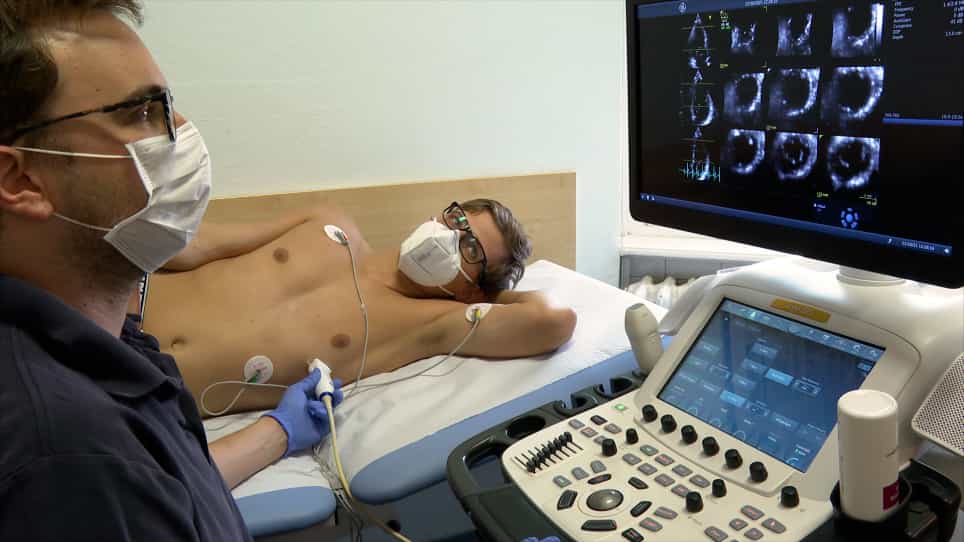

Evaluation of Left Ventricular Structure and Function using 3D Echocardiography
Published on: October 28, 2020
Prevalence and determinants of left ventricular geometric abnormalities in hypertensive patients: A study based on
Tao Sha1, Yu-Qing Huang2, An-Ping Cai2
1Southern Medical University, Guangzhou 510515, Guangdong, China; Department of Cardiology, Guangdong General Hospital, Guangdong Academy of Medical Sciences, Guangdong Cardiovascular Institute, Guangzhou, 510100, Guangdong, China.

Insights
Hypertension can cause left ventricular (LV) geometric abnormalities, with concentric remodeling being most common. Risk factors like large waist and neck circumference are linked to concentric abnormalities, while BMI and SBP are inversely associated.
Area of Science:
- Cardiology
- Hypertension Research
- Echocardiography
Background:
- Left ventricular (LV) geometric abnormalities are common in hypertensive patients.
- Understanding the specific risk factors associated with different types of LV geometric abnormalities is crucial for targeted interventions.
Purpose of the Study:
- To investigate the association between various risk factors and distinct types of left ventricular (LV) geometric abnormalities in hypertensive individuals.
- To identify differential risk profiles for concentric remodeling, eccentric dilated LVH, and concentric LVH.
Main Methods:
- Retrospective analysis of 2290 hypertensive participants with preserved ejection fraction (≥50%) and no other cardiovascular or valve disease.
- Classification of LV geometric abnormalities based on a new system.
- Statistical analysis to determine associations between risk factors (e.g., BMI, SBP, WC, NC, age, gender, alcohol use, hyperuricemia) and LV geometric patterns.
Main Results:
- LV geometric abnormalities were prevalent in 64.6% of participants.
- Concentric LV remodeling was the most common abnormality (40.3%).
- Large waist circumference (WC) and neck circumference (NC) were associated with concentric remodeling. Body mass index (BMI) and systolic blood pressure (SBP) showed inverse associations.
- SBP and age were linked to eccentric dilated LVH, while male gender was inversely associated. Age was the strongest risk factor for eccentric dilated LVH.
- Age, NC, SBP, hyperuricemia, and alcohol use were positively associated with concentric LVH. BMI and male gender were negatively associated.
Conclusions:
- The prevalence of hypertensive LV geometric abnormality is notably high in rural Southern China.
- Concentric LV geometric abnormalities are associated with a broader range of risk factors compared to eccentric abnormalities.
- Risk factors for concentric abnormalities include large WC and NC, age, SBP, hyperuricemia, alcohol use, BMI, and gender.
Objective:
This study was to determine whether different risk factors were associated with different type of left ventricular (LV) geometric abnormalities.
Methods:
This retrospective analysis included 2290 hypertensive participants without other cardiovascular disease, valve disease and with ejection fraction ≥50%. The type of LV geometric abnormality was defined on the basis of the new classification system.
Results:
LV geometric abnormalities were detected in 1479 subjects (64.6%), wherein concentric LV remodeling is the most common LV geometric abnormality (40.3%). Large waist circumference (WC) and neck circumference (NC) were positively associated with concentric LV remodeling, whereas body mass index (BMI) [odds ratio (OR) 0.89, 95% CI 0.85∼0.92, P < 0.001] and systolic blood pressure (SBP) (OR 0.99, 95% CI 0.98∼0.99, P = 0.018) were inversely associated with concentric abnormalities. SBP and age were positively associated with eccentric dilated LVH, while male was inversely associated with eccentric dilated left ventricular hypertrophy (LVH). Age was the strongest risk factor for eccentric dilated LVH (OR 1.05, 95% CI 1.03∼1.07, P < 0.001). Age, NC, SBP, hyperuricemia, and alcohol use were positively associated with concentric LVH, whereas BMI (OR 0.95, 95% CI 0.90∼0.99, P = 0.033) and male (OR 0.12, 95% CI 0.07∼0.18, P < 0.001) were negatively associated with concentric LVH.
Conclusion:
The prevalence of hypertensive LV geometric abnormality in rural area of Southern China was obvious higher. Compared with eccentric LV geometric abnormalities, there were more risk factors, including large WC and NC, age, NC, SBP, hyperuricemia, alcohol use, BMI and gender, which were associated with concentric LV geometric abnormalities.
More Related Videos


Related Concept Videos
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:20
Mitral Regurgitation I: Introduction
 01:29
Heart Failure II: Pathophysiology
 01:30
Hypertension III: Clinical Manifestations and Diagnostic Studies
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests
 01:25
Aortic Regurgitation III: Medical Management