Related Experiment Video
Updated: Mar 7, 2026
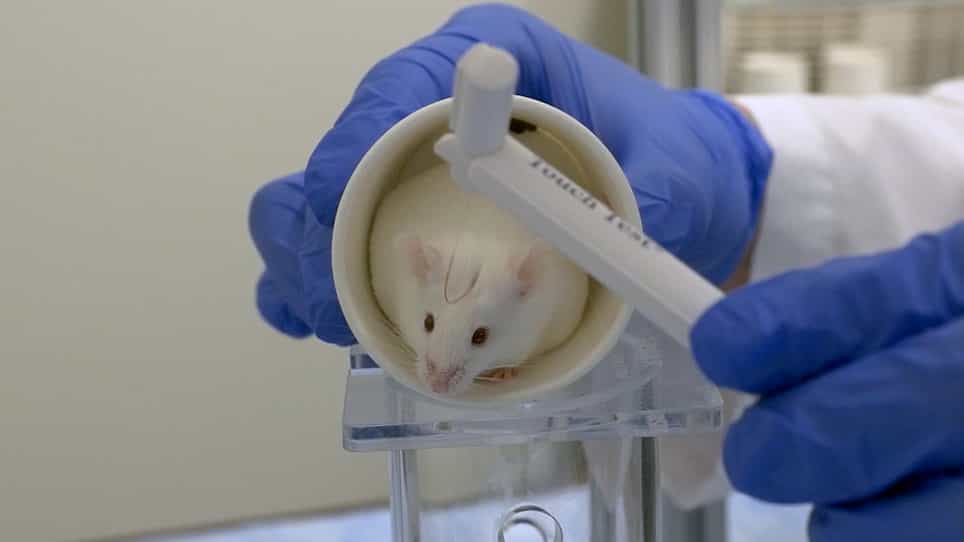

Dural Stimulation and Periorbital von Frey Testing in Mice As a Preclinical Model of Headache
Published on: July 29, 2021
Hypercoagulability and Migraine
Gretchen E Tietjen1, Stuart A Collins1
1Department of Neurology, University of Toledo College of Medicine and Life Sciences, Toledo, OH, USA.

Background:
A growing body of literature suggests that migraineurs, particularly those with aura, have an increased risk for ischemic stroke, but not via enhanced atherosclerosis. The theory that micro-emboli induced ischemia provokes cortical spreading depression (ie, symptomatic aura) in migraineurs but transient ischemic attacks in others highlights a potential role for hypercoagulability as a link between migraine (with aura) and stroke.
Aim:
Our objective is to summarize the literature evaluating the association of migraine with various acquired or inheritable thrombophilic states, including those related to elevated estrogen levels, endothelial activation and dysfunction, antiphospholipid antibodies (aPL), deficiency of coagulation inhibitors, and presence of certain genetic polymorphisms.
Findings:
Although definitive studies are lacking, a preponderance of available evidence links migraine, and especially aura, to increased levels of estradiol (eg, oral contraceptive pill [OCP] use, pregnancy), thrombo- and erythrocytosis, von Willebrand factor (vWF) antigen, fibrinogen, tissue plasminogen activator (tPA) antigen, and endothelial microparticles. Studies of a link to migraine are conflicting for aPL, homocysteine, Protein S, and the methylenetetrahydrofolate reductase (MTHFR) C677T polymorphism. No association with migraine was found in meta-analyses of Factor V Leiden, and of prothrombin gene mutation. Within a large, young ischemic stroke sample, migraine with aura was associated with a thrombophilic state and with patent foramen ovale (PFO). In the non-stroke population, meta-analyses show an association of PFO and migraine with aura (MA), but two population-based studies do not support the link.
Recommendations:
For persons with MA and (1) a personal history or family history of thrombosis, or (2) MRI evidence of micro-vascular ischemia or of stroke, an evaluation for hypercoagulability is warranted. In cases of MA alone, consider screening for markers of endothelial activation (eg, vWF, high sensitivity c-reactive protein [hs CRP], and fibrinogen). Rigorous management of other stroke risk factors is paramount, but efficacy of anti-thrombotic agents in the treatment of migraine is unproven. Closure of PFO is not routinely recommended based on negative randomized trials.
Insights
Migraine with aura may increase ischemic stroke risk due to hypercoagulability, not atherosclerosis. Evaluation for thrombophilia is recommended for those with a history of thrombosis or stroke indicators.
Area of Science:
- Neurology
- Hematology
- Vascular Medicine
Background:
- Migraine with aura is linked to increased ischemic stroke risk, independent of atherosclerosis.
- Hypercoagulability is a potential mechanism connecting migraine with aura to stroke.
- Cortical spreading depression theory suggests micro-emboli trigger aura or transient ischemic attacks.
Purpose of the Study:
- To review literature on the association between migraine and thrombophilic states.
- To investigate links with acquired/inheritable conditions, estrogen levels, endothelial dysfunction, and genetic factors.
Main Methods:
- Literature review and meta-analysis of studies on migraine and thrombophilia.
- Analysis of associations with specific thrombotic markers and genetic polymorphisms.
- Examination of patent foramen ovale (PFO) in relation to migraine and stroke.
Main Results:
- Evidence links migraine, especially with aura, to elevated estradiol, thrombo- and erythrocytosis, von Willebrand factor (vWF), fibrinogen, tissue plasminogen activator (tPA), and endothelial microparticles.
- Conflicting results exist for antiphospholipid antibodies (aPL), homocysteine, Protein S, and MTHFR C677T polymorphism.
- Migraine with aura is associated with thrombophilia and PFO in young stroke patients; PFO association with migraine with aura is supported by meta-analyses but not all population studies.
Conclusions:
- Hypercoagulability evaluation is warranted for migraine with aura patients with thrombosis history or stroke indicators.
- Screening for endothelial activation markers may be considered for migraine with aura alone.
- Management of stroke risk factors is crucial; anti-thrombotic efficacy in migraine is unproven, and PFO closure is not routinely recommended.


Related Concept Videos
 01:30
Anticoagulant Drugs: Low-Molecular-Weight Heparins
 01:24
Disorders of Hemostasis
Thromboembolic Disorders
Two factors primarily cause thromboembolic conditions.
 01:20
Extrinsic and Intrinsic Pathways of Hemostasis
The Extrinsic Pathway
The extrinsic pathway of coagulation is typically initiated by tissue damage that exposes blood to tissue factor (TF), a protein released by the damaged tissue cells outside the blood vessels—this interaction with TF triggers biochemical reactions involving specific clotting factors. The key player here is Factor VII, which...
 01:29
Pharmacogenetic Phenotypes: Alterations in Pharmacokinetics, Drug Targets and Biologic Milieu
 01:30
Venous Thrombosis I: Introduction
 01:18
Anticoagulant Drugs: Vitamin K Antagonists and Direct Oral Anticoagulants
Warfarin, a prominent vitamin K antagonist family member, exerts its effect by inhibiting the enzyme VKORC1 (vitamin K epoxide reductase complex 1). By hindering this enzyme, warfarin...