Related Experiment Video
Updated: Mar 7, 2026
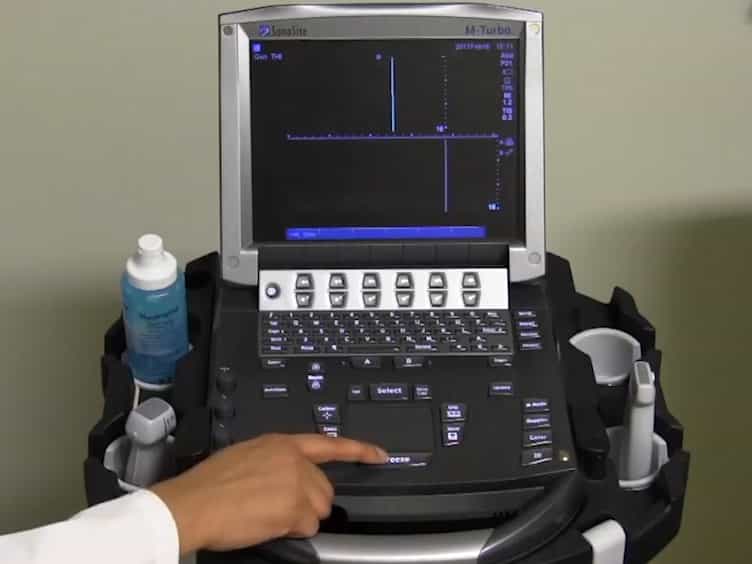

Bedside Ultrasound for Guiding Fluid Removal in Patients with Pulmonary Edema: The Reverse-FALLS Protocol
Published on: July 28, 2018
Targeting urine output and 30-day mortality in goal-directed therapy: a systematic review with meta-analysis and
Esther N van der Zee1, Mohamud Egal2,3, Diederik Gommers1
1Department of Intensive Care, Erasmus MC, University Medical Center Rotterdam, Rotterdam, The Netherlands.

Background:
Oliguria is associated with a decreased kidney- and organ perfusion, leading to organ damage and increased mortality. While the effects of correcting oliguria on renal outcome have been investigated frequently, whether urine output is a modifiable risk factor for mortality or simply an epiphenomenon remains unclear. We investigated whether targeting urine output, defined as achieving and maintaining urine output above a predefined threshold, in hemodynamic management protocols affects 30-day mortality in perioperative and critical care.
Methods:
We performed a systematic review with a random-effects meta-analyses and meta-regression based on search strategy through MEDLINE, EMBASE and references in relevant articles. We included studies comparing conventional fluid management with goal-directed therapy and reporting whether urine output was used as target or not, and reporting 30-day mortality data in perioperative and critical care.
Results:
We found 36 studies in which goal-directed therapy reduced 30-day mortality (OR 0.825; 95% CI 0.684-0.995; P = 0.045). Targeting urine output within goal-directed therapy increased 30-day mortality (OR 2.66; 95% CI 1.06-6.67; P = 0.037), but not in conventional fluid management (OR 1.77; 95% CI 0.59-5.34; P = 0.305). After adjusting for operative setting, hemodynamic monitoring device, underlying etiology, use of vasoactive medication and year of publication, we found insufficient evidence to associate targeting urine output with a change in 30-day mortality (goal-directed therapy: OR 1.17; 95% CI 0.54-2.56; P = 0.685; conventional fluid management: OR 0.74; 95% CI 0.39-1.38; P = 0.334).
Conclusions:
The principal finding of this meta-analysis is that after adjusting for confounders, there is insufficient evidence to associate targeting urine output with an effect on 30-day mortality. The paucity of direct data illustrates the need for further research on whether permissive oliguria should be a key component of fluid management protocols.
More Related Videos
 10:38
Observational Study Protocol for Repeated Clinical Examination and Critical Care Ultrasonography Within the Simple Intensive Care Studies
Published on: January 16, 2019
 06:59
A Novel Approach for the Administration of Medications and Fluids in Emergency Scenarios and Settings
Published on: November 9, 2016
Related Concept Videos
 01:22
Acute Kidney Injury VI: Nursing Management
 01:20
Acute Kidney Injury V: Interprofessional Care
 01:18
Chronic Kidney Disease IV: Nursing Management
 01:22
Heart Failure Drugs: Diuretics
 01:25
Hemodialysis III: Nursing Management
 01:24
Nephrotic Syndrome III : Nursing Management