Related Experiment Video
Updated: Mar 7, 2026


Automated Segmentation of Cortical Grey Matter from T1-Weighted MRI Images
Published on: January 7, 2019
Evaluation of multimodal segmentation based on 3D T1-, T2- and FLAIR-weighted images - the difficulty of choosing
Tobias Lindig1, Raviteja Kotikalapudi2, Daniel Schweikardt1
1Dept. of Diagnostic and Interventional Neuroradiology, University Hospital Tübingen, Hoppe-Seyler-Str. 3, 72076 Tübingen, Germany.

Abstract:
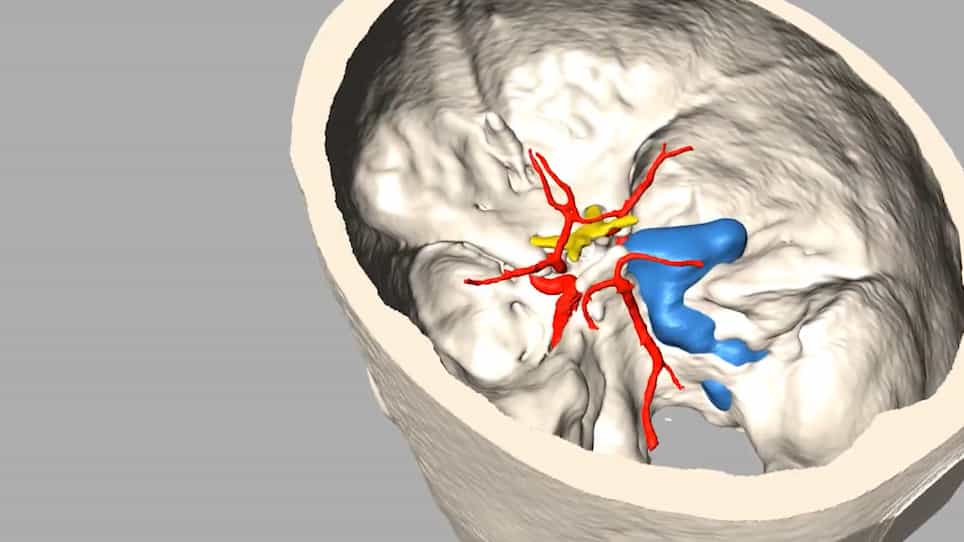
Voxel-based morphometry is still mainly based on T1-weighted MRI scans. Misclassification of vessels and dura mater as gray matter has been previously reported. Goal of the present work was to evaluate the effect of multimodal segmentation methods available in SPM12, and their influence on identification of age related atrophy and lesion detection in epilepsy patients. 3D T1-, T2- and FLAIR-images of 77 healthy adults (mean age 35.8 years, 19-66 years, 45 females), 7 patients with malformation of cortical development (MCD) (mean age 28.1 years,19-40 years, 3 females), and 5 patients with left hippocampal sclerosis (LHS) (mean age 49.0 years, 25-67 years, 3 females) from a 3T scanner were evaluated. Segmentation based on T1-only, T1+T2, T1+FLAIR, T2+FLAIR, and T1+T2+FLAIR were compared in the healthy subjects. Clinical VBM results based on the different segmentation approaches for MCD and for LHS were compared. T1-only segmentation overestimated total intracranial volume by about 80ml compared to the other segmentation methods. This was due to misclassification of dura mater and vessels as GM and CSF. Significant differences were found for several anatomical regions: the occipital lobe, the basal ganglia/thalamus, the pre- and postcentral gyrus, the cerebellum, and the brainstem. None of the segmentation methods yielded completely satisfying results for the basal ganglia/thalamus and the brainstem. The best correlation with age could be found for the multimodal T1+T2+FLAIR segmentation. Highest T-scores for identification of LHS were found for T1+T2 segmentation, while highest T-scores for MCD were dependent on lesion and anatomical location. Multimodal segmentation is superior to T1-only segmentation and reduces the misclassification of dura mater and vessels as GM and CSF. Depending on the anatomical region and the pathology of interest (atrophy, lesion detection, etc.), different combinations of T1, T2 and FLAIR yield optimal results.
Insights
Multimodal MRI segmentation improves accuracy in detecting age-related brain atrophy and epilepsy lesions compared to T1-only methods. Combining T1, T2, and FLAIR scans offers superior results for brain morphometry and disease identification.
Area of Science:
- Neuroimaging
- Radiology
- Medical Image Analysis
Background:
- Voxel-based morphometry (VBM) traditionally relies on T1-weighted MRI scans.
- Previous studies reported misclassification of vessels and dura mater as gray matter in VBM.
- Accurate brain segmentation is crucial for identifying age-related changes and neurological conditions.
Purpose of the Study:
- To evaluate the impact of multimodal segmentation methods in SPM12 on VBM analysis.
- To assess the influence of different segmentation approaches on detecting age-related atrophy.
- To compare the effectiveness of various segmentation techniques for lesion detection in epilepsy patients.
Main Methods:
- Acquired 3D T1-, T2-, and FLAIR-weighted MRI scans from 77 healthy adults and 62 patients (MCD and LHS).
- Compared segmentation results from T1-only, T1+T2, T1+FLAIR, T2+FLAIR, and T1+T2+FLAIR approaches.
- Evaluated VBM results for age-related atrophy and lesion detection in epilepsy cohorts.
Main Results:
- T1-only segmentation overestimated intracranial volume due to misclassification of dura and vessels.
- Significant regional differences in VBM were observed across segmentation methods.
- Multimodal T1+T2+FLAIR segmentation showed the best age correlation; T1+T2 was optimal for LHS detection.
Conclusions:
- Multimodal MRI segmentation significantly outperforms T1-only methods in VBM analysis.
- Combining T1, T2, and FLAIR sequences reduces misclassification errors, enhancing accuracy.
- Optimal segmentation strategy depends on the specific anatomical region and clinical application (atrophy vs. lesion detection).