Related Experiment Video
Updated: Mar 7, 2026


The bm12 Inducible Model of Systemic Lupus Erythematosus SLE in C57BL/6 Mice
Published on: November 1, 2015
[Systemic lupus erythematosus and lymphopenia: Clinical and pathophysiological features]
M Martin1, A Guffroy1, X Argemi2
1Service d'immunologie clinique et de médecine interne, centre national de référence des maladies auto-immunes rares, hôpitaux universitaires de Strasbourg, 67091 Strasbourg, France; CNRS UPR 3572 « immunopathologie, chimie thérapeutique »/équipe « tolérance cellulaire B, auto-immunité », laboratoire d'excellence Medalis, Institute of Molecular and Cellular Biology (IBMC), Strasbourg, France.

Abstract:
Lymphopenia is frequent in systemic lupus erythematosus (SLE) and profound (<500/mm3) in 10% of cases. T lymphocytes, especially CD4+, are more affected than B cells. The pathophysiological mechanisms are complex, involving lymphocytotoxic antibodies, excess of apoptosis, increased susceptibility of T cells to complement mediated cytolysis, as well as lymphopoiesis impairment and lymphocyte sequestration. Lymphopenia in SLE is independent from other cytopenia and immunosuppressive drug regiments, and associated with disease activity, risk of flare and damage scores. Infectious risk is mostly bacterial, and lymphopenia <1 G/L is an independent risk factor for severe bacterial infections occurrence. The T cellular deficiency is associated with less control of viral replication, but severe and symptomatic infections are scarce. Although exceptional in SLE, pneumocystis is more severe than in HIV+ patients, and risk of progressive multifocal leukoencephalopathy seems increased compared to other rheumatic diseases. To date, there are no specific recommendations for management of SLE with lymphopenia. Infectious prophylaxis should remain exceptional and discussed on a case by case basis. Further studies are needed to assess the clinical characteristics and outcomes of patients with SLE and profound lymphopenia (<500/mm3), which are probably a subset of SLE with primary immunodeficiency and require specific management.

Related Concept Videos
 01:28
Functions of the Lymphatic and Immune System
The primary lymphoid organs, including the bone marrow and the thymus, serve as the maturation sites for lymphocytes. Secondary lymphoid organs, like the mucosa-associated lymphoid tissue, activate these lymphocytes and serve as...
 01:18
Lymphoid Cells and Tissues
Lymphoid cells consist of various types of immune system cells. These include B and T lymphocytes, which are responsible for producing antibodies and killing infected cells, respectively. Dendritic cells act as messengers between the innate and adaptive...
 01:27
Disorders of Leukocytes
Leukopenia may result from bone marrow disorders, autoimmune diseases, and infectious diseases. For example, conditions such as multiple myeloma and aplastic anemia can impair the bone marrow's ability to produce adequate leukocytes. Similarly, autoimmune diseases like lupus and viral infections such as HIV can prompt the immune...
 01:23
Introduction to Lymphatic and Immune System
The immune responses can be categorized into two types: innate and adaptive. Innate immunity comprises nonspecific defenses we are born...
 01:24
Nephrotic Syndrome I : Introduction
 01:15
Secondary Lymphoid Organs
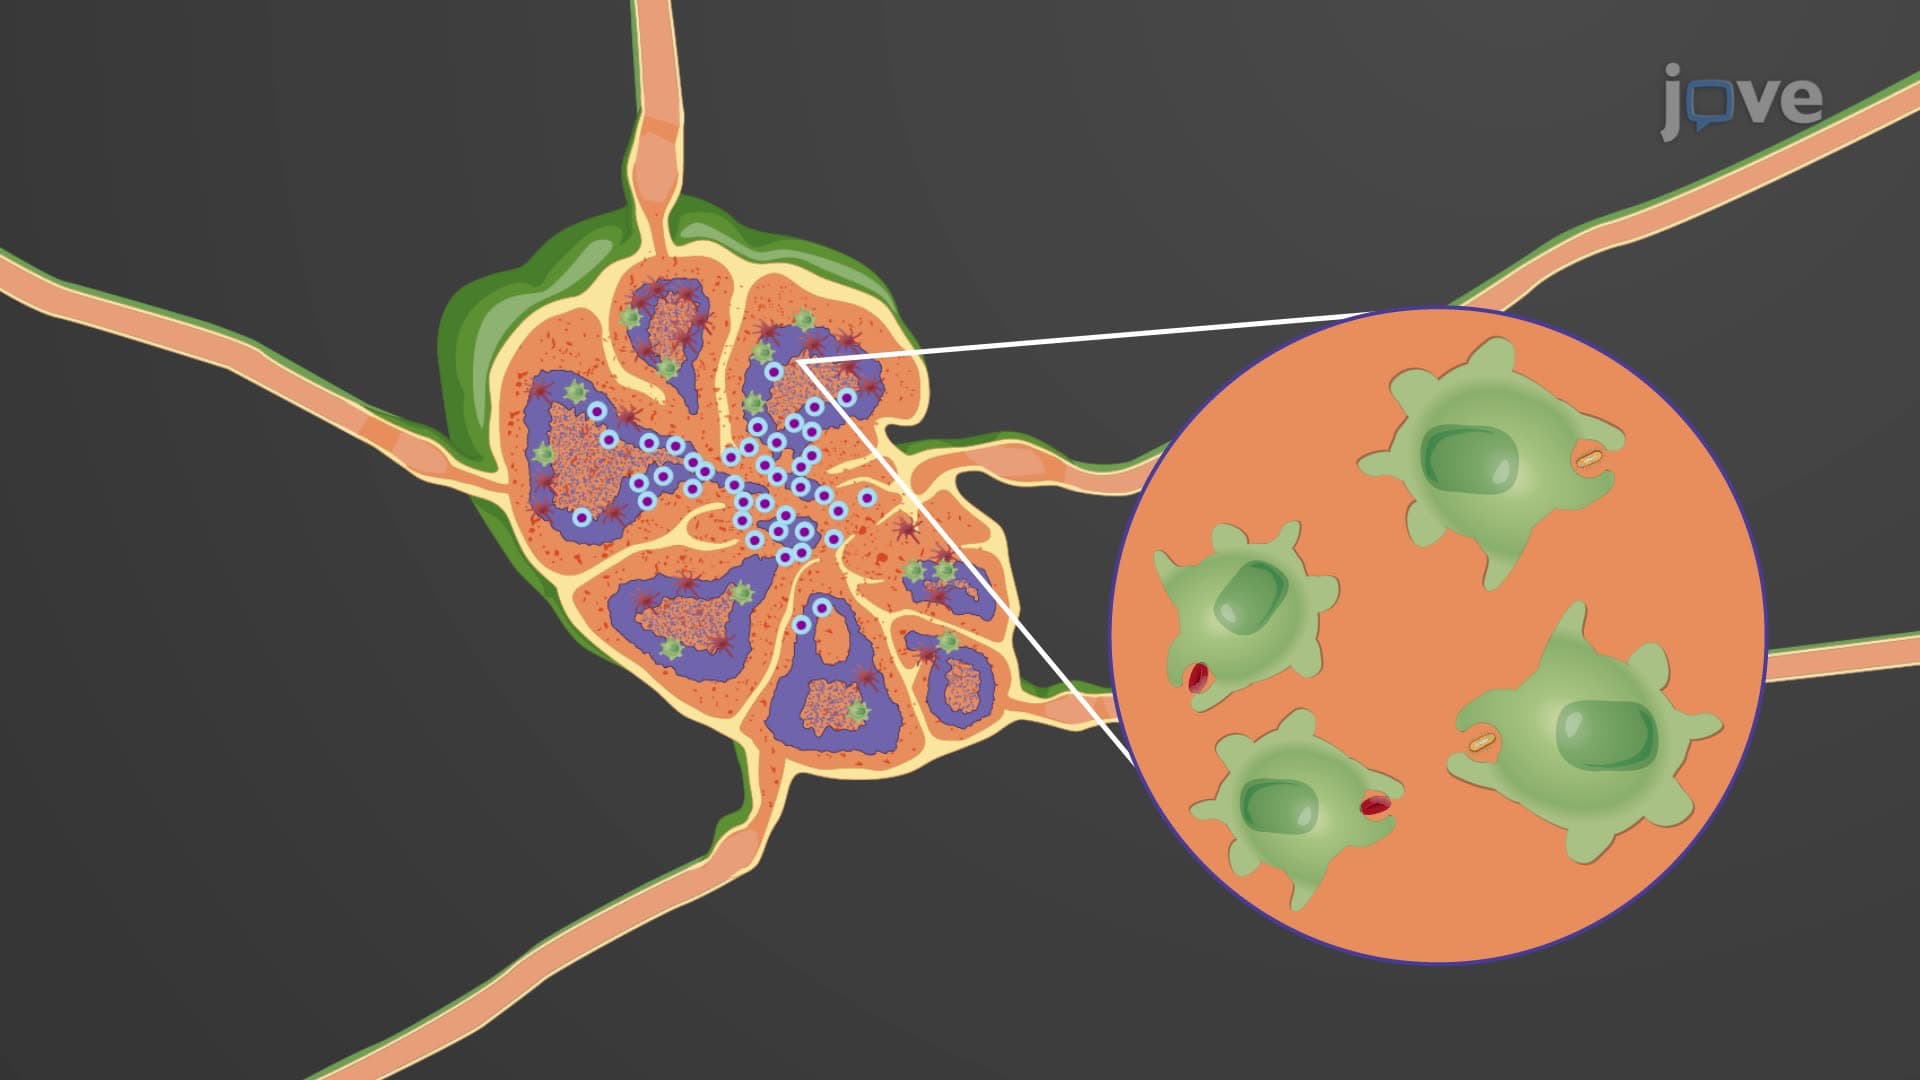
The spleen is a vital organ in the lymphatic system, nestled in the upper left side of the abdomen. It is composed of two primary regions: the red pulp and the white pulp, each having distinct functions. The red pulp performs a significant role in blood filtration. It efficiently purges the blood of old or damaged red blood cells and...