Related Experiment Video
Updated: Mar 7, 2026


Quantifying Antibody-Dependent Cellular Cytotoxicity in a Tumor Spheroid Model: Application for Drug Discovery
Published on: April 26, 2024
Outcomes and Drug Costs of Sunitinib Regimens for Metastatic Renal Cell Carcinoma: A Provincial Population-Based
Aleksi Suo1, Urooj Iqbal2, June Lim3
1Department of Medicine, University of Saskatchewan, Saskatoon, SK, Canada.

Background:
Conventional sunitinib dosing in metastatic renal cell carcinoma (mRCC) administers 50 mg daily on a 4 weeks on/2 weeks off (4/2) schedule. Not all patients tolerate this regimen and many undergo modifications to schedule, dose, or both.
Material And Methods:
All patients with mRCC treated with sunitinib by the Saskatchewan Cancer Agency between January 1, 2006, and January 1, 2013, were included. Regimens were categorized as standard intermittent dosing (SID), modified intermittent schedule (MIS), modified intermittent dosing (MID), combination of modified schedule and dosing (MSD), or continuous dosing (CD). The primary objective was to compare overall survival (OS) between regimens. Secondary outcomes included progression-free survival (PFS), discontinuation due to adverse effects (AE), and medication cost.
Results:
Among 161 patients, 18.0%, 51.6%, and 30.4% had favorable, intermediate, and poor Heng risk prognoses, respectively. A total of 140 (87.0%) received sunitinib as first-line therapy. MID was associated with longer OS compared with SID (estimated median 28.4 vs. 11.2 months). PFS was longer for MID, MSD, and CD compared with SID (estimated median 12.0, 9.0, and 8.0 months vs. 3.0 months, respectively). Adjustment for potential confounders did not negate these associations. SID also had higher average monthly drug costs than MIS, MID, and MSD. Overall discontinuation rate due to AE was high (24%).
Conclusion:
An adjusted-dose sunitinib regimen is associated with improved OS and PFS over SID, with lower costs. The development of toxicities requiring dose reductions serves as a predictive biomarker for better outcomes.
More Related Videos
 06:38
A Syngeneic Mouse Model of Metastatic Renal Cell Carcinoma for Quantitative and Longitudinal Assessment of Preclinical Therapies
Published on: April 12, 2017
 10:27
Testing Targeted Therapies in Cancer using Structural DNA Alteration Analysis and Patient-Derived Xenografts
Published on: July 25, 2020
Related Concept Videos
 01:15
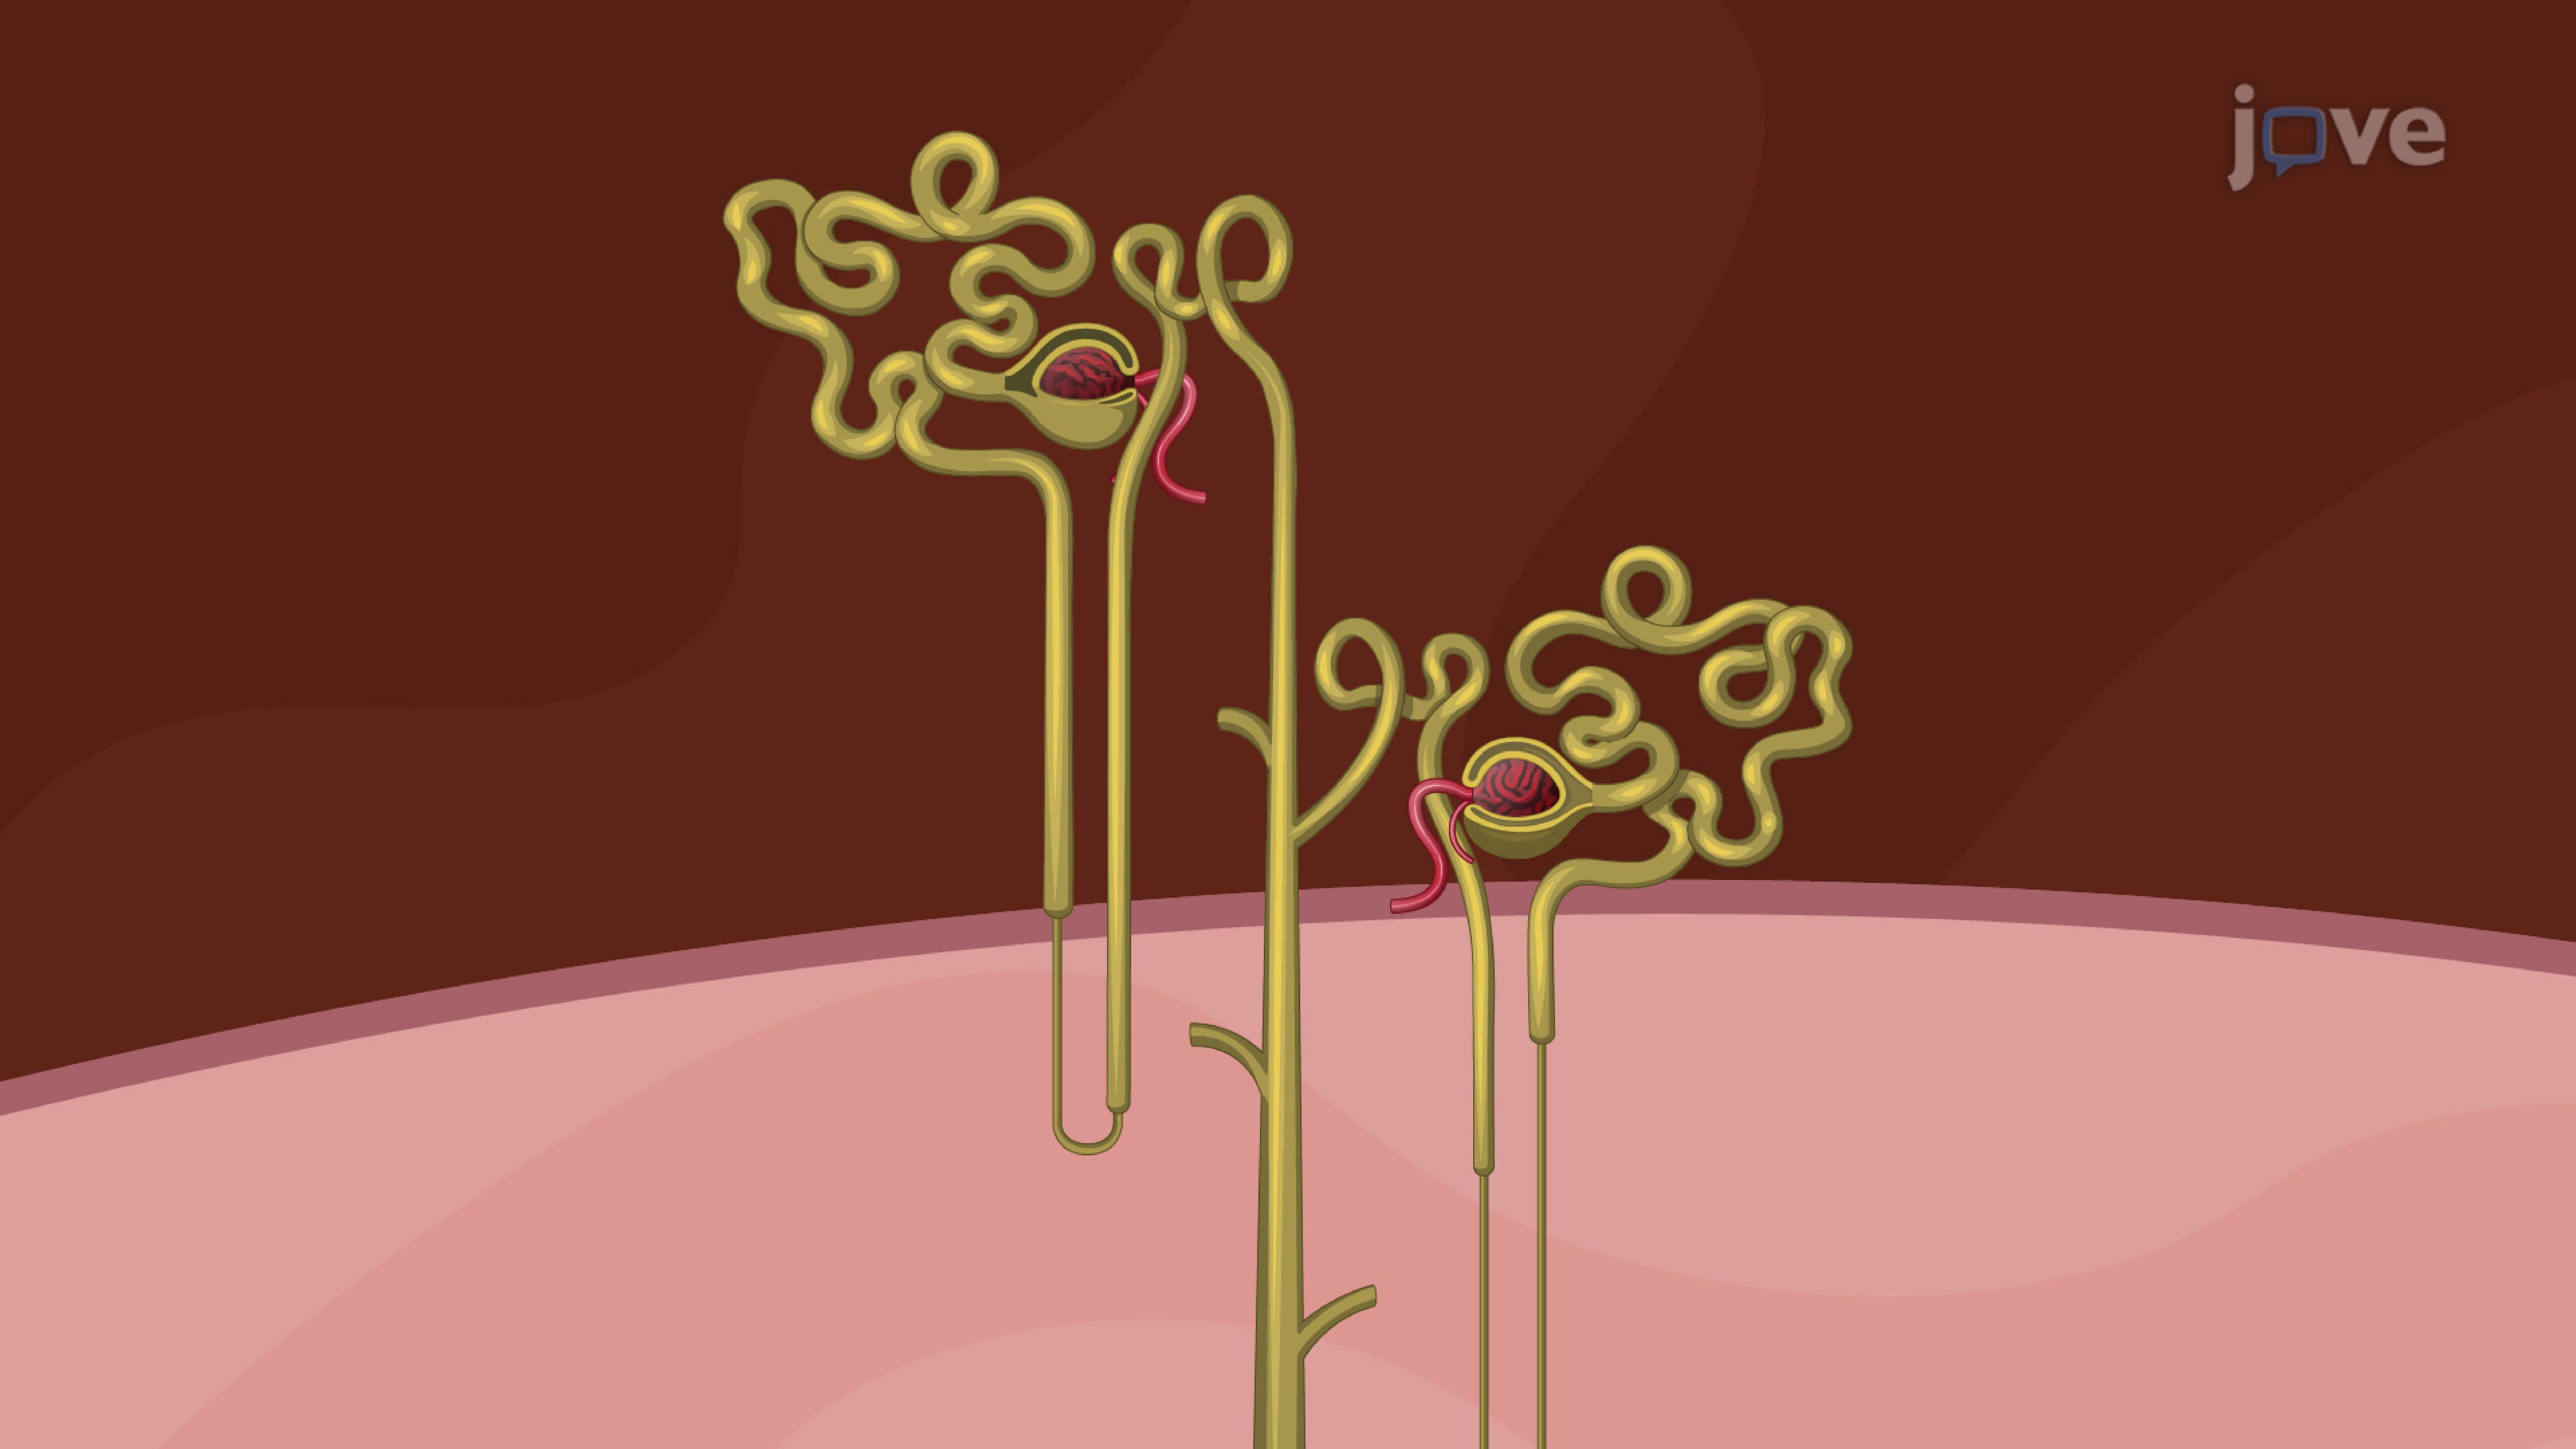
Renal Drug Excretion: Overview
A nephron consists of two primary structures: the renal corpuscle and the renal tubule. The renal corpuscle contains the glomerulus, a network of capillaries where the first step of renal excretion, glomerular filtration, occurs. Blood pressure forces water, ions, and small molecules...
 01:06
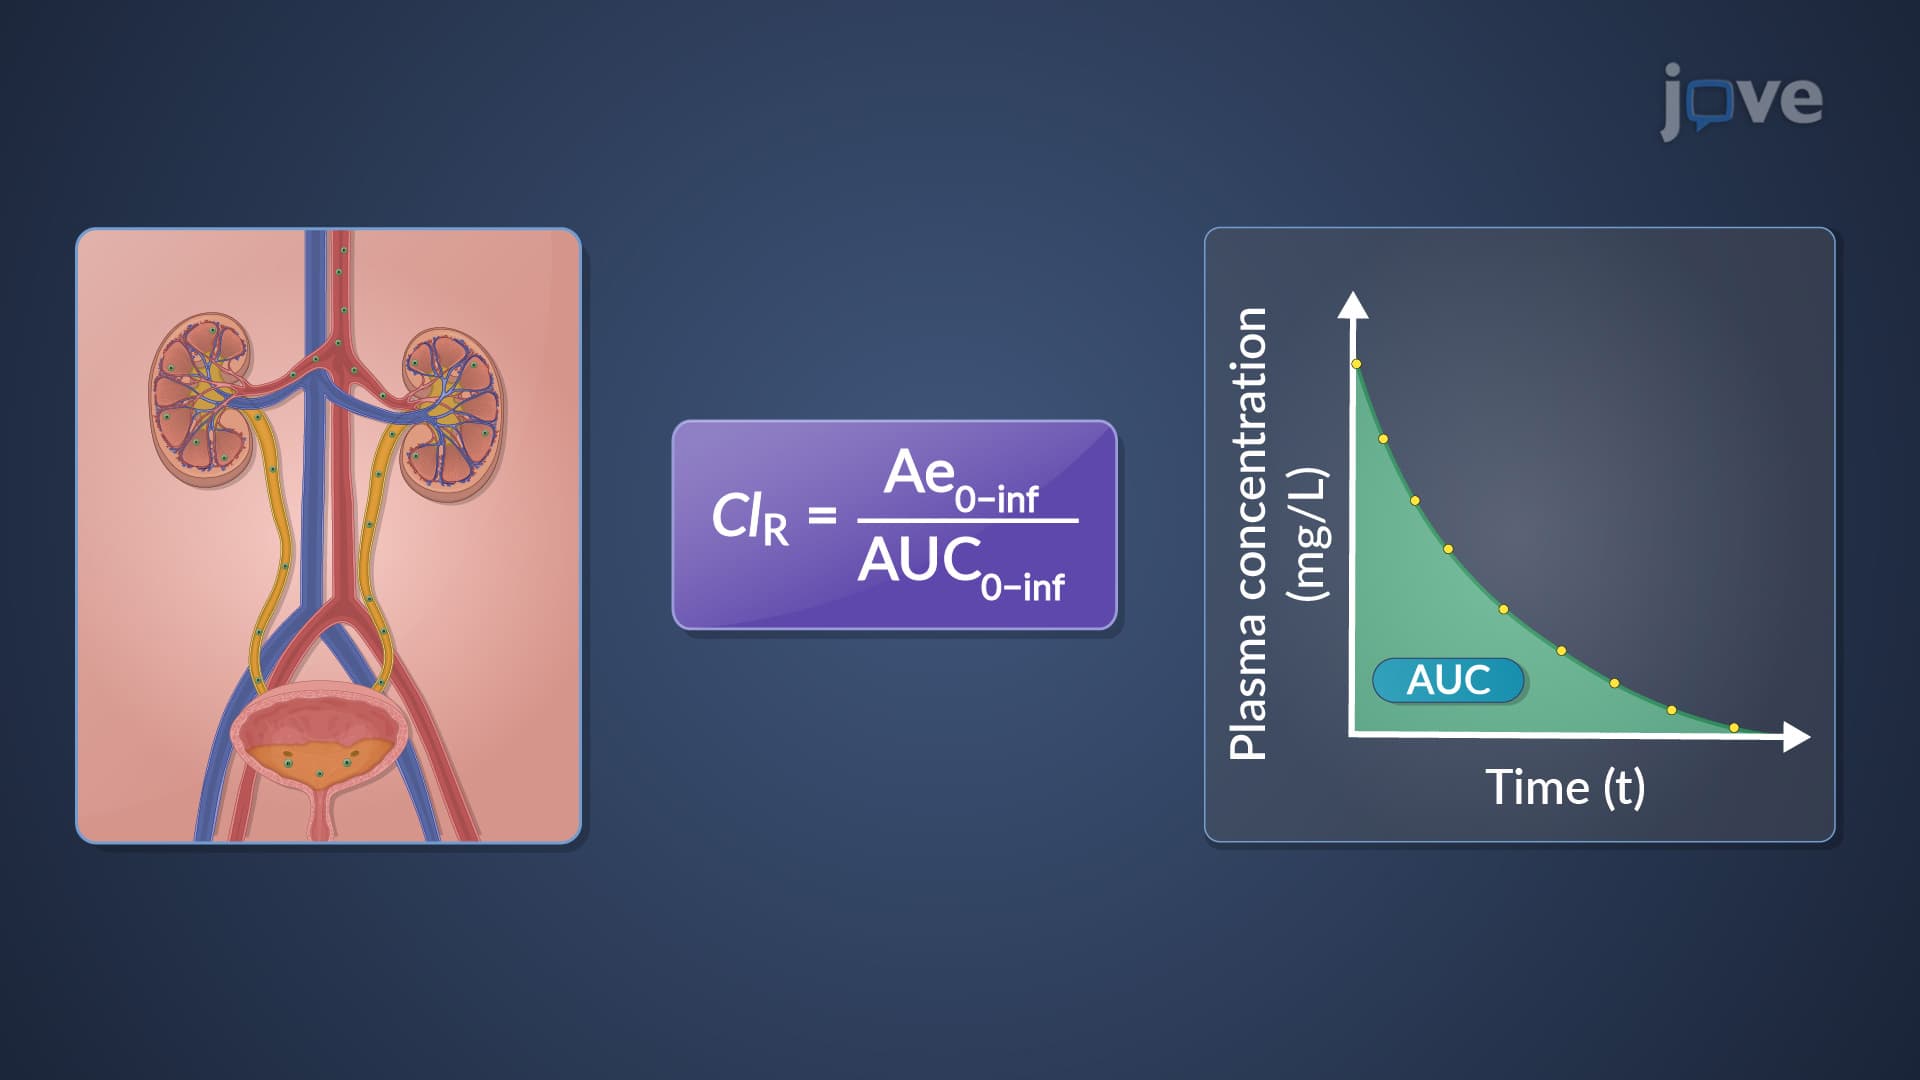
Renal Drug Clearance: Overview
Renal clearance can be calculated using different methods. One approach is to divide the urinary drug excretion rate by the plasma drug concentration. This method directly measures renal clearance, indicating the kidneys' efficiency in...
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:21
Cancer Survival Analysis
 01:28
Drug Dosing in Renal Diseases: Estimation of Glomerular Filtration Rate Based on Serum Creatinine Concentration