Related Experiment Video
Updated: Mar 7, 2026


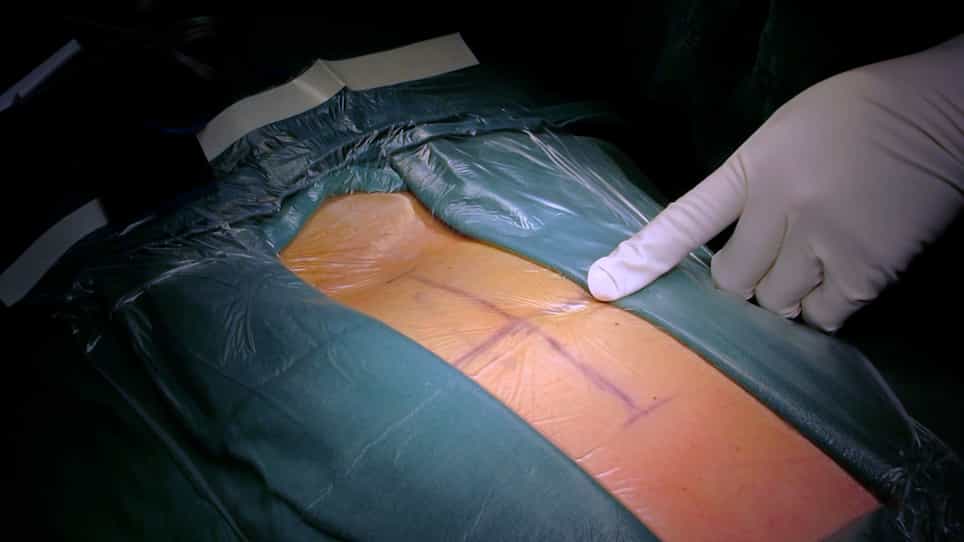
Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
Early results of thoraco lumbar burst fracture treatment using selective corpectomy and rectangular cage
Bowei Liang1, Guofeng Huang1, Luobing Ding1
1Department of Orthopedics, The 175 Hospital of PLA, Affiliated Dongnan Hospital of Xiamen University, Zhangzhou, Fujian 363000, China.

Background:
Subsidence and late fusion are commonly observed in anterior subtotal corpectomy and reconstruction for treating thoracolumbar burst fractures. The subsidence rate of this surgical method was reported from 19.6% to 75% in the literatures, which would cause treatment failure. Thus, an improvement of anterior surgery technique should be studied to reduce these complications.
Materials And Methods:
130 patients of thoracolumbar burst fractures treated by minimal corpectomy, decompression and U cage, between January 2009 and December 2010 were included in this study. The hospital Ethical Committee approved the protocols. The American Spinal Injury Association (ASIA) scale, visual analog scales, and Oswestry Disability Index (ODI) scores were used for clinical evaluation. The local kyphosis angle, vertebral height (one level above the fractured vertebral to one level below), canal stenosis, and fusion status were used to assess radiological outcome. All complications and demographic data such as number of male/female patients, average age, mode of trauma, burst level involved, mean surgery time and blood lost were reported.
Results:
120 patients were followed up for 24 months. Most patients had improvement of at least 1 ASIA grade, and all experienced pain reduction. The mean ODI score steadily decreased after the surgery (P < 0.01). Approximately, 83.3% of patients achieved solid fusion at 3 months and reached 98.3% at 6 months. The kyphosis angle and radiographic height were corrected significantly after the surgery and with a nonsignificant loss of correction at 24 months (P > 0.05). The average canal stenosis index was increased from 39% to 99% after surgery. No cage subsidence or implant failure was observed.
Conclusions:
The clinical outcomes described here suggest that the selective corpectomy and rectangular cage reconstruction can effectively promote solid fusion and eliminate complications related to subsidence or implant failure.
Related Concept Videos
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...