Related Experiment Video
Updated: Mar 7, 2026


Assessment of Vascular Function in Patients With Chronic Kidney Disease
Published on: June 16, 2014
Carotid systolic flow time with passive leg raise correlates with fluid status changes in patients undergoing
Pavel Antiperovitch1, Eduard Iliescu2, Barry Chan3
1Queen's University, Department of Medicine, Etherington Hall, Room 3033, 94 Stuart Street, Kingston, Ontario, K7L 3N6.

Abstract:
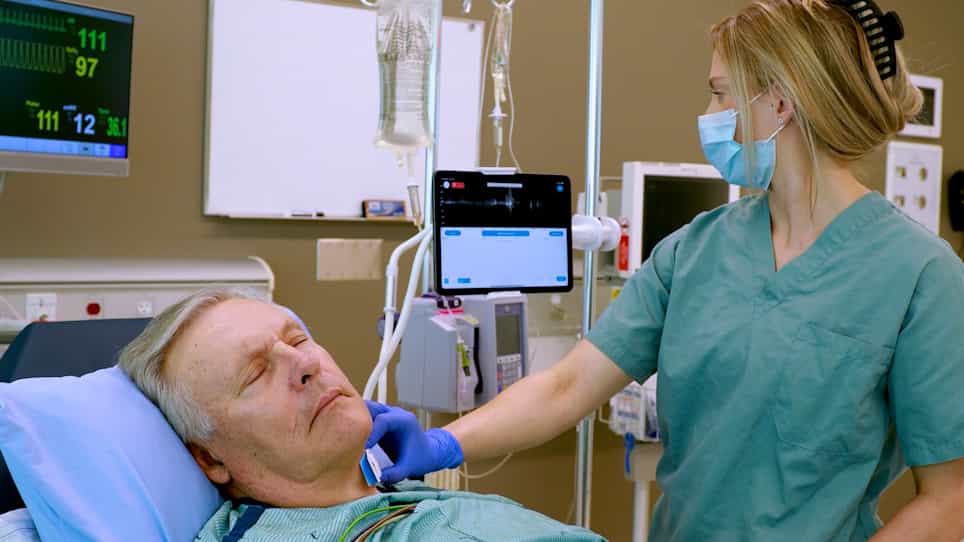
Corrected carotid systolic flow time (CFTc) has been proposed as a measure of volume status in acutely ill patients. This study endeavors to determine whether the change in CFTc with passive leg raise (PLR) maneuver correlates with volume status changes. Dialysis patients at Kingston General Hospital (Kingston, Canada) underwent point-of-care carotid ultrasonography at the beginning and the end of dialysis. With each measurement, 2 values were recorded: the absolute CFTc, and the difference in CFTc before and after the PLR maneuver. A total of 49 measurements were collected during the study period. CFTc changed with PLR by 5±22milliseconds (2.0%) pre-dialysis and by 40±19milliseconds (13.0%) post-dialysis (P<.0001). Incorporating PLR to the CFTc measurement improved the area under the ROC from 0.64 to 0.91. Particularly, in our sample of patients, a 30milliseconds increase in CFTc with PLR predicted the post-dialysis volume state (LR+=11) whereas an increase of less than 20milliseconds argued against it (LR-=0.079). The assessment of CFTc pre- and post-PLR correlates with intravascular volume changes in patients undergoing dialysis. Alternative to the currently available bedside modalities, this technique is non-invasive, objective, simple to perform at the bedside, and reversible with respect to volume challenge.
Related Concept Videos
 01:24
Hemodialysis II: Procedure and Complications
 01:25
Hemodialysis III: Nursing Management
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:19
Urodynamic Studies: Uroflowmetry
 01:28
Special considerations while measuring blood pressure
Monitoring Both Arms:
Monitoring BP in both arms during the initial assessment is advisable, as the systolic value may differ by five to ten mm Hg between arms. For subsequent BP assessments, use the arm with the higher reading.