Related Experiment Video
Updated: Mar 7, 2026
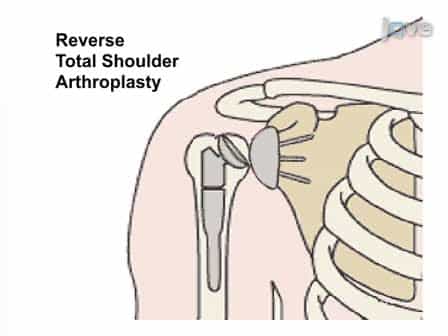

Reverse Total Shoulder Arthroplasty
Published on: July 5, 2011
Preoperative planning for accurate glenoid component positioning in reverse shoulder arthroplasty
J Berhouet1, L V Gulotta1, D M Dines2
1Hospital for Special Surgery, Department of Sports Medicine and Shoulder, 535 E 70th St., New York, NY 10021, USA; Hospital for Special Surgery, The Leon Root, Motion Analysis Laboratory, 510 E 73rd St., New York, NY 10021, USA.

Background:
Glenoid component positioning in reverse shoulder arthroplasty (RSA) is challenging. Patient-specific instrumentation (PSI) has been advocated to improve accuracy, and is based on precise preoperative planning. The purpose of this study was to determine the accuracy of glenoid component positioning when only the glenoid surface is visible, compared to when the entire scapula is visible on a 3D virtual model.
Methods:
CT scans of 30 arthritic shoulders were reconstructed in 3D models. Two surgeons then virtually placed a glenosphere component in the model while visualizing only the glenoid surface, in order to simulate typical intraoperative exposure ("blind 3D" surgery). One surgeon then placed the component in an ideal position while visualizing the entire scapula ("visible 3D" surgery). These two positions were then compared, and the accuracy of glenoid component positioning was assessed in terms of correction of native glenoid version and tilt, and avoidance of glenoid vault perforation.
Results:
Mean version and tilt after "blind 3D" surgery were +1.4° (SD 8.8°) and +7.6° (SD 6°), respectively; glenoid vault perforation occurred in 17 specimens. Mean version and tilt after "visible 3D" surgery were +0.3° (SD 0.8°) and +0.1° (SD 0.5°), respectively, with glenoid vault perforation in 6 cases. "Visible 3D" surgery provided significantly better accuracy than "blind 3D" surgery (P<0.05).
Conclusion:
When the entire scapula is used as reference, accuracy is improved and glenoid vault perforation is less frequent. This type of visualization is only possible with pre-operative 3D CT planning, and may be augmented by PSI.
Level Of Evidence:
Basic science study. Level III.
More Related Videos
 09:31
Individualized Stem-positioning in Calcar-guided Short-stem Total Hip Arthroplasty
Published on: February 27, 2018
 09:51
The Transition to an Anterior-Based Muscle Sparing Approach Improves Early Postoperative Function but is Associated with a Learning Curve
Published on: September 7, 2022