Related Experiment Video For Lung adenocarcinoma
Updated: Mar 6, 2026

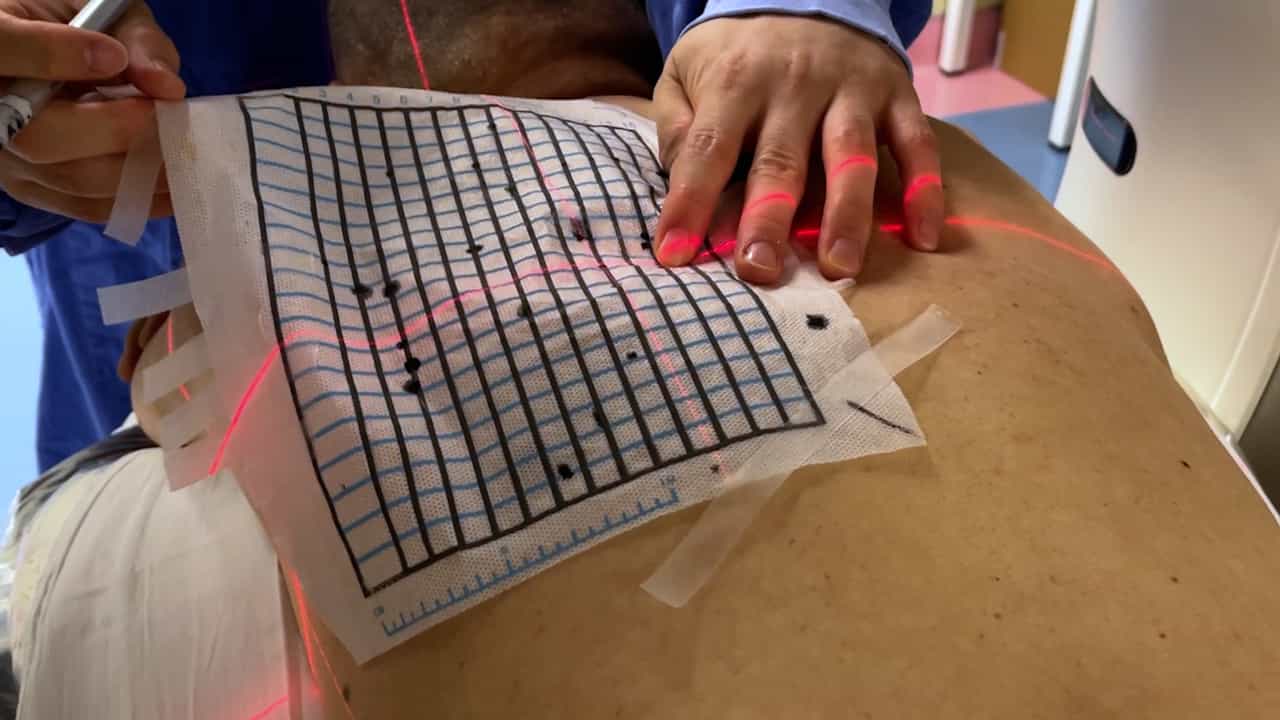
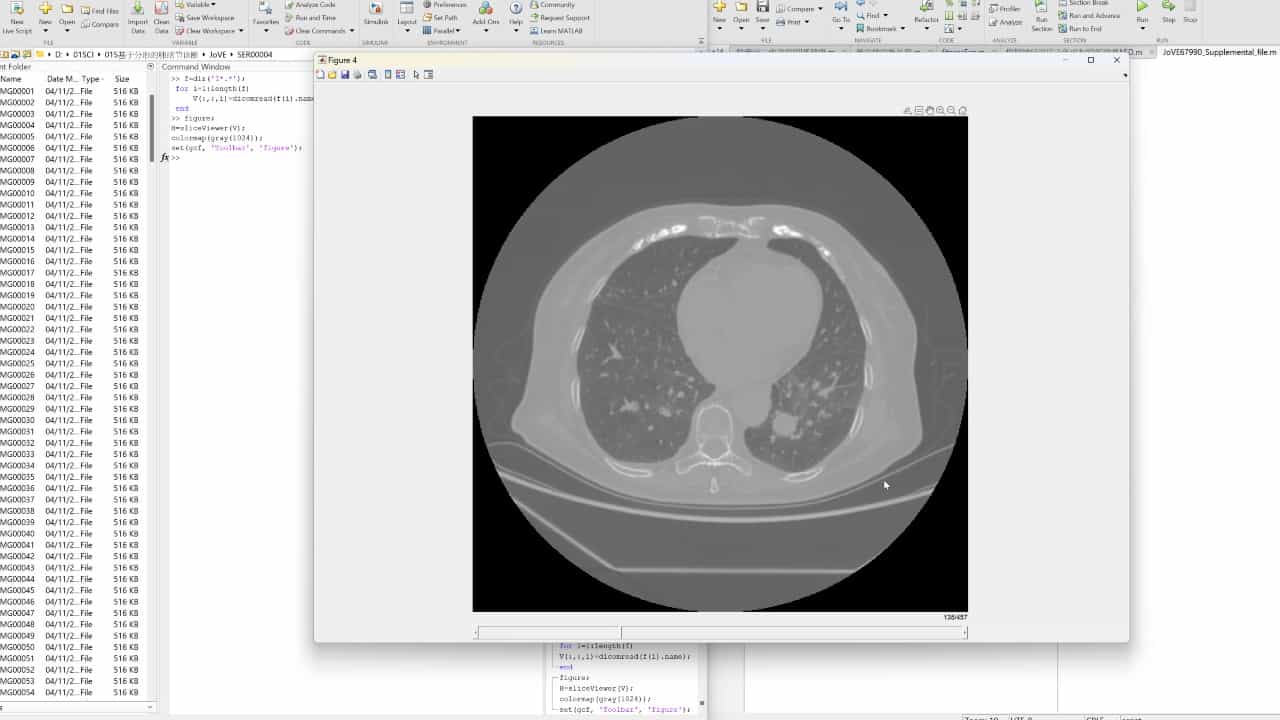
Author Spotlight: A 3D Digital Model for the Diagnosis and Treatment of Pulmonary Nodules
Published on: May 19, 2023
Size Measurement and T-staging of Lung Adenocarcinomas Manifesting as Solid Nodules ≤30 mm on CT: Radiology-Pathology
Benedikt H Heidinger1, Kevin R Anderson2, Eoin M Moriarty3
1Radiology, Beth Israel Deaconess Medical Center, Harvard Medical School, 330 Brookline Ave, Boston, MA; Department of Biomedical Imaging and Image-guided Therapy, Vienna General Hospital, Medical University of Vienna, Währinger Gürtel 18-20, 1090 Vienna, Austria.

Rationale And Objectives:
This study aimed to compare long-axis diameter to average computed tomography (CT) diameter measurements of lung adenocarcinomas manifesting as solid lung nodules ≤30 mm on CT, as referenced to pathologic measurements, and to determine the impact of the two CT measurement approaches on tumor (T)-staging of nodules.
Materials And Methods:
This institutional review board-approved study included all 274 radiologic solid adenocarcinomas resected at our institution over 10 years. Two observers measured long- and short-axis diameters on pre-resection chest CT in lung and mediastinal windows. T-stages were determined. CT measurements and T-stages were compared to pathology measurements and T-stages using Wilcoxon signed rank test and McNemar test. Inter- and intraobserver variability was determined with intraclass correlation coefficients (ICC) and Bland-Altman plots.
Results:
For lung and mediastinal windows, nodule size was significantly larger using long-axis diameter rather than average diameter (16.93 vs. 14.92 mm, P <.001; and 14.02 vs. 12.17 mm, P <.001, respectively). The correlation of CT with pathologic measurements was stronger with long-axis than with average diameter (ICC 0.808 vs. 0.730; and 0.731 vs. 0.621, respectively). Lung window measurements correlated stronger with pathology than mediastinal window measurements. CT T-stages differed from pathology T-stages in more than 20% of nodules (P <.001). Inter- and intraobserver variability was small with long-axis and average diameter (ICC range 0.96-0.991, and 0.970-0.993, respectively), but long-axis diameter showed wider scatter on Bland-Altman plots.
Conclusions:
Long-axis CT diameter is preferable for T-staging because it better reflects the pathology T-stage. Average CT diameter might be used for longitudinal nodule follow-up because it shows less measurement variability and is more conservative in size assessment.