Related Experiment Video
Updated: Mar 6, 2026


Digital Home-Monitoring of Patients after Kidney Transplantation: The MACCS Platform
Published on: April 12, 2021
Filtration Markers, Cardiovascular Disease, Mortality, and Kidney Outcomes in Stable Kidney Transplant Recipients:
M C Foster1, D E Weiner1, A G Bostom2
1Division of Nephrology, Tufts Medical Center, Boston, MA.

Insights
Cystatin C and beta-2-microglobulin (B2M) are better predictors of adverse outcomes like cardiovascular events, mortality, and kidney failure in kidney transplant recipients than creatinine. These filtration markers offer stronger prognostic value for transplant patient health.
Area of Science:
- Nephrology
- Transplantation Medicine
- Cardiovascular Research
Background:
- Cystatin C and beta-2-microglobulin (B2M) are established filtration markers linked to adverse outcomes in general populations.
- Their predictive power may exceed that of creatinine, particularly in specific patient cohorts.
- Kidney transplant recipients represent a population at high risk for cardiovascular events, mortality, and graft failure.
Purpose of the Study:
- To evaluate the association of estimated glomerular filtration rate (eGFR) derived from cystatin C (eGFRcys) and B2M (eGFRB2M) with cardiovascular outcomes, mortality, and kidney failure.
- To compare the prognostic utility of eGFRcys and eGFRB2M against traditional creatinine-based eGFR (eGFRcr) in stable kidney transplant recipients.
- To determine if these associations persist after adjusting for baseline eGFRcr.
Main Methods:
- A case-cohort study design was employed within the Folic Acid for Vascular Outcome Reduction in Transplantation (FAVORIT) Trial.
- A random subcohort (N=508) was selected and enriched for cardiovascular events, mortality, and kidney failure.
- Multivariable regression models were used to assess hazard ratios for adverse outcomes based on eGFR categories (<30 vs. 60+ mL/min/1.73m2).
Main Results:
- Lower eGFRcys (<30) was associated with significantly increased risk for cardiovascular events (HR 2.02), mortality (HR 3.92), and kidney failure (HR 9.49) compared to eGFRcys 60+.
- Similarly, lower eGFRB2M (<30) showed strong associations with cardiovascular events (HR 2.56), mortality (HR 4.09), and kidney failure (HR 15.53).
- These associations remained significant even after adjusting for baseline eGFRcr, indicating independent prognostic value.
Conclusions:
- Cystatin C and B2M-based eGFR are strongly associated with adverse cardiovascular outcomes, mortality, and kidney failure in stable kidney transplant recipients.
- These markers demonstrate superior or complementary prognostic capability compared to creatinine-based eGFR in this high-risk population.
- Incorporating cystatin C and B2M into risk assessment may improve management strategies for kidney transplant recipients.
Abstract:
Cystatin C and beta-2-microglobulin (B2M) are filtration markers associated with adverse outcomes in nontransplant populations, sometimes with stronger associations than for creatinine. We evaluated associations of estimated glomerular filtration rate from cystatin C (eGFRcys ), B2M (eGFRB2M ), and creatinine (eGFRcr ) with cardiovascular outcomes, mortality, and kidney failure in stable kidney transplant recipients using a case-cohort study nested within the Folic Acid for Vascular Outcome Reduction in Transplantation (FAVORIT) Trial. A random subcohort was selected (N = 508; mean age 51.6 years, median transplant vintage 4 years, 38% women, 23.6% nonwhite race) with enrichment for cardiovascular events (N = 306; 54 within the subcohort), mortality (N = 208; 68 within the subcohort), and kidney failure (N = 208; 52 within the subcohort). Mean eGFRcr , eGFRcys , and eGFRB2M were 46.0, 43.8, and 48.8 mL/min/1.73m2 , respectively. After multivariable adjustment, hazard ratios for eGFRcys and eGFRB2M <30 versus 60+ were 2.02 (95% confidence interval [CI] 1.09-3.76; p = 0.03) and 2.56 (1.35-4.88; p = 0.004) for cardiovascular events; 3.92 (2.11-7.31) and 4.09 (2.21-7.54; both p < 0.001) for mortality; and 9.49 (4.28-21.00) and 15.53 (6.99-34.51; both p < 0.001) for kidney failure. Associations persisted with additional adjustment for baseline eGFRcr . We conclude that cystatin C and B2M are strongly associated with cardiovascular events, mortality, and kidney failure in stable kidney transplant recipients.

Related Concept Videos
 01:28
Kidney Transplant I: Introduction
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
 01:16
Kidney Transplant III: Nursing Management
 01:25
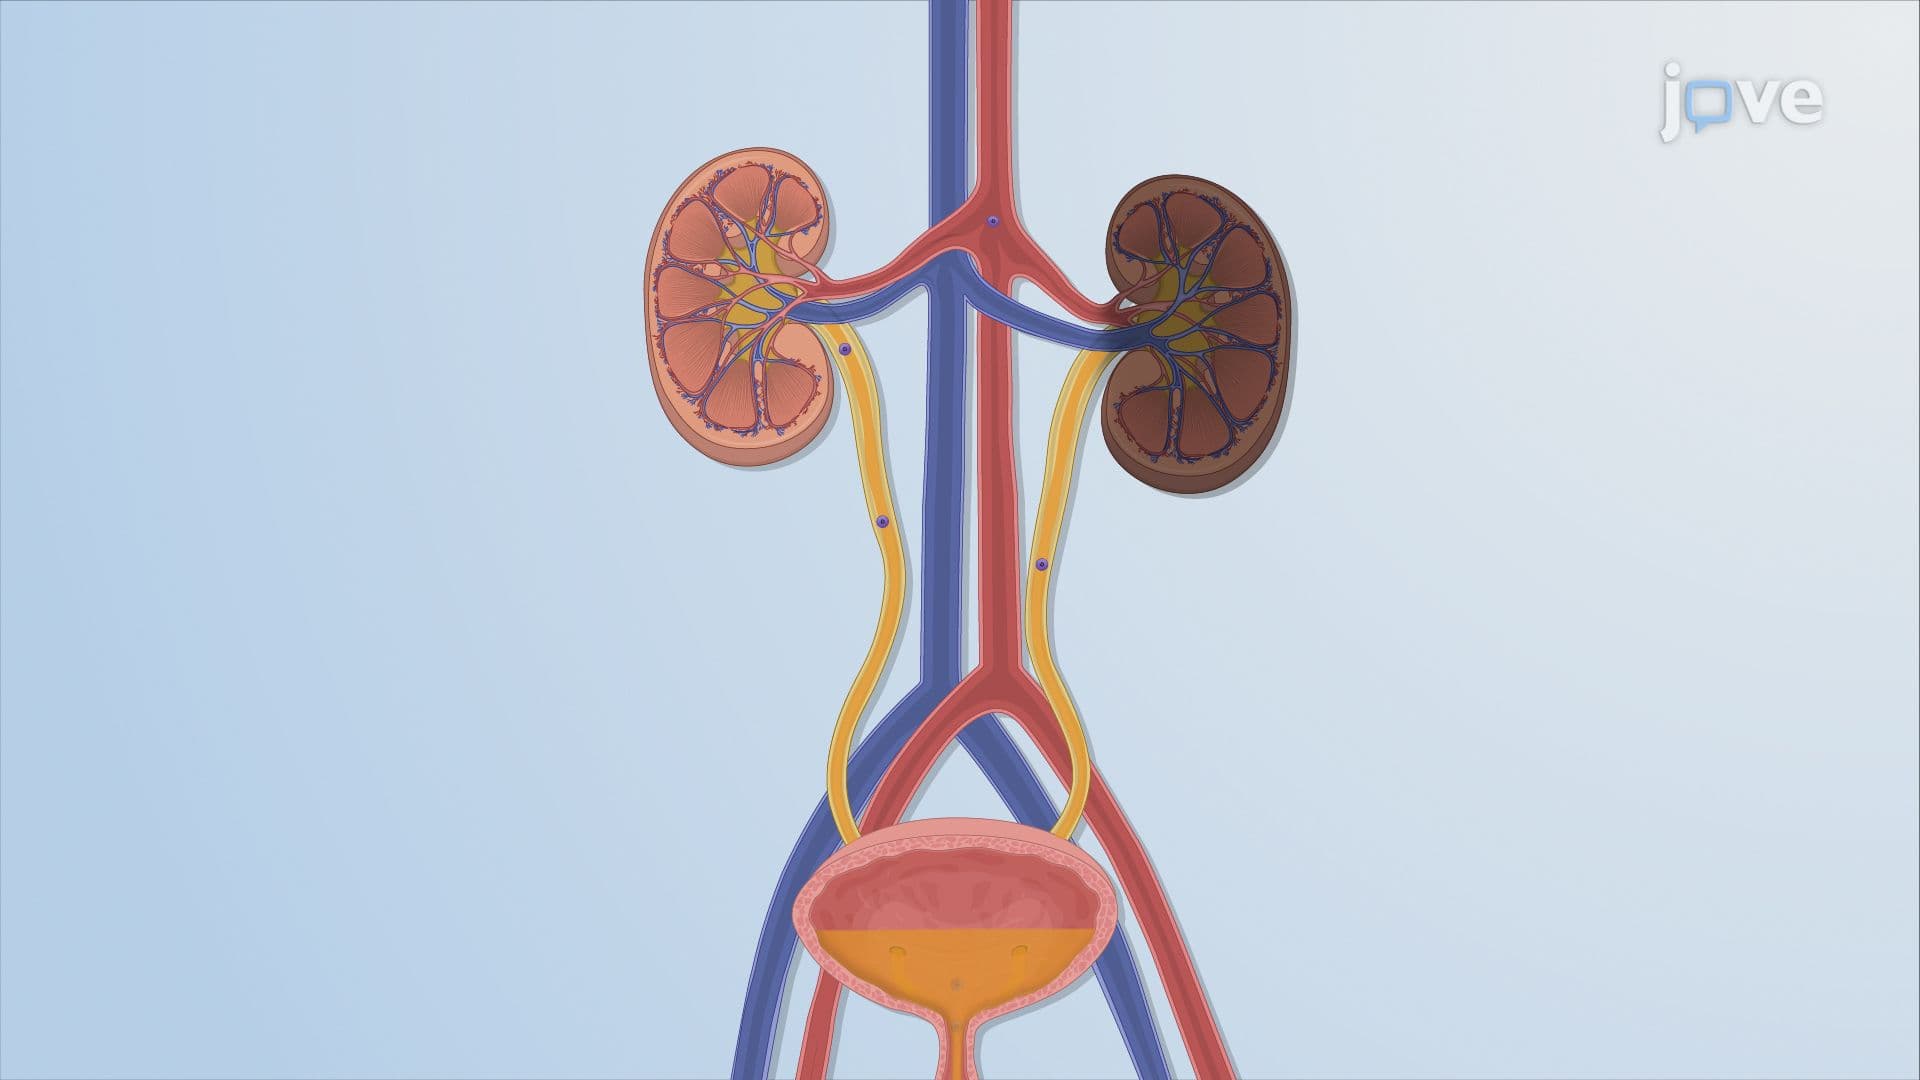
Drug Dosing in Renal Diseases: Measurement of Glomerular Filtration Rate
 01:24
Serum Studies: Renal Function Tests
 01:02
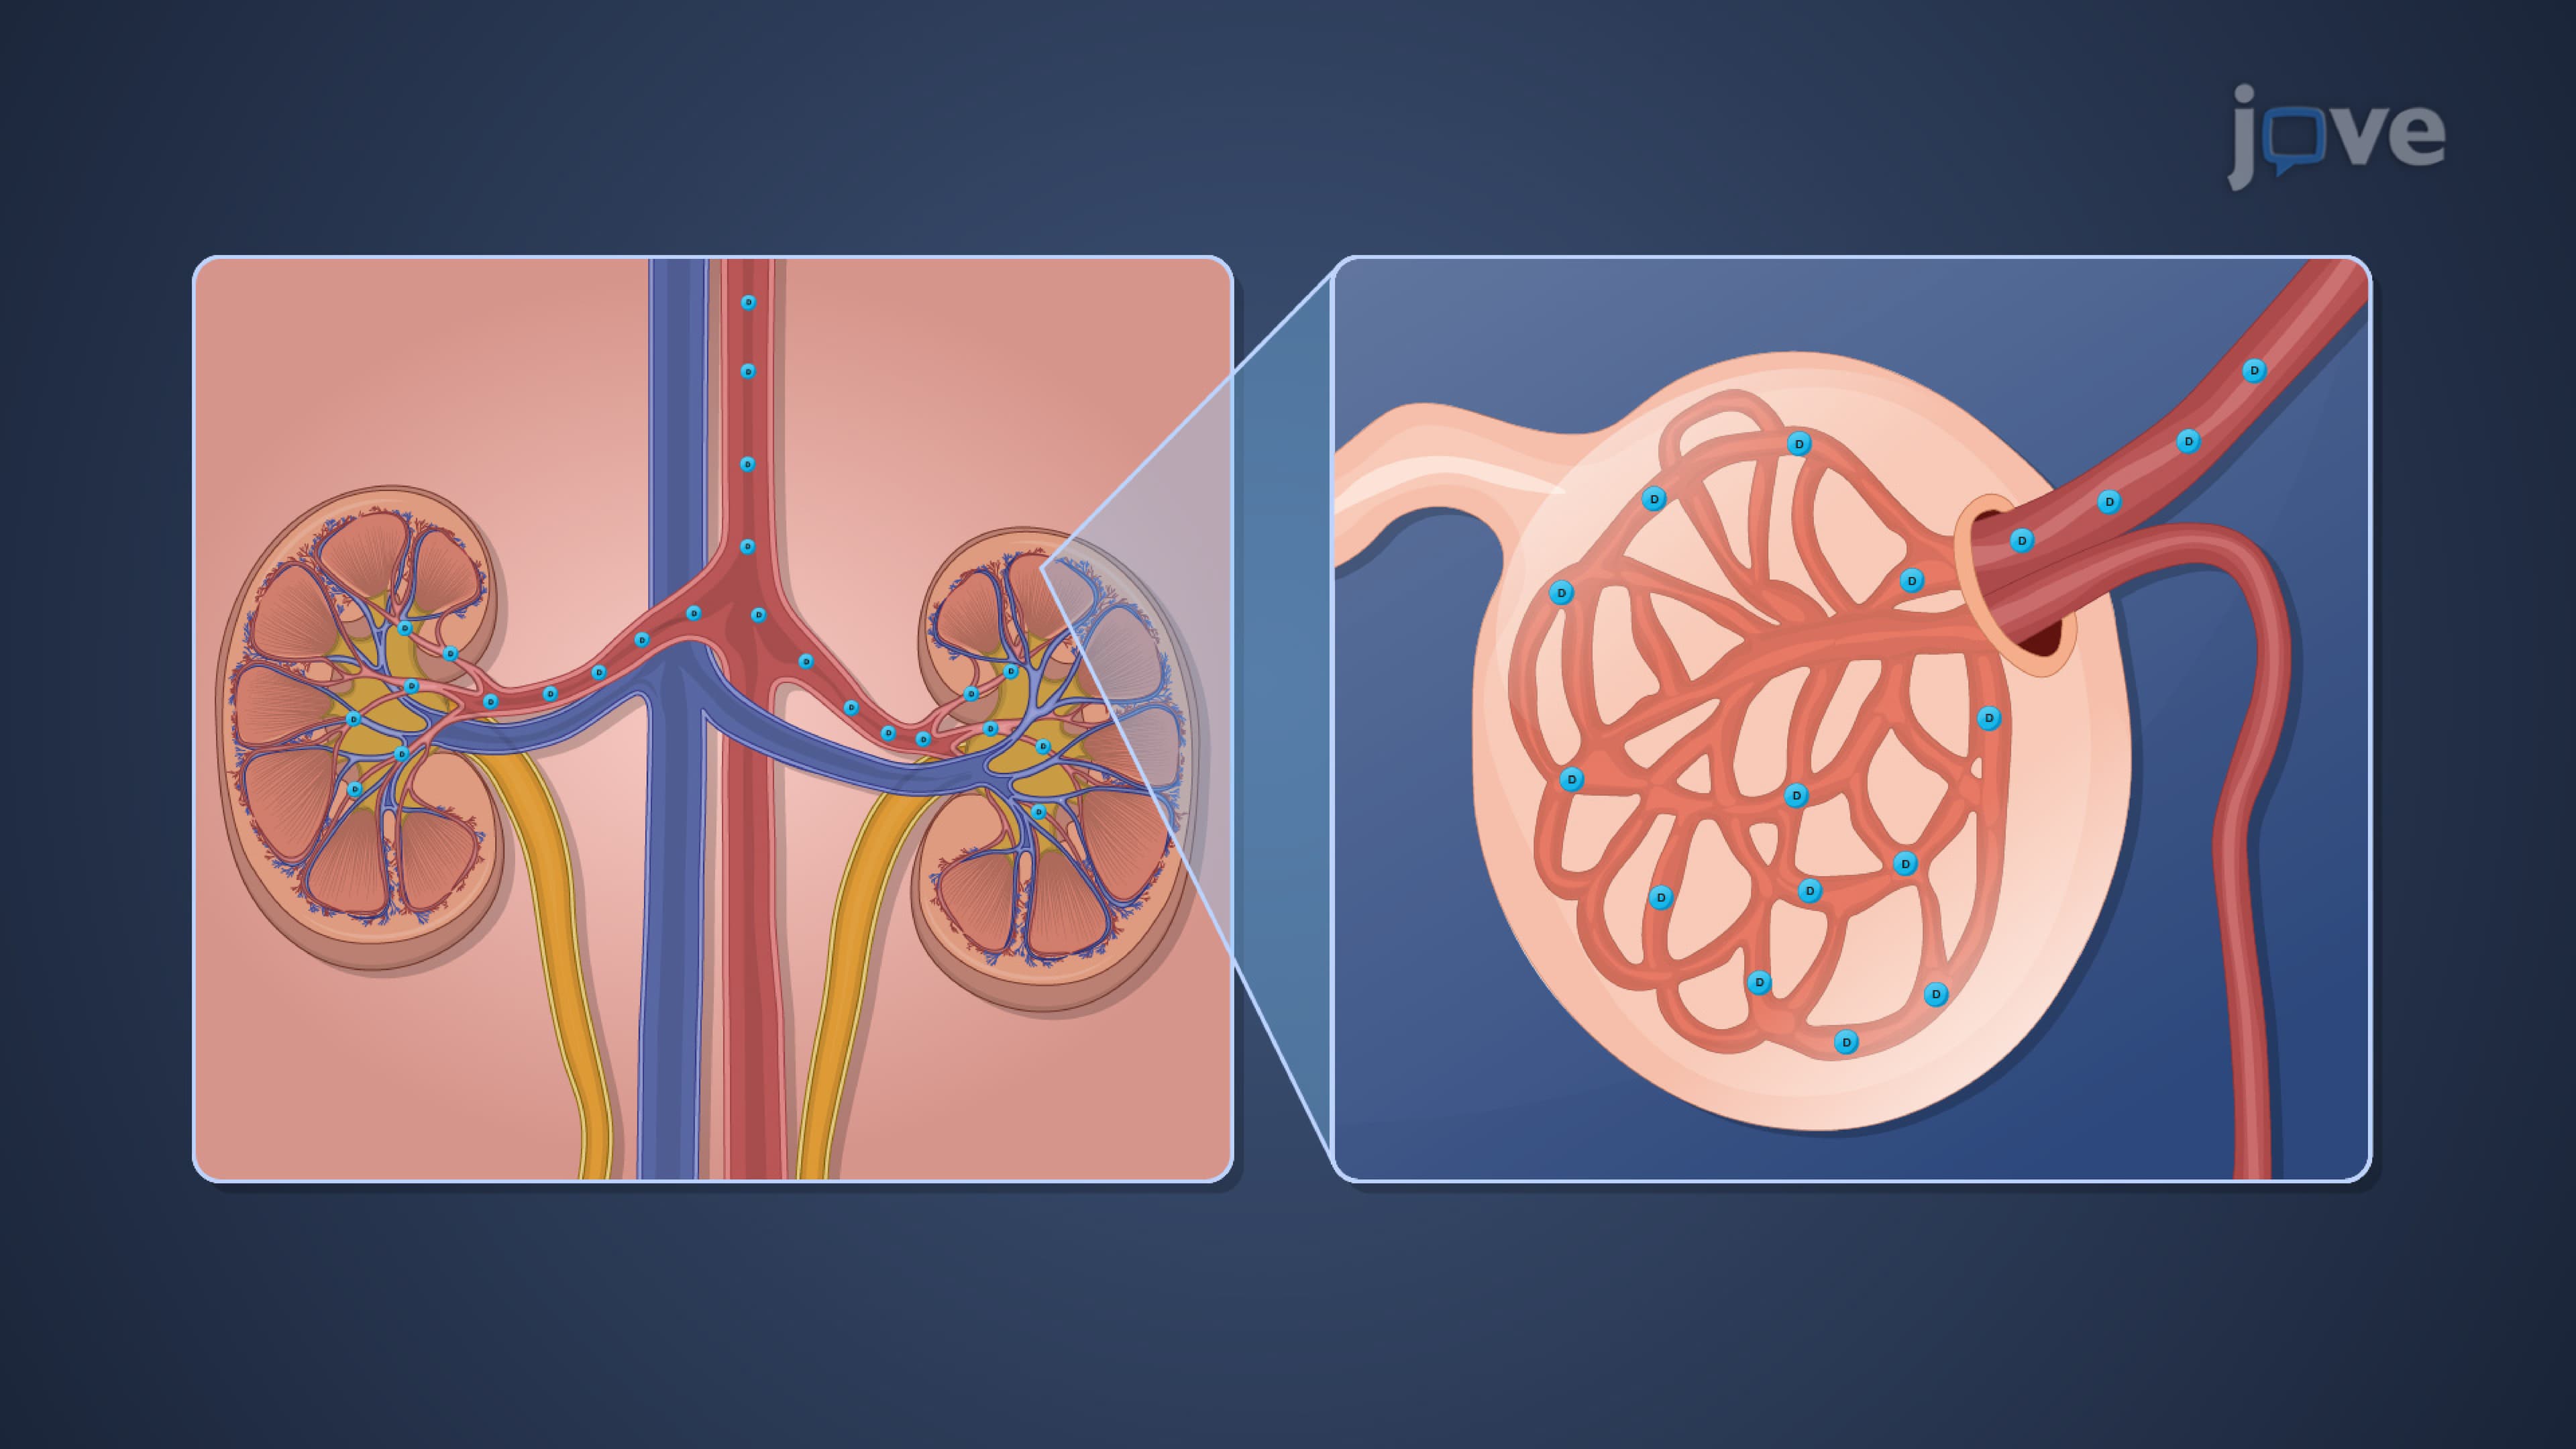
Renal Drug Excretion: Glomerular Filtration
Drugs gain access to the kidney via the renal artery, which progressively branches off into afferent arterioles....