Related Experiment Video
Updated: Mar 6, 2026
Evaluation of Respiratory Muscle Activation Using Respiratory Motor Control Assessment RMCA in Individuals with Chronic Spinal Cord Injury
Published on: July 19, 2013
Comparison of differences in respiratory function and pressure as a predominant abnormal movement of children with
1Department of Physical Therapy, College of Nursing and Healthcare Science, Dong-eui University, Republic of Korea.

Insights
Children with cerebral palsy (CP) show distinct differences in respiratory function and pressure based on their motor type (spastic, dyskinetic, ataxic). These findings aid pediatric physical therapists in tailoring interventions for improved respiratory capacity in children with CP.
Area of Science:
- Pediatrics
- Neurology
- Pulmonology
Background:
- Cerebral palsy (CP) presents with diverse motor impairments affecting overall health.
- Understanding specific functional differences among CP subtypes is crucial for targeted rehabilitation.
- Respiratory compromise is a common concern in children with CP.
Purpose of the Study:
- To investigate and compare respiratory function and pressure.
- To differentiate between spastic, dyskinetic, and ataxic CP types.
- To inform clinical practice and intervention strategies.
Main Methods:
- Study included 43 children (5-13 years) with CP, classified by Gross Motor Function Classification System levels I-III.
- Participants were stratified into spastic, dyskinetic, and ataxic groups.
- Respiratory function (FVC, FEV1, PEF) and pressures (MIP, MEP) were measured using a Spirometer Pony FX.
Main Results:
- Significant differences were observed across the three CP groups in forced vital capacity (FVC), forced expiratory volume at one second (FEV1), and peak expiratory flow (PEF).
- Maximal inspiratory pressure (MIP) showed significant variations among the groups.
- Maximal expiratory pressure (MEP) did not exhibit significant differences across the spastic, dyskinetic, and ataxic CP types.
Conclusions:
- Pediatric physical therapists can utilize these findings to understand subtype-specific respiratory characteristics in children with CP.
- This knowledge supports the development of individualized intervention programs to enhance respiratory capacity.
- Recognizing qualitative differences in muscle tone and movement patterns is key for effective respiratory management.
Abstract:
[Purpose] The purpose of this study was to determine differences in respiratory function and pressure among three groups of children with cerebral palsy as a predominant abnormal movement which included spastic type, dyskinetic type, and ataxic type. [Subjects and Methods] Forty-three children with cerebral palsy of 5-13 years of age in I-III levels according to the Gross Motor Function Classification System, the study subjects were divided by stratified random sampling into three groups of spastic type, dyskinetic type, and ataxic type. For reliability of the measurement results, respiratory function and pressure of the children with cerebral palsy were measured by the same inspector using Spirometer Pony FX (Cosmed Ltd., Italy) equipment, and the subject's guardians (legal representative) was always made to observe. [Results] In the respiratory function, there were significant differences among three groups in all of forced vital capacity, forced expiratory volume at one second, and peak expiratory flow. For respiratory pressure, the maximal inspiratory pressure had significant differences among three groups, although the maximal expiratory pressure had no significant difference. [Conclusion] Therefore, pediatric physical therapists could be provided with important clinical information in understanding the differences in respiratory function and pressure for the children with cerebral palsy showing predominantly abnormal movement as a diverse qualitative characteristics of the muscle tone and movement patterns, and in planning intervention programs for improvement of respiratory capacity.

Related Concept Videos
 01:27
Physical Assessment of the Respiratory Tract II: Inspection
Chest Configuration
The chest configuration...
 01:30
Respiratory System Abnormal Finding I: Inspection and Percussion
Inspection Findings
During an inspection, several findings may suggest the presence of respiratory distress or disease. Pursed-lip breathing, where exhalation is slowed by...
 01:24
Pressure Relationships in Thoracic Cavity
Breathing Mechanisms
Both intra-alveolar and intrapleural pressures rely on specific lung properties. The ability to breathe—allowing air to enter the lungs...
 01:17
Pulmonary Cycle: Exhalation
 01:24
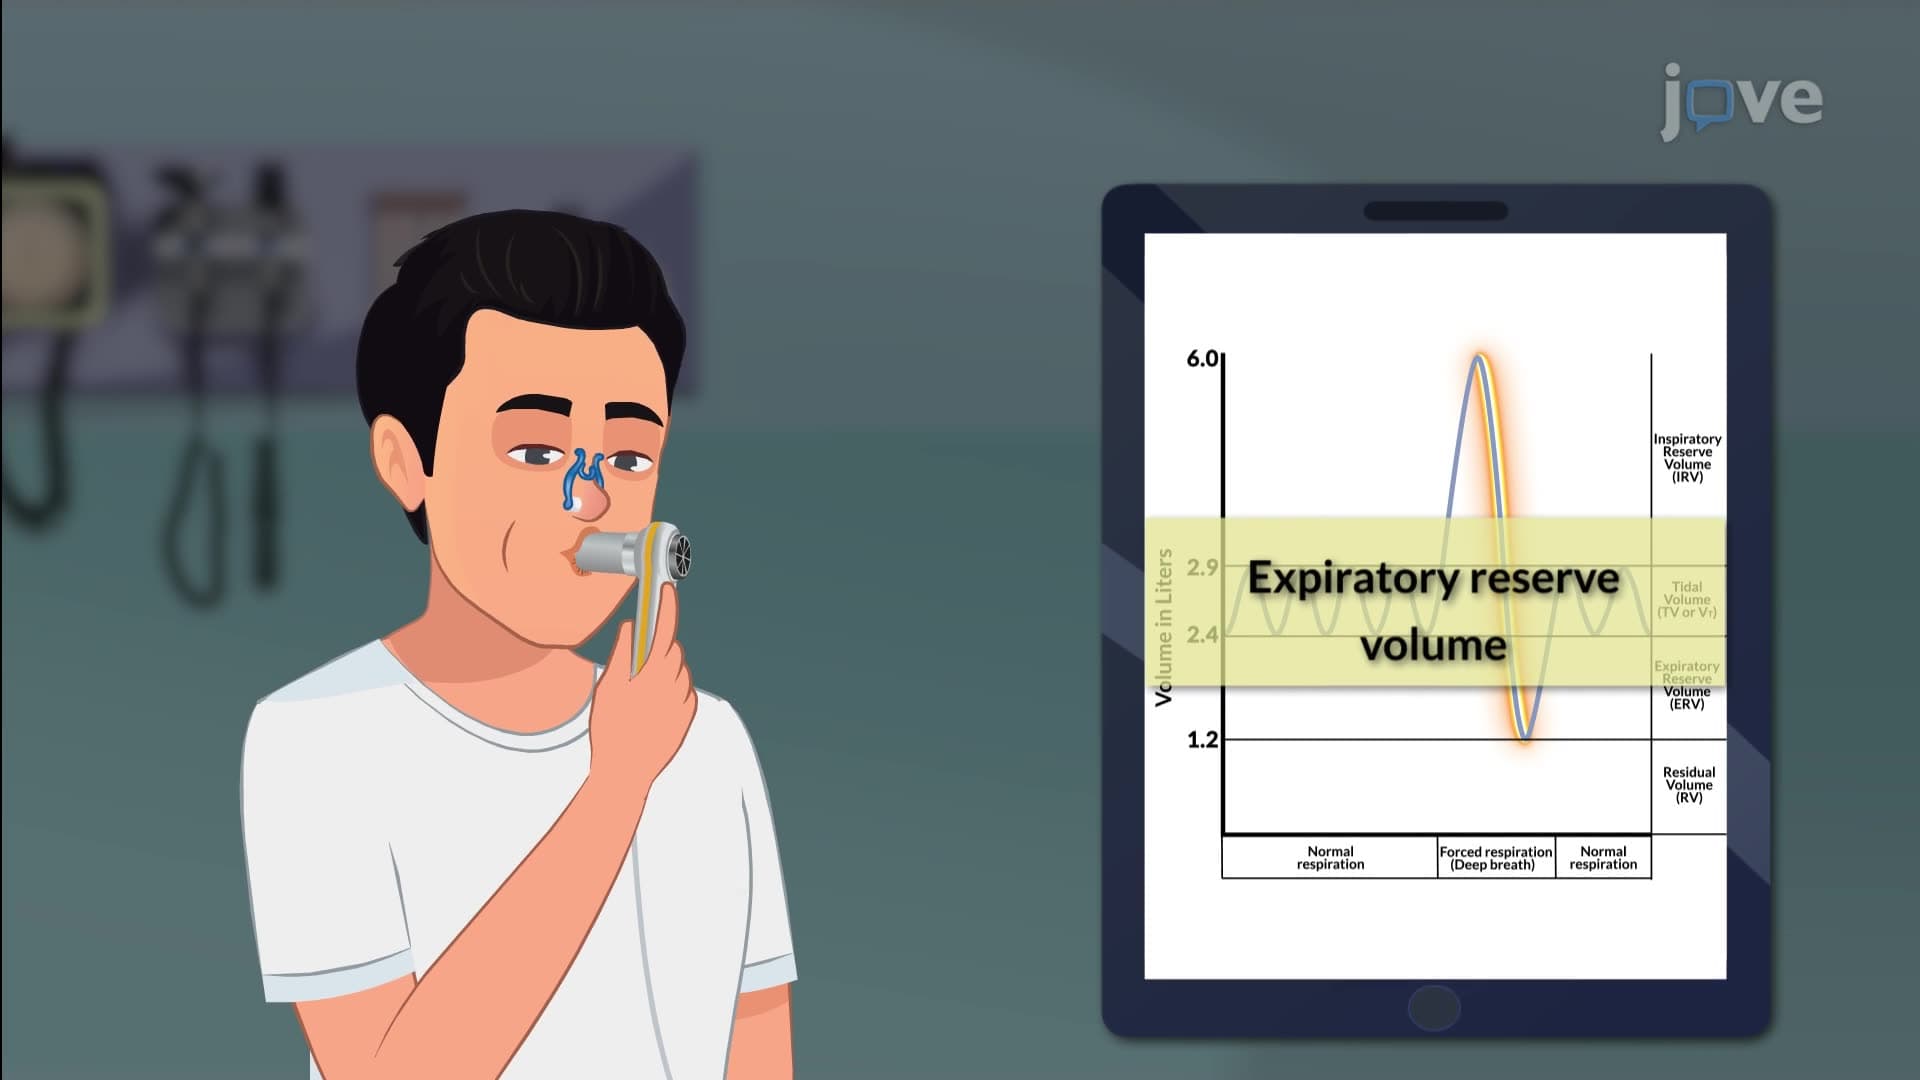
Respiratory Capacities
One key metric is the Inspiratory Capacity (IC), which represents the maximum amount of air that can be inhaled with full effort. IC is calculated by summing the tidal volume and inspiratory reserve volume, typically ranging from 2.4 to 3.6 liters.
The Functional Residual Capacity (FRC) represents the air in the...
 01:15
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...