Related Experiment Video
Updated: Mar 6, 2026
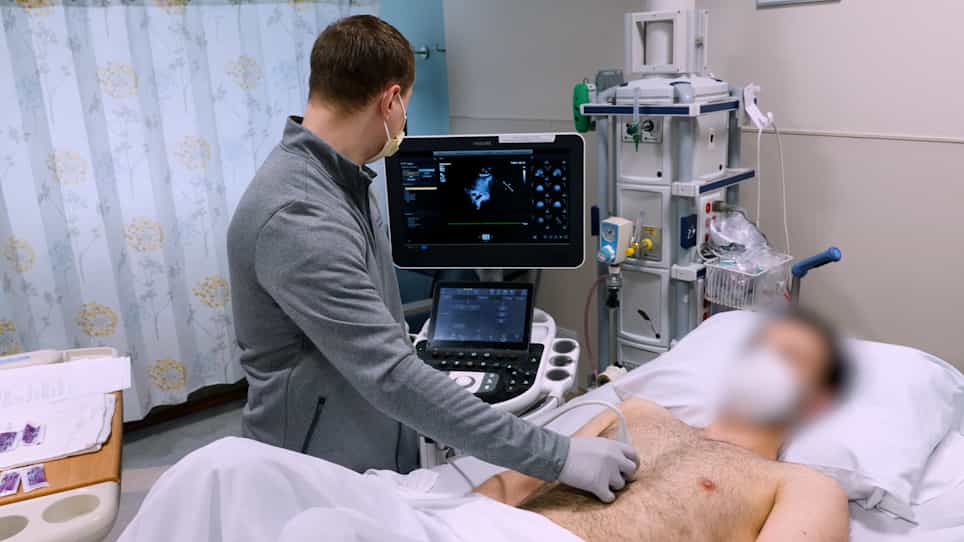
Image Acquisition Method for the Sonographic Assessment of the Inferior Vena Cava
Published on: January 13, 2023
Serial lung and IVC ultrasound in the assessment of congestive heart failure
Rachel Spevack1, Mohamed Al Shukairi2, Dev Jayaraman3
1Internal Medicine Training Program, Department of Medicine, Jewish General Hospital, McGill University, 3755 Chemin de la Cote St Catherine, Montreal, H3T 1E2, Canada. rachel.la.spevack@gmail.com.

Background:
Management of congestive heart failure (CHF) is dependent on clinical assessments of volume status, which are subjective and imprecise. Point-of-care ultrasound (POCUS) is useful in the diagnosis of CHF, but how POCUS findings correlate with therapy remains unknown. This study aimed to determine whether the changes in clinical evaluation of CHF with treatment are mirrored with changes in the number of B lines on lung ultrasound (LUS) and inferior vena cava (IVC) size. In this prospective observational study, investigators performed serial clinical and ultrasound assessments within 24 h of admission (T1), day 1 in hospital (T2) and within 24 h of discharge (T3). Clinical assessments included an evaluation of the jugular venous distension (JVD), hepatojugular reflux (HJR), pulmonary rales and a clinical congestion score was calculated. Ultrasound assessment included the IVC size and collapsibility, and the number of B lines in an 8-point scan.
Results:
Fifty consecutive patients were recruited with a mean age of 71.2 years (SD 12.7). Mean clinical congestion score on admission was 5.6 (SD 1.4) and declined significantly over time to 1.3 (0.91), as did the JVP, HJR and pulmonary rales. No significant changes were found in the IVC size between T1 [1.9 (0.65)] and T3 [2.0 (0.50)] or in the IVC collapsibility index [T1 0.3 (0.19) versus T3 0.25 (0.16)]. The mean number of B lines decreased from 11 (6.1) at T1 to 8.3 (5.5) at T3, although this decrease did not reach statistical significance. Spearman correlation between JVP and HJR versus IVC collapsibility and total B lines did not yield significant results.
Conclusions:
Clinical exam findings correlate over time during the management of CHF, whereas LUS and IVC results did not. The number of B lines did decrease with therapy, but did not reach statistical significance likely because the sampled population was small and had only mild heart failure. Further studies are warranted to further explore the use of lung ultrasound in this patient population.
More Related Videos
 08:22
The Application of Point-of-Care Ultrasonography (POCUS) in the Management of Acute Respiratory Distress Syndrome (ARDS) in the Intensive Care Unit
Published on: December 12, 2025
 07:59
Bedside Ultrasound for Guiding Fluid Removal in Patients with Pulmonary Edema: The Reverse-FALLS Protocol
Published on: July 28, 2018
Related Concept Videos
 01:20
Imaging Studies for Cardiovascular System III: X-Ray
Definition and Purpose
An X-ray, or radiograph, is a non-invasive method that uses ionizing radiation to take images of internal structures. It is mainly used in cardiac imaging to examine the heart, lungs, and major blood vessels, aiming to identify abnormalities in the heart's size, shape, and position, such as heart failure, congenital defects, and vascular...
 01:17
Imaging Studies for Cardiovascular System I:Echocardiography
Indications: Echocardiography is utilized to diagnose heart failure, valve disorders, and myocardial infarction. It also assesses cardiac structures' size, shape, and motion,...
 01:20
Imaging Studies for Cardiovascular System II:Types of Echocardiography
Types of Echocardiography
Transthoracic Echocardiography (TTE)
TTE is the most common type of echocardiogram which involves placing a transducer on the patient's chest, emitting sound waves to create heart images. TTE is invaluable for evaluating the heart's size, structure, and motion, making it particularly useful for...
 01:25
Assessment of the Cardiovascular System IV: Auscultation
Normal Heart Sounds
S1 (First Heart Sound)-
S1 is made by the closure of the mitral and tricuspid valves (atrioventricular valves), marking the beginning of systole.
S2 (Second Heart Sound)-
S2 is made by the closure of the aortic and pulmonic valves (semilunar valves), marking the end of the systole.
 01:23
Mitral Stenosis II: Clinical features and Diagnostic Tests
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies