Related Experiment Video
Updated: Mar 6, 2026
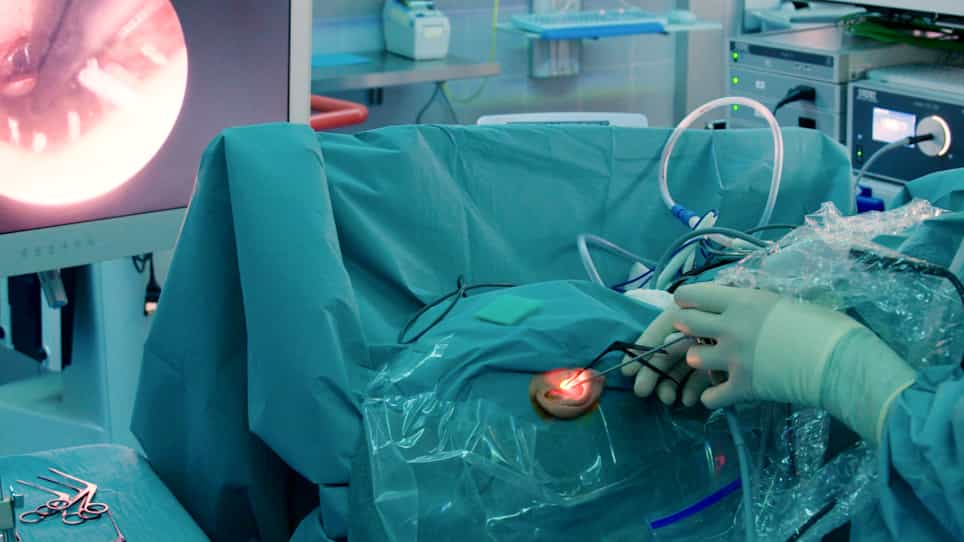

Endoscopic Cholesteatoma Surgery
Published on: January 19, 2022
Intraoperative Bleeding and the Risk of Residual Cholesteatoma: A Multivariate Analysis
Gavin J le Nobel1, Sharon L Cushing, Blake C Papsin
1*Department of Otolaryngology Head and Neck Surgery, University of Toronto†Hospital for Sick Children, Toronto, Ontario, Canada.

Objective:
Residual cholesteatoma most frequently occurs where visualization and surgical access are restricted by anatomic constraints. Other factors that compromise surgical field visualization might also increase rates of residual cholesteatoma. We evaluated whether impaired surgical field clarity from bleeding increases rates of residual cholesteatoma.
Study Design:
Prospective cohort study.
Setting:
Tertiary care hospital.
Patients:
Consecutive series of children having intact canal wall surgery for cholesteatoma.
Interventions:
Impact of bleeding on surgical field clarity was assessed intraoperatively on a six-point scale.
Main Outcome Measures:
Presence of residual cholesteatoma was established at follow up clinical encounters, second stage procedures, and with magnetic resonance imaging. Multiple logistic regression was used to determine the influence of surgical field clarity and other factors on rates of residual cholesteatoma.
Results:
Surgery was completed on 232 ears and residual cholesteatoma found in 45 (19%) ears. Multivariate regression analysis of cases completed with atticotomy or tympanoplasty demonstrated that surgical field clarity was a significant predictor of residual cholesteatoma (OR [odds ratio] 4, 95%CI 1.05-15; p = 0.04). Cholesteatoma extent was the most significant predictor of residual cholesteatoma when including cases requiring combined approach tympanomastoidectomy (OR 2.2, 95%CI 1.4-3.3; p < 0.001).
Conclusions:
Impaired surgical field clarity from intraoperative bleeding is associated with increased risk of residual cholesteatoma in surgery for meso/epitympanic cholesteatoma. These findings are of particular significance for endoscopic ear surgery in which management of bleeding can be more difficult and support the use of techniques, such as hypotensive general anesthesia, that minimize surgical site bleeding and improve surgical field visualization.

