Platysma Motor Nerve Transfer for Restoring Marginal Mandibular Nerve Function
Related Experiment Video
Updated: Mar 6, 2026
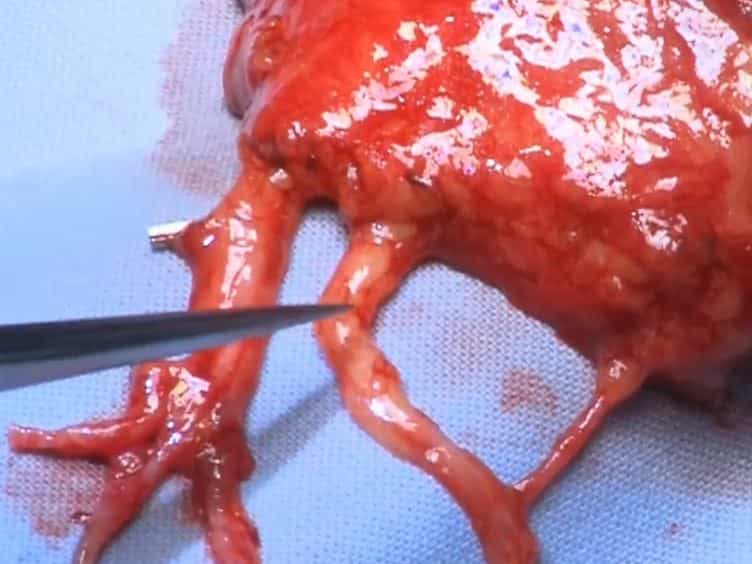
Single-stage Dynamic Reanimation of the Smile in Irreversible Facial Paralysis by Free Functional Muscle Transfer
Published on: March 1, 2015
Andres Rodriguez-Lorenzo1, David Jensson1, Wolfgang J Weninger1
1Department of Plastic and Maxillofacial Surgery, Uppsala University Hospital, Uppsala, Sweden; Department of Surgical Sciences, Uppsala University, Uppsala, Sweden; and Center of Anatomy and Cell Biology and Division of Plastic and Reconstructive Surgery, Department of Surgery, Medical University of Vienna, Vienna, Austria.

Background:
Injuries of the marginal mandibular nerve (MMN) of the facial nerve result in paralysis of the lower lip muscle depressors and an asymmetrical smile. Nerve reconstruction, when possible, is the method of choice; however, in cases of long nerve gaps or delayed nerve reconstruction, conventional nerve repairs may be difficult to perform or may provide suboptimal outcomes. Herein, we investigate the anatomical technical feasibility of transfer of the platysma motor nerve (PMN) to the MMN for restoration of lower lip function, and we present a clinical case where this nerve transfer was successfully performed.
Methods:
Ten adult fresh cadavers were dissected. Measurements included the number of MMN and PMN branches, the maximal length of dissection of the PMN from the parotid, and the distance from the anterior border of the parotid to the facial artery. The PMN reach for direct coaptation to the MMN at the level of the crossing with the facial artery was assessed. We performed histomorphometric analysis of the MMN and PMN branches.
Results:
The anatomy of the MMN and PMN was consistent in all dissections, with an average number of subbranches of 1.5 for the MMN and 1.2 for the PMN. The average maximal length of dissection of the PMN was 46.5 mm, and in every case, tension-free coaptation with the MMN was possible. Histomorphometric analysis demonstrated that the MMN contained an average of 3,866 myelinated fiber counts per millimeter, and the PMN contained 5,025. After a 3-year follow-up of the clinical case, complete recovery of MMN function was observed, without the need of central relearning and without functional or aesthetic impairment resulting from denervation of the platysma muscle.
Conclusions:
PMN to MMN transfer is an anatomically feasible procedure for reconstruction of isolated MMN injuries. In our patient, by direct nerve coaptation, a faster and full recovery of lower lip muscle depressors was achieved without the need of central relearning because of the synergistic functions of the PMN and MMN functions and minimal donor-site morbidity.
More Related Videos
 06:48
Ethanol-Induced Cervical Sympathetic Ganglion Block Applications for Promoting Canine Inferior Alveolar Nerve Regeneration Using an Artificial Nerve
Published on: November 30, 2018
 05:04
Facial Nerve Surgery in the Rat Model to Study Axonal Inhibition and Regeneration
Published on: May 5, 2020
Related Concept Videos
 01:14
Cranial Nerves: Types Part I
Olfactory Nerve (Cranial Nerve I)
The olfactory nerve, or cranial nerve I, is unique as it is purely sensory and dedicated to the sense of smell. This nerve originates in the olfactory epithelium of the...
 01:22
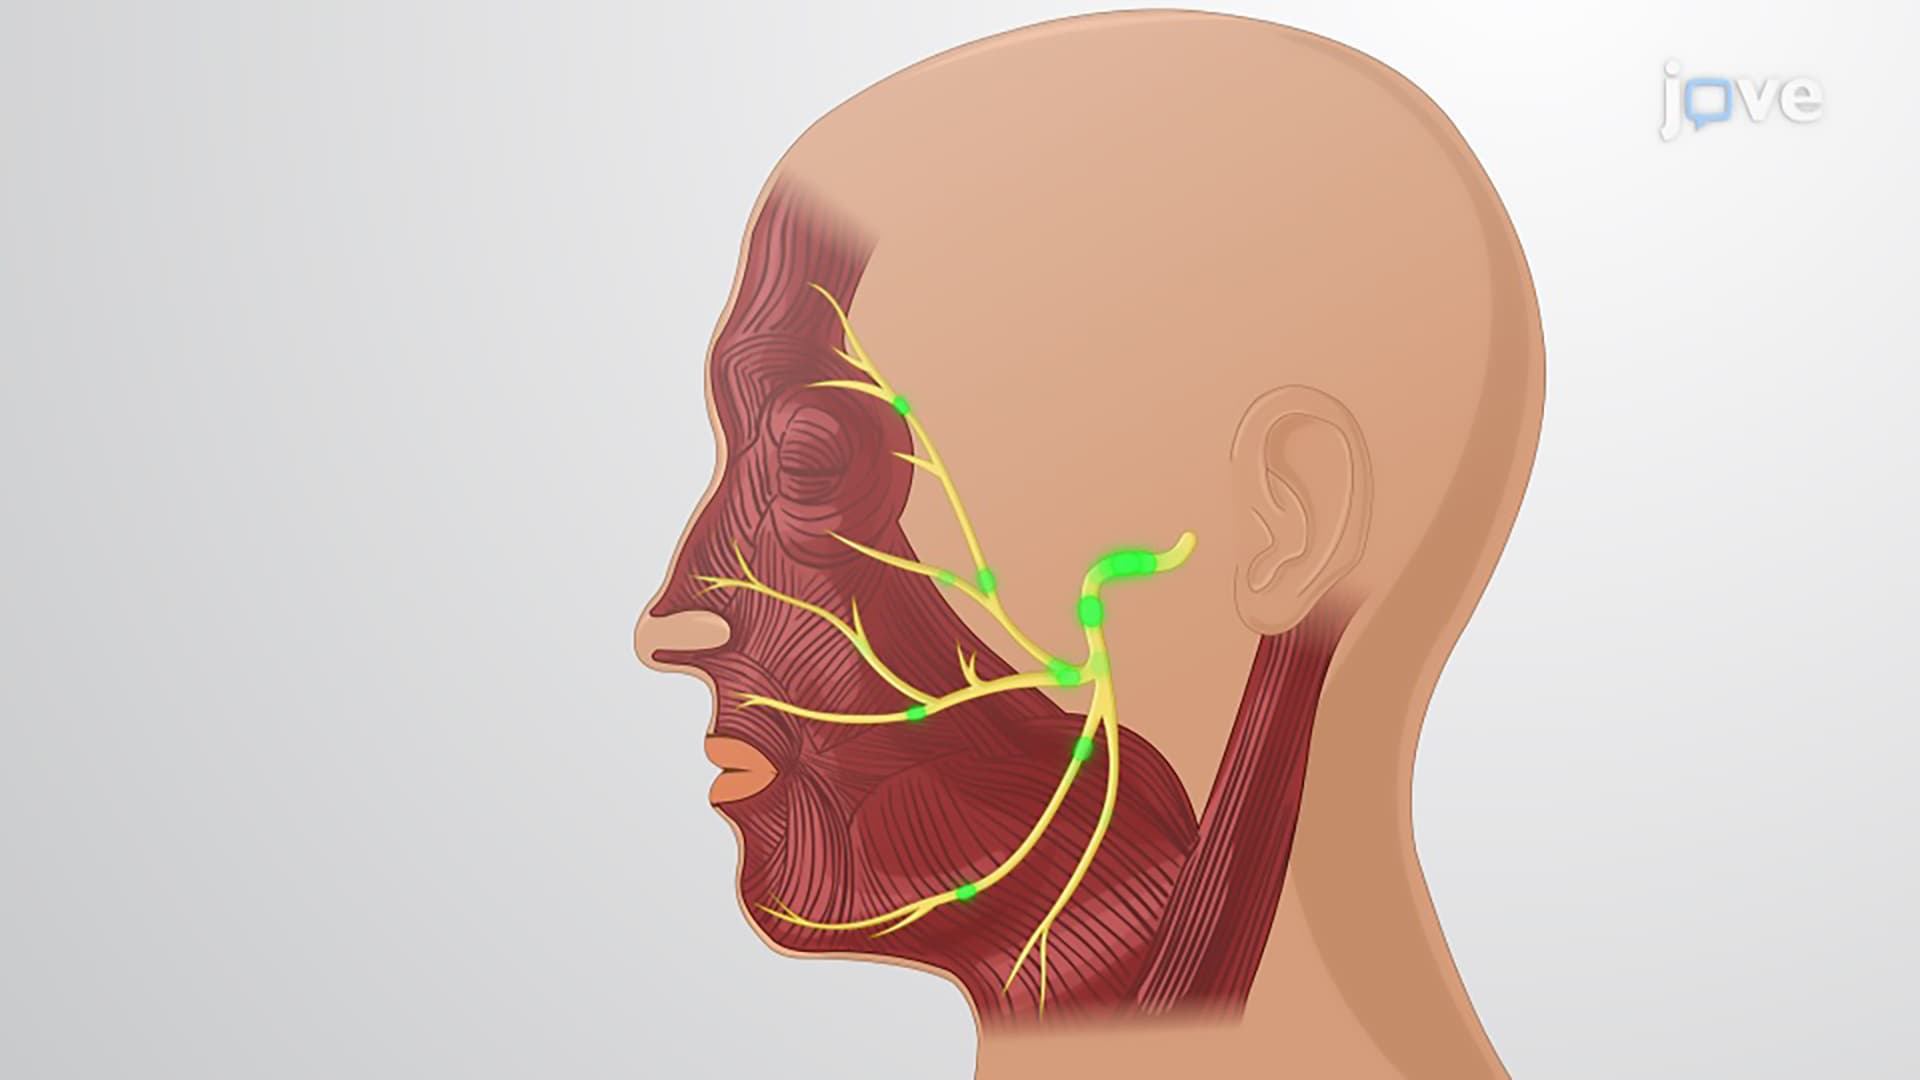
Cranial Nerves: Types Part II
Facial Nerve (Cranial Nerve VII)
Cranial nerve VII, or the facial nerve,...