Related Experiment Video
Updated: Mar 6, 2026


Author Spotlight: Modeling an Aspect of Preeclampsia in Female Mice Using Hypoxic Human Placenta-Derived Small Extracellular Vesicles
Published on: January 26, 2024
Multicenter screening for pre-eclampsia by maternal factors and biomarkers at 11-13 weeks' gestation: comparison with
N O'Gorman1, D Wright2, L C Poon1,3
1Harris Birthright Center for Fetal Medicine, King's College Hospital, London, UK.

Insights
The Fetal Medicine Foundation (FMF) algorithm significantly outperforms NICE and ACOG screening methods for pre-eclampsia (PE). This advanced screening for PE in early pregnancy offers superior detection rates and is crucial for timely intervention.
Area of Science:
- Maternal-fetal medicine
- Obstetric screening protocols
- Diagnostic test performance evaluation
Background:
- Pre-eclampsia (PE) screening is critical for early intervention and improved maternal-fetal outcomes.
- Current screening guidelines from NICE and ACOG rely on maternal history and risk factors.
- The Fetal Medicine Foundation (FMF) proposes an algorithm integrating maternal factors with biophysical and biochemical markers.
Purpose of the Study:
- To compare the diagnostic performance of the FMF pre-eclampsia screening algorithm against NICE and ACOG guidelines.
- To evaluate detection rates (DRs) and false-positive rates (FPRs) for various gestational ages of PE delivery.
- To assess the efficacy of different screening strategies in identifying pregnancies at risk for pre-eclampsia.
Main Methods:
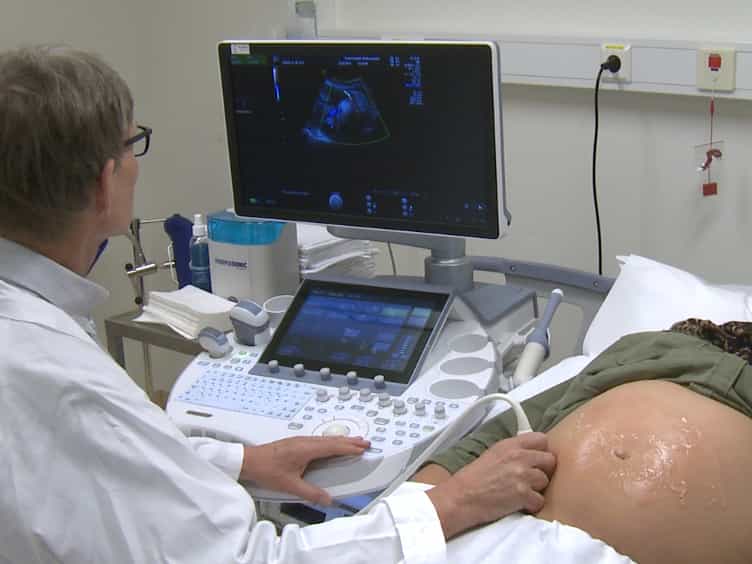
- Prospective multicenter study involving 8775 singleton pregnancies at 11-13 weeks' gestation.
- Utilized a validated FMF algorithm combining maternal factors, mean arterial pressure (MAP), uterine artery pulsatility index (UtA-PI), and serum placental growth factor (PlGF).
- Compared FMF algorithm performance with screening based on NICE and ACOG recommendations for PE detection and aspirin use.
Main Results:
- The FMF algorithm achieved 100% DR for PE <32 weeks, 75% for PE <37 weeks, and 43% for PE ≥37 weeks, with a 10.0% FPR.
- NICE guidelines yielded lower DRs (41% for <32 weeks) at a similar FPR (10.2%).
- ACOG recommendations showed high DRs (90% for <37 weeks) but with a significantly higher FPR (64.2%).
Conclusions:
- The FMF algorithm demonstrates superior performance in screening for pre-eclampsia at 11-13 weeks' gestation compared to NICE and ACOG methods.
- Integration of maternal factors with MAP, UtA-PI, and PlGF offers a more effective approach to PE screening.
- The findings support the adoption of the FMF algorithm for enhanced early detection and management of pre-eclampsia.
Objective:
To compare the performance of screening for pre-eclampsia (PE) based on risk factors from medical history, as recommended by NICE and ACOG, with the method proposed by The Fetal Medicine Foundation (FMF), which uses Bayes' theorem to combine the a-priori risk from maternal factors, derived by a multivariable logistic model, with the results of various combinations of biophysical and biochemical measurements.
Methods:
This was a prospective multicenter study of screening for PE in 8775 singleton pregnancies at 11-13 weeks' gestation. A previously published FMF algorithm was used for the calculation of patient-specific risk of PE in each individual. The detection rates (DRs) and false-positive rates (FPRs) for delivery with PE < 32, < 37 and ≥ 37 weeks were estimated and compared with those derived from application of NICE guidelines and ACOG recommendations. According to NICE, all high-risk pregnancies should be offered low-dose aspirin. According to ACOG, use of aspirin should be reserved for women with a history of PE in at least two previous pregnancies or PE requiring delivery < 34 weeks' gestation.
Results:
In the study population, 239 (2.7%) cases developed PE, of which 17 (0.2%), 59 (0.7%) and 180 (2.1%) developed PE < 32, < 37 and ≥ 37 weeks, respectively. Screening with use of the FMF algorithm based on a combination of maternal factors, mean arterial pressure (MAP), uterine artery pulsatility index (UtA-PI) and serum placental growth factor (PlGF) detected 100% (95% CI, 80-100%) of PE < 32 weeks, 75% (95% CI, 62-85%) of PE < 37 weeks and 43% (95% CI, 35-50%) of PE ≥ 37 weeks, at a 10.0% FPR. Screening with use of NICE guidelines detected 41% (95% CI, 18-67%) of PE < 32 weeks, 39% (95% CI, 27-53%) of PE < 37 weeks and 34% (95% CI, 27-41%) of PE ≥ 37 weeks, at 10.2% FPR. Screening with use of ACOG recommendations detected 94% (95% CI, 71-100%) of PE < 32 weeks, 90% (95% CI, 79-96%) of PE < 37 weeks and 89% (95% CI, 84-94%) of PE ≥ 37 weeks, at 64.2% FPR. Screening based on the ACOG recommendations for use of aspirin detected 6% (95% CI, 1-27%) of PE < 32 weeks, 5% (95% CI, 2-14%) of PE < 37 weeks and 2% (95% CI, 0.3-5%) of PE ≥ 37 weeks, at 0.2% FPR.
Conclusion:
Performance of screening for PE at 11-13 weeks' gestation by the FMF algorithm using a combination of maternal factors, MAP, UtA-PI and PlGF, is by far superior to the methods recommended by NICE and ACOG. Copyright © 2017 ISUOG. Published by John Wiley & Sons Ltd.