Related Experiment Video
Updated: Mar 6, 2026
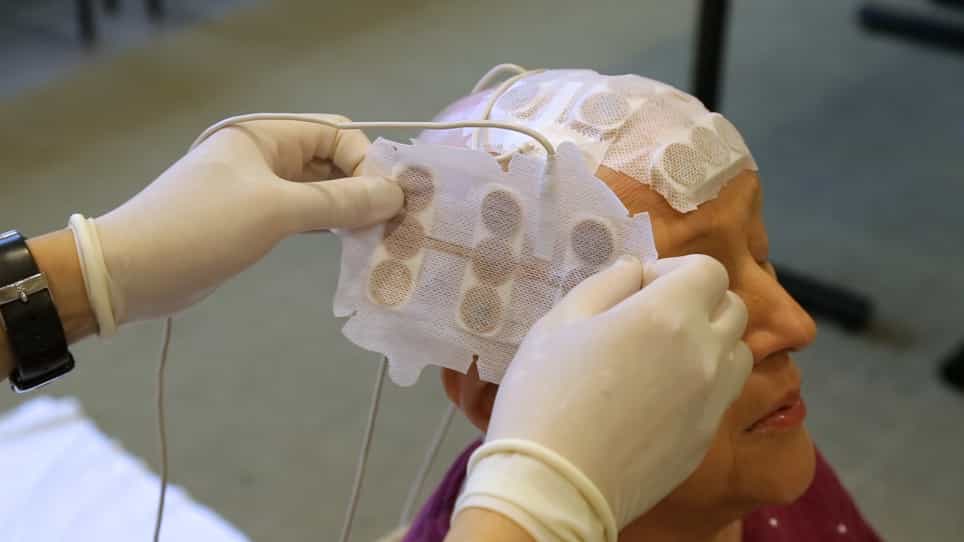

The Clinical Application of Tumor Treating Fields Therapy in Glioblastoma
Published on: April 16, 2019
Limited role for extended maintenance temozolomide for newly diagnosed glioblastoma
Dorothee Gramatzki1, Philipp Kickingereder2, Bettina Hentschel2
1From the Department of Neurology and Brain Tumor Center (D.G., M.W.), University Hospital Zurich and University of Zurich, Switzerland; Department of Neuroradiology (P.K., M.B.), University Hospital of Heidelberg; Institute for Medical Informatics, Statistics and Epidemiology (B.H., M.L.), University of Leipzig; Departments of Neuropathology (J.F., G.R.) and Neurosurgery (M.S.), Heinrich-Heine University Düsseldorf; Division of Neurooncology (U.H.), Department of Neurology, University Medical Center Bonn; Department of Neurosurgery (G.S.), University of Dresden; Department of Neurosurgery (J.-C.T.), Ludwig Maximilians University Munich; Department of Neurosurgery (M.W.), University Medical Center Hamburg-Eppendorf, Hamburg; Department of Neurology (U.S.), Knappschaftskrankenhaus Bochum-Langendreer, Ruhr-University Bochum; Clinical Cooperation Unit Neurooncology (W.W.), German Cancer Consortium, German Cancer Research Center, and Neurology Clinic and National Center for Tumor Diseases, University Hospital Heidelberg; Department of Neuropathology (T.P.), DGNN Brain Tumor Reference Center, University of Bonn Medical School; and German Cancer Consortium (G.R.), German Cancer Research Center Heidelberg, Partner Site Essen/Düsseldorf, Düsseldorf, Germany. dorothee.gramatzki@usz.ch.

Objective:
To explore an association with survival of modifying the current standard of care for patients with newly diagnosed glioblastoma of surgery followed by radiotherapy plus concurrent and 6 cycles of maintenance temozolomide chemotherapy (TMZ/RT → TMZ) by extending TMZ beyond 6 cycles.
Methods:
The German Glioma Network cohort was screened for patients with newly diagnosed glioblastoma who received TMZ/RT → TMZ and completed ≥6 cycles of maintenance chemotherapy without progression. Associations of clinical patient characteristics, molecular markers, and residual tumor determined by magnetic resonance imaging after 6 cycles of TMZ with progression-free survival (PFS) and overall survival (OS) were analyzed with the log-rank test. Multivariate analyses using the Cox proportional hazards model were performed to assess associations of prolonged TMZ use with outcome.
Results:
Sixty-one of 142 identified patients received at least 7 maintenance TMZ cycles (median 11, range 7-20). Patients with extended maintenance TMZ treatment had better PFS (20.5 months, 95% confidence interval [CI] 17.7-23.3, vs 17.2 months, 95% CI 10.2-24.2, p = 0.035) but not OS (32.6 months, 95% CI 28.9-36.4, vs 33.2 months, 95% CI 25.3-41.0, p = 0.126). However, there was no significant association of prolonged TMZ chemotherapy with PFS (hazard ratio [HR] = 0.8, 95% CI 0.4-1.6, p = 0.559) or OS (HR = 1.6, 95% CI 0.8-3.3, p = 0.218) adjusted for age, extent of resection, Karnofsky performance score, presence of residual tumor, O6-methylguanine DNA methyltransferase (MGMT) promoter methylation status, or isocitrate dehydrogenase (IDH) mutation status.
Conclusion:
These data may not support the practice of prolonging maintenance TMZ chemotherapy beyond 6 cycles.
Classification Of Evidence:
This study provides Class III evidence that in patients with newly diagnosed glioblastoma, prolonged TMZ chemotherapy does not significantly increase PFS or OS.


