ST-Elevation Myocardial Infarction after Penetrating Thoracic Trauma
Kiran Faryar1, Michael P Flaherty2, Martin Huecker1
1Department of Emergency Medicine, University of Louisville, Louisville, Kentucky.

Insights
ST-segment elevation myocardial infarction (STEMI) can occur after chest trauma. This case highlights that conservative management may be suitable for stable patients without coronary artery issues.
Area of Science:
- Emergency Medicine
- Cardiology
- Trauma Surgery
Background:
- Penetrating thoracic trauma can lead to ST-segment elevation myocardial infarction (STEMI).
- Prompt recognition and evaluation are crucial for appropriate patient management.
Observation:
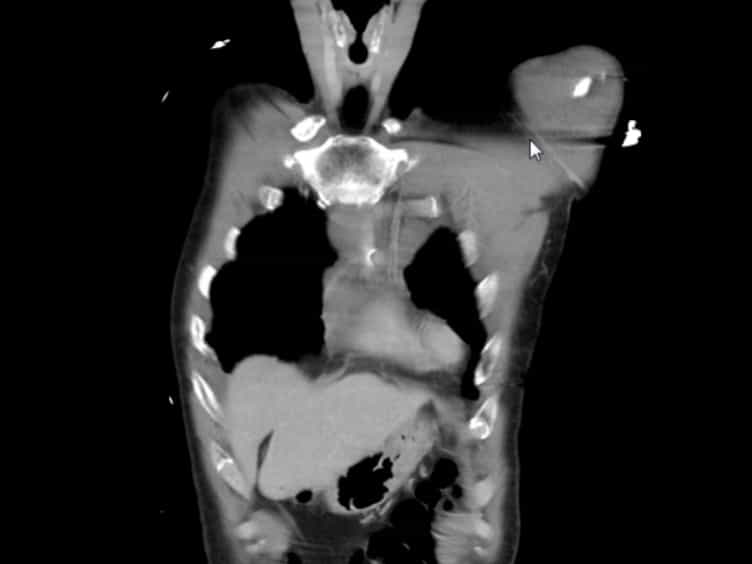
- A case report of a 42-year-old male with a self-inflicted gunshot wound to the chest presented with STEMI.
- Initial management involved conservative treatment due to hemodynamic stability.
- Subsequent cardiac catheterization revealed no coronary artery atherosclerosis or traumatic injury.
Findings:
- STEMI occurred in the absence of detectable plaque rupture or direct coronary trauma.
- This presentation is unusual and challenges typical STEMI etiologies.
Implications:
- The decision for emergent coronary angiography in trauma-related STEMI should be individualized based on hemodynamic status and cardiac risk factors.
- Conservative medical management is a viable option for asymptomatic, hemodynamically stable patients.
- Myocardial infarction should be considered in the initial assessment of penetrating thoracic injuries.
Background:
ST-segment elevation myocardial infarction (STEMI) may complicate penetrating thoracic trauma.
Case Report:
This report describes a 42-year-old man who sustained a self-inflicted gunshot wound to the left chest. Electrocardiogram showed ST elevation in the inferior leads. Emergent catheterization was not recommended and conservative management was initiated. Cardiac catheterization 4 days later showed no perturbation of the coronary arteries, neither atherosclerotic nor traumatic. WHY SHOULD AN EMERGENCY PHYSICIAN BE AWARE OF THIS?: This case is unusual because it demonstrates a STEMI with no detectable plaque rupture or gunshot pellets on coronary catheterization. The decision to aggressively manage these patients with early coronary angiography depends on the hemodynamic status of the patient, their cardiac risk factors, and their ability to tolerate ischemic insult. In asymptomatic hemodynamically stable patients, conservative medical management should be considered. Myocardial infarction is a complication after penetrating thoracic trauma and should be considered in initial evaluation.
More Related Videos
Related Concept Videos
 01:30
Acute Coronary Syndrome I: Introduction
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:22
Esophageal Perforation-I: Introduction
The location of esophageal perforation can vary, occurring anywhere along the esophagus....
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:26
Pneumothorax-I
Pneumothorax can be even further classified as spontaneous, traumatic, and tension pneumothorax.