Related Experiment Video
Updated: Mar 6, 2026
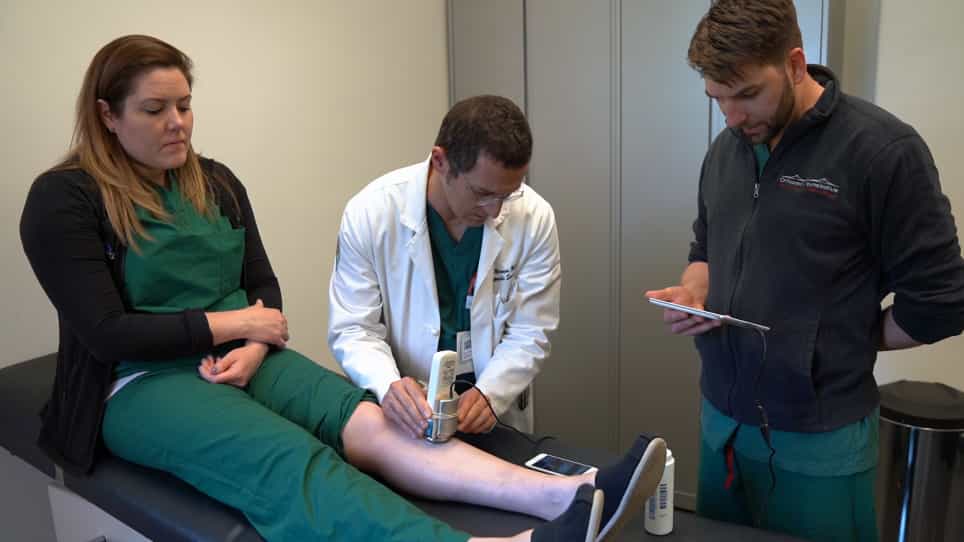

A Novel Non-invasive Method for the Detection of Elevated Intra-compartmental Pressures of the Leg
Published on: May 31, 2019
Pediatric Acute Compartment Syndrome
Kristin S Livingston1, Michael P Glotzbecker, Benjamin J Shore
1From the Department of Orthopaedic Surgery, University of California San Francisco School of Medicine, San Francisco, CA (Dr. Livingston) and the Department of Orthopaedic Surgery, Harvard Medical School, Boston Children's Hospital, Boston, MA (Dr. Glotzbecker and Dr. Shore).

Insights
Pediatric acute compartment syndrome (PACS) requires differentiation from adult cases. Early detection using the "three As" (anxiety, agitation, analgesic requirement) and compartment pressure measurement improves outcomes.
Area of Science:
- Pediatric Orthopedics
- Emergency Medicine
- Surgical Critical Care
Background:
- Pediatric acute compartment syndrome (PACS) presents differently than adult acute compartment syndrome.
- Understanding PACS's varied causes, including trauma, vascular issues, infection, and more, is crucial for healthcare providers.
- Recognizing unique PACS signs and symptoms is essential for timely diagnosis.
Purpose of the Study:
- To highlight the differences between pediatric and adult acute compartment syndrome.
- To emphasize the importance of recognizing unique pediatric presentations and diagnostic tools.
- To underscore the impact of diagnostic delays on patient outcomes.
Main Methods:
- Review of clinical presentations and diagnostic criteria for PACS.
- Comparison of pediatric and adult acute compartment syndrome signs and symptoms.
- Discussion of diagnostic adjuncts like compartment pressure measurement.
- Analysis of treatment outcomes following fasciotomy in pediatric patients.
Main Results:
- Trauma is the most common cause of PACS, but other etiologies exist.
- The "three As" (anxiety, agitation, analgesic requirement) are more accurate indicators in children than classic adult signs.
- Compartment pressure measurement may be necessary for diagnosis in ambiguous cases.
- Fasciotomy generally yields excellent outcomes in children, provided diagnosis is not delayed.
Conclusions:
- Accurate differentiation of PACS from adult acute compartment syndrome is vital.
- Early detection of PACS through unique pediatric signs and diagnostic measures is critical.
- Timely intervention, such as fasciotomy, leads to favorable outcomes, while delays can result in severe complications like myonecrosis.
Abstract:
Pediatric acute compartment syndrome (PACS) is a clinical entity that must be carefully differentiated from the adult version (ie, acute compartment syndrome). Healthcare providers must understand the variable etiologies of PACS, of which trauma is the most common but can also include vascular insult, infection, surgical positioning, neonatal phenomena, overexertion, and snake and insect bites. In addition to the unique etiologies of PACS, providers must also recognize the different signs and symptoms of PACS. The three As (ie, anxiety, agitation, analgesic requirement) of PACS have supplanted the classic adult signs as being more accurate and allowing earlier detection. In children with questionable clinical signs but concern for PACS, compartment pressure measurement may be necessary to confirm the diagnosis. Overall, outcomes after fasciotomy in children tend to be excellent; however, diagnostic delays secondary to unfamiliar clinical scenarios can lead to myonecrosis and subsequent poor outcomes.
Related Concept Videos
 01:30
Acute Coronary Syndrome I: Introduction
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations
 01:28
Acute Coronary Syndrome IV: Interprofessional Care
 01:26
Acute Coronary Syndrome V: Nursing Management
 01:29
Pulmonary Embolism I: Introduction
 01:30
Acute Respiratory Failure-III