Related Experiment Video
Updated: Mar 5, 2026
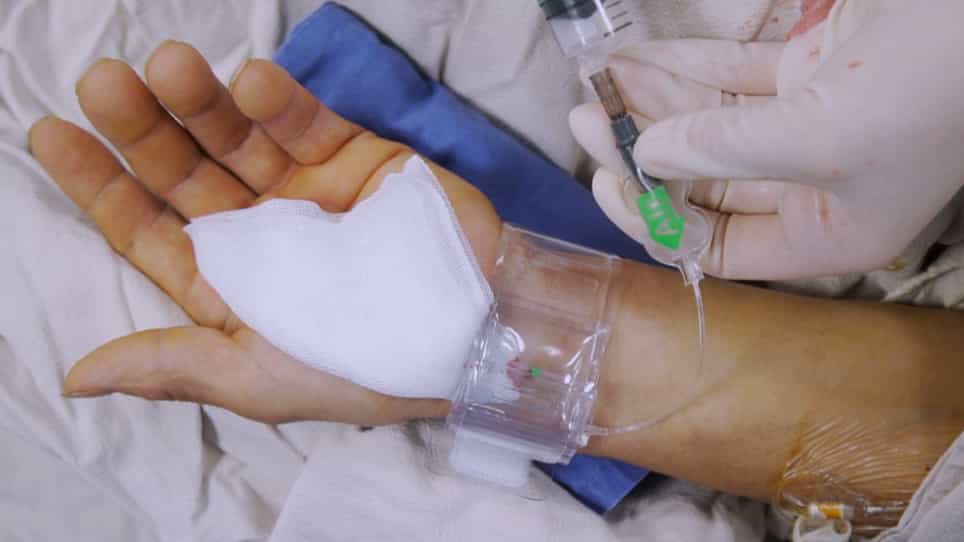

Transradial Access Chemoembolization for Hepatocellular Carcinoma Patients
Published on: September 20, 2020
Radial versus femoral access in patients with acute coronary syndromes with or without ST-segment elevation
Pascal Vranckx1, Enrico Frigoli2, Martina Rothenbühler3
1Department of Cardiology and Critical Care Medicine, Hartcentrum Hasselt, Jessa Ziekenhuis, Stadsomvaart 11, 3500 Hasselt, Belgium.

Insights
Radial access in acute coronary syndrome (ACS) patients significantly reduced net adverse clinical events (NACE) compared to femoral access. This benefit was consistent across ST-segment elevation myocardial infarction (STEMI) and non-ST-segment elevation ACS, demonstrating improved safety outcomes.
Area of Science:
- Cardiology
- Interventional Cardiology
- Vascular Access
Background:
- Percutaneous coronary intervention (PCI) is a cornerstone in managing acute coronary syndromes (ACS).
- Vascular access site selection (radial vs. femoral) can significantly impact procedural safety and patient outcomes.
- The Minimizing Adverse Haemorrhagic Events by TRansradial Access Site and Systemic Implementation of angioX (MATRIX) programme investigated these differences.
Purpose of the Study:
- To compare the efficacy and safety of radial versus femoral access in patients with ST-segment elevation myocardial infarction (STEMI) and non-ST-segment elevation acute coronary syndrome (NSTE-ACS).
- To determine if the choice of access site influences major adverse cardiovascular events (MACE) and net adverse clinical events (NACE).
Main Methods:
- A randomized trial involving patients with STEMI and NSTE-ACS.
- Patients were stratified and randomized to either radial or femoral access.
- Co-primary outcomes assessed at 30 days included MACE (death, myocardial infarction, stroke) and NACE (MACE or major bleeding).
Main Results:
- Radial access significantly reduced NACE in the overall population (P=0.023 for NSTE-ACS).
- While MACE did not reach statistical significance for the primary endpoint in NSTE-ACS (P=0.016), trends favored radial access.
- Radial access demonstrated a consistent benefit in reducing all-cause mortality and access site-related bleeding across both STEMI and NSTE-ACS patient groups.
Conclusions:
- Radial access offers consistent clinical benefits in patients with ACS, irrespective of STEMI or NSTE-ACS presentation.
- The findings support radial access as a preferred strategy for PCI due to improved safety and reduced adverse events.
- The MATRIX program confirms the safety and efficacy of radial access in a broad ACS population.
Aims:
To assess whether radial compared with femoral access is associated with consistent outcomes in patients with ST-segment elevation myocardial infarction (STEMI) and non-ST-segment elevation acute coronary syndrome (NSTE-ACS).
Methods And Results:
In the Minimizing Adverse Haemorrhagic Events by TRansradial Access Site and Systemic Implementation of angioX (MATRIX) programme patients were randomized to radial or femoral access, stratified by STEMI (2001 radial, 2009 femoral) and NSTE-ACS (2196 radial, 2198 femoral). The 30-day co-primary outcomes were major adverse cardiovascular events (MACE), defined as death, myocardial infarction, or stroke, and net adverse clinical events (NACE), defined as MACE or major bleeding In the overall study population, radial access reduced the NACE but not MACE endpoint at the prespecified 0.025 alpha. MACE occurred in 121 (6.1%) STEMI patients with radial access vs. 126 (6.3%) patients with femoral access [rate ratio (RR) = 0.96, 95% CI = 0.75-1.24; P = 0.76] and in 248 (11.3%) NSTE-ACS patients with radial access vs. 303 (13.9%) with femoral access (RR = 0.80, 95% CI = 0.67-0.96; P = 0.016) (Pint = 0.25). NACE occurred in 142 (7.2%) STEMI patients with radial access and in 165 (8.3%) patients with femoral access (RR = 0.86, 95% CI = 0.68-1.08; P = 0.18) and in 268 (12.2%) NSTE-ACS patients with radial access compared with 321 (14.7%) with femoral access (RR = 0.82, 95% CI = 0.69-0.97; P = 0.023) (Pint = 0.76). All-cause mortality and access site-actionable bleeding favoured radial access irrespective of ACS type (Pint = 0.11 and Pint = 0.36, respectively).
Conclusion:
Radial as compared with femoral access provided consistent benefit across the whole spectrum of patients with ACS, without evidence that type of presenting syndrome affected the results of the random access allocation.
More Related Videos
 06:04
Upper-extremity Approach for Secondary Access in Transfemoral Transcatheter Aortic Valve Implantation
Published on: August 8, 2025
 18:11
A Research Method For Detecting Transient Myocardial Ischemia In Patients With Suspected Acute Coronary Syndrome Using Continuous ST-segment Analysis
Published on: December 28, 2012
Related Concept Videos
 01:30
Acute Coronary Syndrome I: Introduction
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations
 01:28
Acute Coronary Syndrome IV: Interprofessional Care
 01:11
Assessment of radial pulse
The radial pulse, located at the wrist, is often the preferred site for assessing peripheral pulse because of its accessibility and dependability. The process of determining the radial pulse involves several steps:
 01:25
Assessment of apical radial pulse
The A-R pulse assessment involves simultaneous evaluation of the apical and radial pulses. When the apical and radial pulse rates vary, this assessment helps identify a pulse deficit.
Pre-Procedural Preparation