Related Experiment Video
Updated: Mar 5, 2026

Evaluation of Patients' Posture and Gait Profile After Lumbar Fusion Surgery by Video Rasterstereography and Treadmill Gait Analysis
Published on: March 23, 2019
Associations between sarcopenia and degenerative lumbar scoliosis in older women
Yawara Eguchi1, Munetaka Suzuki1, Hajime Yamanaka1
1Department of Orthopaedic Surgery, Shimoshizu National Hospital, 934-5, Shikawatashi, Yotsukaido, Chiba 284-0003 Japan.

Background:
Age-related sarcopenia can cause various forms of physical disabilities. We investigated how sarcopenia affects degenerative lumbar scoliosis (DLS) and lumbar spinal canal stenosis (LSCS).
Methods:
Subjects comprised 40 elderly women (mean age 74 years) with spinal disease whose chief complaints were low back pain and lower limb pain. They included 15 cases of DLS (mean 74.8 years) and 25 cases of LSCS (mean age 72.9 years). We performed whole-body dual-energy X-ray absorptiometry (DXA) to analyze body composition, including appendicular and trunk skeletal muscle mass index (SMI; lean mass (kg)/height (m)2) and bone mineral density (BMD). A diagnostic criterion for sarcopenia was an appendicular SMI <5.46. To check spinal alignment, lumbar scoliosis (LS), sagittal vertical axis (SVA), thoracic kyphosis (TK), lumbar lordosis (LL), pelvic tilt (PT), pelvic incidence (PI), sacral slope (SS), and vertebral rotational angle (VRA) were measured. Clinical symptoms were determined from the Japanese Orthopedic Association scores, low back pain visual analog scale, and Roland-Morris Disability Questionnaire (RDQ). Criteria for DLS were lumbar scoliosis >10° and a sagittal vertical axis (SVA) >50 mm. Sarcopenia prevalence, correlations between spinal alignment, BMD, and clinical symptoms with appendicular and trunk SMIs, and correlation between spinal alignment and clinical symptoms were investigated.
Results:
DLS cases had significantly lower body weight, BMI, lean mass arm, and total lean mass than LSCS cases. Sarcopenia prevalence rates were 4/25 cases (16%) in LSCS and 7/15 cases (46.6%) in DLS, revealing a high prevalence in DLS. Appendicular SMIs were DLS 5.61 and LSCS 6.13 (p < 0.05), and trunk SMIs were DLS 6.91 and LSCS 7.61 (p < 0.01) showing DLS to have significantly lower values than LSCS. Spinal alignment correlations revealed the appendicular SMI was negatively correlated with PT (p < 0.05) and the trunk SMI was found to have a significant negative correlation with SVA, PT, LS, and VRA (p < 0.05). The trunk SMI was found to have a significant positive correlation with BMD (p < 0.05). As for clinical symptoms, RDQ was negatively correlated with appendicular SMI and positively correlated with PT (P < 0.05).
Conclusions:
Sarcopenia complications were noted in 16% of LSCS patients and a much higher percentage, or 46.6%, of DLS patients. Appendicular and trunk SMIs were both lower in DLS, suggesting that sarcopenia may be involved in scoliosis. The appendicular skeletal muscle was related to posterior pelvic tilt, while the trunk muscle affected stooped posture, posterior pelvic tilt, lumbar scoliosis, and vertebral rotation. Decreases in trunk muscle mass were also associated with osteoporosis. Moreover, RDQ had a negative correlation with appendicular skeletal muscle mass and a positive correlation with PT, suggesting that sarcopenia may be associated with low back pain as a result of posterior pelvic tilt. Our research reveals for the first time how sarcopenia is involved in spinal deformations, suggesting decreases in pelvic/lumbar support structures such as trunk and appendicular muscle mass may be involved in the progression of spinal deformities and increased low back pain.
Related Concept Videos
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...
 01:16
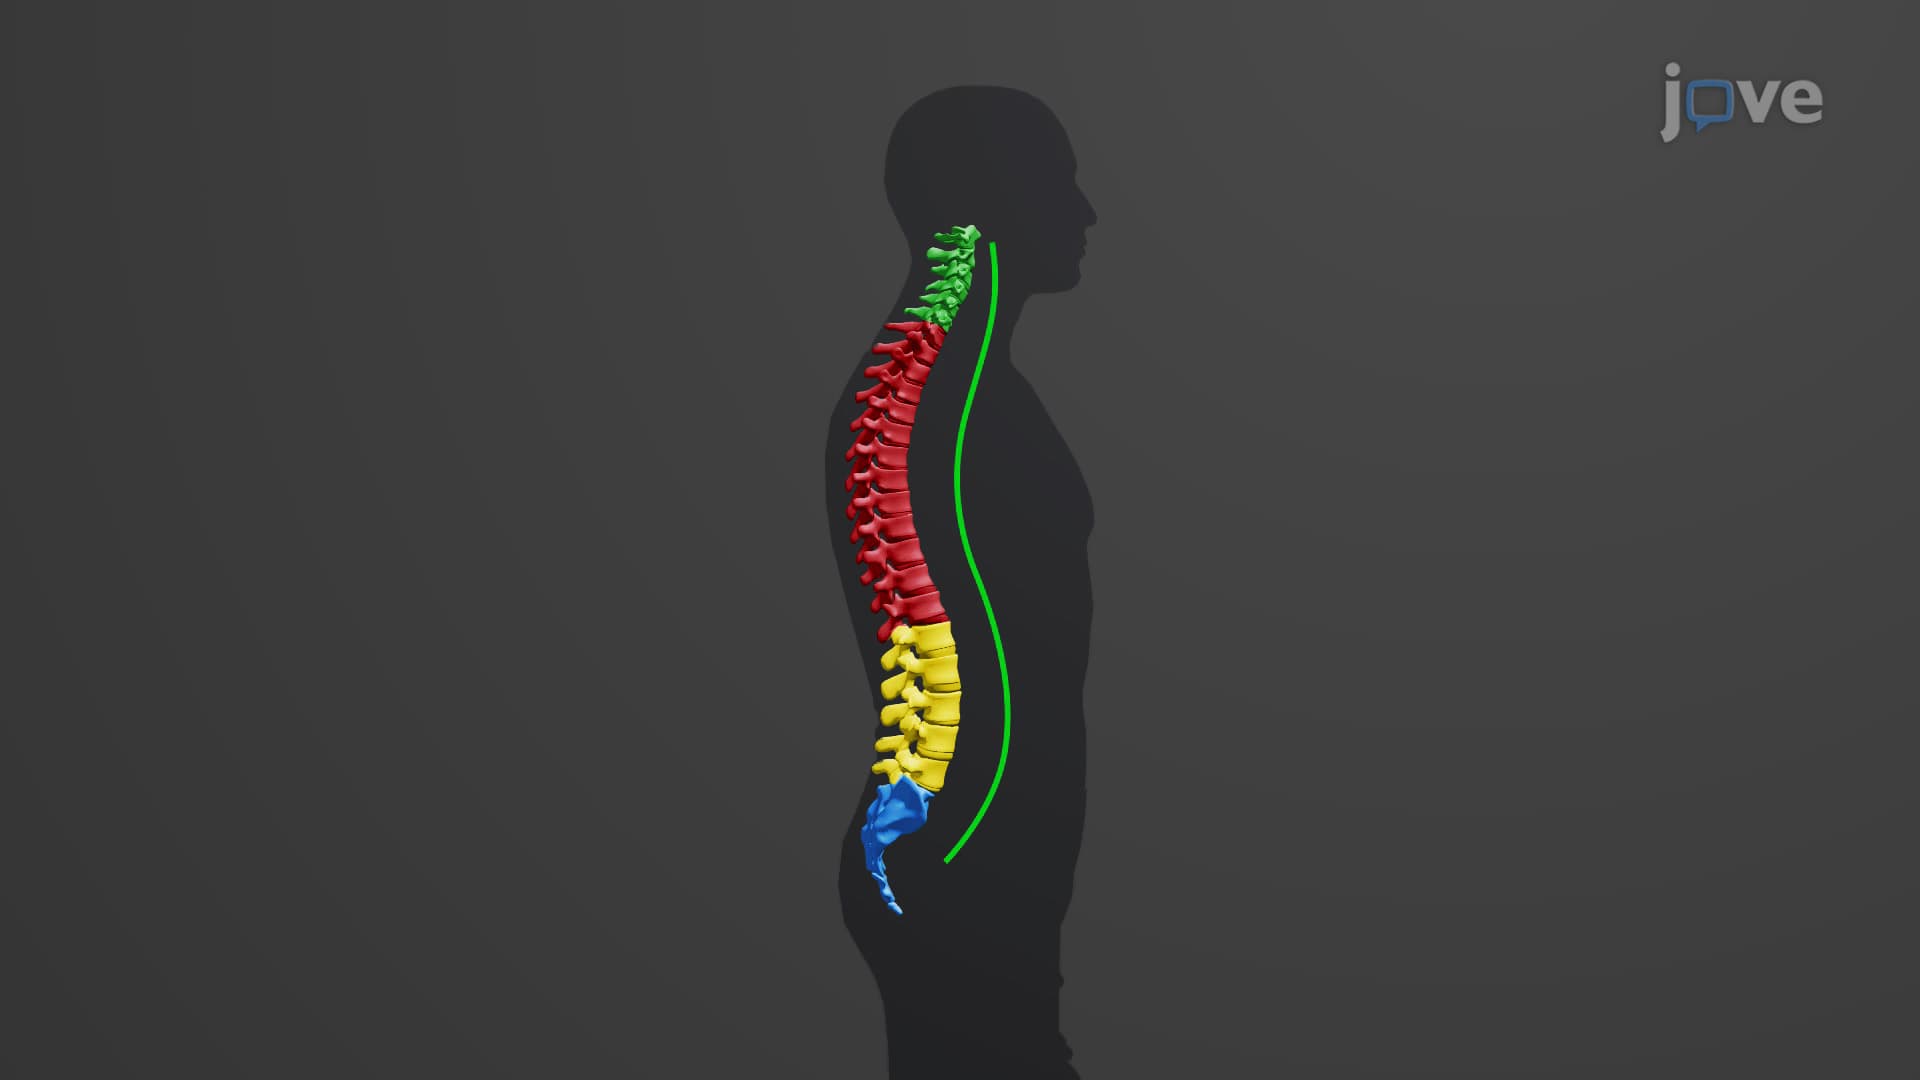
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form...